Showing posts with label Journal of Research & Reviews. Show all posts

Saturday, 30 September 2023

Lupine Publishers | Motivation: We Need Psychobiosocial Model

 Lupine Publishers | Journal of Research & Reviews Health care


Opinion

Motivation has been studied in many ways over many years, historically, the concept of motivation derived from many different lines of inquiry. Morgane (1979) for example attacked the concept as mystical and without representation of nervous system. Now we can see that the concept represents the convergence of different lines of inquiry in the history of philosophy and sciences I will highlight on some viewpoints and global facts of new trends and theories of the concept. Why do we do what we do? Why do we feel what we feel? How can we change what we do and feel? What causes behavior? What starts, maintains, and stops behavior? Why does behavior vary in its intensity? Motivation is the process of initiating, sustaining, and directing psychological and physiological activities, including internal forces such as impulses, drives and desires involved in the process. Motives may operate on a conscious or unconscious level and are frequently divided into physiological (primary or organic, such as hunger and elimination), and psychological (secondary, or personal /social such as af􀏐iliation, competition and interests) [1]. Motivation and emotion derive from movere (Latin for “to move”. Motivation refers to the processes that give behavior energy and direction Motivated behavior leads to rewards or reinforcement, which create in the promotion of new learning, and the maintenance of performance and achievement. On the other hand, the motivation can be measured preferences, interests, choices, aversions, and willingness to overcome barriers to achieve the goal, or to work and perform. At this point the approach/avoidance ply a signi􀏐icant role in understanding the dynamic basis of behavior, especially, the concept of con􀏐licts.

Motivation con􀏐licts is happened when two or more motives with each other resulting in frustration as in animal desiring food but waiting to avoid a 􀏐light with predator. Some motivational con􀏐licts involve acquired motives. According to this view, I see that, social and environmental context ply an important role in the direction of motivated behavior. The motivation is inferred from behavior to account for the shifts in arousal and direction of behavior throughout the day and season. The motivated behavior may be aroused or derived by a change in the internal environment, by naturally arousing stimuli such as incentive, signs stimuli, and previously neutral stimuli that come to arouse because of learning and conditioning. The hypothalamus and other structures lining the ventricles received information from the internal environment through seven known cirecumventricular organs that lie outside the blood-brain barrier. The hypothalamus exerts over the internal environment through its in􀏐luence on pituitary and through its connections with the brainstem such as dorsal vague complex. These connections allow it to participate in neural control over autonomic functions and metabolism. Learning and experience play signi􀏐icant roles in motivation and rewards (reinforcement). It is only with humans that we have a way of knowing about hedonic experience for we can measure pleasantness and unpleasantness with suitable rating scales or magnitude estimation techniques.

There is connection between motivation and creativity. The enjoyment is justi􀏐ication enough for intrinsic motivation, and the intrinsic motivation boosts creativity. On the other hand, personal relevance of a task causes intrinsic motivation [2]. Higher incentives do not always lead to better performance. Monetary incentives worsen performance in tasks that require creative problem solving. For complex tasks, people are driven by autonomy, mastery and purpose. Cultivate emotional ownership. As we suggested at the outset of this article, it is indeed an exciting time for the study of motivation–cognition –emotion interactions. Although studies of motivation have been an active focus within psychology and neuroscience for decades, there has clearly also been a recent rejuvenation of interest [3]. It is very important to investigate the relationship between motivation, emotion and cognition in personality. The 􀏐ield is now poised to make rapid progress on these and related questions, but that such progress will critically depend on the adoption of an integrative, collaborative approach. Psychological study of motivation searches for theories that describe the functions of motivation in natural systems such as humans and animals. New trend in investigating emotion is that the psychological theories of motivation are implementing in arti􀏐icial systems [4].

Conclusion

we need an integrated/global model for investigating the motivation because it is complex phenomena. This model should be containing the psychobiosocial trend for approaching the goal of science: understanding, predicting and controlling the motivated behavior in personality [5]. Rudolf concluded, “Motivated behavior is complex. Obtaining goals — ‘appetitive’ behavior — involves the integration of cognitive knowledge about your goals with habits and the motivational impact of environmental stimuli (CSs). Once you’ve obtained your goal, you need to integrate complex ‘consummatory’ response patterns to use it. Structures within the brain’s limbic system play an important role in appetitive and consummatory behaviors; we can distinguish those structures contributing to each”.

Read More About Lupine Publishers Journal of Research and Reviews Healthcare Please Click on Below Link:
https://lupine-publishers-research.blogspot.com/

Saturday, 12 August 2023

Lupine Publishers | Perspective of Youth about Chromoblastomycosis

 Lupine Publishers | Journal of Research & Reviews Health Care


Abstract

Objectives of the present study were to evaluate the perspective of youth about chromoblastomycosis. A total of 100 subjects were asked to answer the questionnaire. The subjects were students in Bahauddin Zakariya University Multan, Pakistan. Alexander pedroso in Saopolo, Brazil studied the cases of Chromoblastomycosis in 1911. The name of disease was blastomycosa negra. The name of a disease figueria described by German Physician. It was done from the current study that most of the females said that chromoblastomycosis was not a viral, fungal, bacterial disease. There is a 50% chance whether it may or may not be a viral, fungal or bacterial.

Keywords:Chromoblastomycosis; Fungal Disease; Cauliflower

Introduction

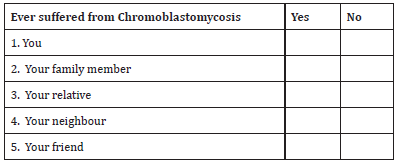
Fungal infection of the skin is the Chromoblastomycosis, which is a long-term. Often in rural areas, in tropical or subtropical climates this infection occurs such as Madagascar in Africa and Brazil in South America . By many different types of fungi, this infection can be caused. Very slowly, chromoblastomycosis spreads. It is not often lethal and usually has a good projection, but it’s cure is very difficult. Medication and surgery, the several treatments include. Among the subcutaneous mycoses and is ubiquitous, Chromoblastomycosis is classified. Chromoblastomycosis disease was recommended by the International Society for Human and Animal Mycology in 1992.On the foot or leg chromoblastomycosis begins [1]. Where the skin is wrecked, other exposed body parts may be infected. Papules are formed in this disease. Dull red patches are formed when these papules extend. Objectives of the present study were to evaluate the perspective of youth about chromoblastomycosis (Tables 1-4).

Table 1: Questionnaire to assess awareness about Chromoblastomycosis.

Lupinepublishers-openaccess-Research-Reviews

Table 2: Questionnaire to analyze awareness about ubiquity of Chromoblastomycosis.

Lupinepublishers-openaccess-Research-Reviews

Table 3: Questionnaire to estimate vision about Chromoblastomycosis transference.

Lupinepublishers-openaccess-Research-Reviews

Table 4: Questionnaire to evaluate perspective of youth about Chromoblastomycosis.

Lupinepublishers-openaccess-Research-Reviews

Materials and Method

Results

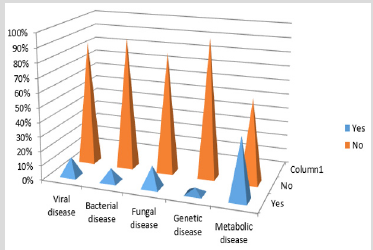
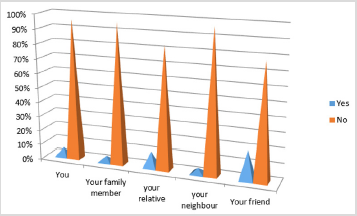
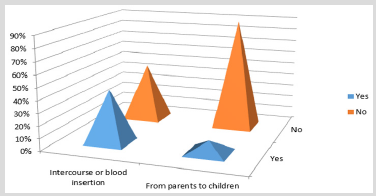
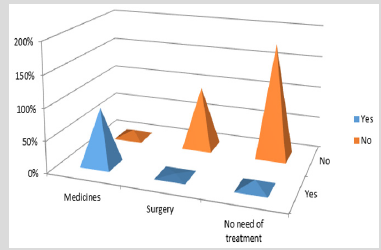
Presence and absence of chromoblastomycosis in male and female is shown in the (Figures 1-4). In the first column graph it was showed that most of the females said that Chromoblastomycosis was not a viral disease and most males also said that it is not a viral. Most of the females took this disease not as a bacterial and most males said that it was not a bacterial disease [2-5]. Most of the females said that it was not a fungal disease and males also had a same opinion. Both males and females said that chromoblastomycosis was not a genetic disease. Most females said that chromoblastomycosis was a metabolic disease. But when we observed the disease then we concluded that chromoblastomycosis was a fungal disease. Then, next question asked from them that whether you, your family member, relative, neighbor and friend suffered from this disease or not then most of the females and males said no. The other question asked to them whether the disease by contacts or blood transfer or from parents to offspring was transmitted or not then the most females said that disease was not transmitted by contacts or blood transfer or from parents to offspring. The other question were that either the disease was treated by medicines, surgery or no treatment was available for that then most females and males said that it could be treated by medicines [5-8].

Figure 1: Questionnaire Evaluation About Etiology of Chromoblastomycosis.

Lupinepublishers-openaccess-Research-Reviews

Figure 2: Questionnaire to evaluate views about prevalence of Chromoblastomycosis.

Lupinepublishers-openaccess-Research-Reviews

Figure 3: Questionnaire to evaluate views about prevalence of Chromoblastomycosis.

Lupinepublishers-openaccess-Research-Reviews

Figure 4: Questionnaire to evaluate views about Chromoblastomycosis.

Lupinepublishers-openaccess-Research-Reviews

Discussion

In recent studies, questionnairebased studies had given an important development. Alexandre pedroso in Saopolo, Brazil studied the cases of Chromoblastomycosis in 1911. The name of disease was blastomycosa negra. The name of a disease figueria described by German Physician [9,10].

Conclusion

From present study, it was concluded that most of the females said that chromoblastomycosis was not a viral, fungal, bacterial disease. There is a 50% chance whether it may or may not be a viral, fungal or bacterial.

Read More About Lupine Publishers Journal of Research & Reviews Healthcare Please Click on Below Link:
https://lupine-publishers-research.blogspot.com/

Thursday, 29 June 2023

Lupine Publishers | Bitter Gourd Relish and Blood Group Relationship

 Lupine Publishers | Journal of Research & Reviews Health Care


Abstract

The topic of our project was to explore the “Bitter gourd relish and blood group relationship.” The number of subjects to examine were 176. The process we adopted before examining the subjects was acquiring their consent before the collection of related information. We checked blood group of the subjects by using lancing device along with anti-sera A, B and D solutions and then noted the precipitate formation. In the meanwhile we asked whether they liked bitter gourd as a dish or not. We gathered the basic information about bitter gourd composition and its merits for the subjects that used it as a dish or juice. Then we organized the random data presented in a table and observed the relationship of bitter gourd liking to blood type and made a comparative analysis of blood groups. At the end, we defined the results.

Keywords:Bitter Gourd; Blood Grouping; Bitter Melon; Karela; Fondness; Relish; Liking

Introduction

Human beings has a fluid inside their bodies known as blood. Blood comprises leukocytes, erythrocytes, and platelets. ABO Blood Group system was first discovered in 1901 by Karl Landsteiner. The classification of human blood group is based on antigens and antibodies present in blood. Antibodies are the natural immune system proteins that act as a defense mechanism. ABO system is encoded by gene I located on chromosome 9. This gene is polymorphic having three alleles represented as Iᵃ, Iᵇ and i. If a subject has blood group A, then it means it has antigen A present on its red blood cells and antibody B is present. So, genotype IᵃIᵃ or Iᵃi, will produce phenotype A. Subject having genotype IᵇIᵇ or Iᵇi will produce phenotype B. Subject having AB blood, no antibody is present, and genotype is IᵃIᵇ. If blood group is O, this subject has no antigens and both antibodies are present in the blood plasma. So, the homozygous recessive genotype ii produces the phenotype O. The universal donor is O blood group and can donate blood to group A and group B types. The universal recipient is AB group, means it can take blood from any donor like from group A, B and O [1]. There is another protein known as Rh protein or Rh factor present on erythrocytes. A subject is Rh positive when the Rh protein is present and Rh negative if Rh protein is absent. So, blood group of a subject may be A⁻, A⁺, B⁻, B⁺, AB⁻, AB⁺, O⁺ and O⁻ [2].

Bitter gourd a vegetable, also known as bitter melon, bitter squash, balsam pear, and simply as karela (in Urdu). The scientific name of bitter gourd is Momordica chianti. Bitter gourd a vine of the family Cucurbitaceae, grown mostly in Asia and Africa [3]. Bitter gourd juice consists of nutrients like iron, magnesium, potassium and vitamin C. It is rich in dietary fiber. It contains two- fold of calcium of spinach, potassium of banana and beta-carotene. The compound momordicines and increased levels of calcium is the cause of characteristic bitterness of bitter gourd. Bitter gourd contains diabetic control compounds naturally. Also, bitter squash juice is anti-inflammatory and lowers bad cholesterol levels in human body and acid lessons the risk of heart of stroke and heart attack due to enrichment in iron and folic acid. It maintains the blood pressure of body. Anti-oxidants along with vitamins like C and A in bitter gourd retards premature skin ageing and minimizes wrinkles. Momordica charantia, a compound strengthens the anti-oxidant activity of liver enzyme and provides defense against liver failure and removes intoxication caused by frequent alcohol uptakes that settled down in liver. It also boosts functioning of bladder. Bitter melon contains less amount of carbohydrates, calories and fat, that play role in removal of already present fat cells and inhibits the generation of new fat cells. Anti-oxidants in bitter melon reduces the risk of cervical, prostate and breast cancer in humans. Bitter gourd decreases the sight-related problems such as cataract as being rich in vitamin A and beta-carotene and strengthens eyesight [4]. Objective of present study was correlating blood groupings with bitter gourd.

Materials and Method

Blood Grouping

The materials required to test blood group were the required quantity of blood from specific groups (three drops) was taken for testing with a prick of sterilized needle (blood lancet) on a fingertip (any), slides and solutions of anti-sera A (antigen A with B antibody), anti-sera B (contains antigens B with A antibodies) and anti-sera D (Rh +ve factor). Anti-sera means the solution contains opposite antibody with respect to antigen. First, label the slide with A, B, and D so that anti-sera drops can be identified. Then placed three drops of blood on the slide. Afterwards, add a or few drop of anti- sera A, anti-sera B, anti-sera D according to the labeling on the slide. In the end, leave the slide for two to three minutes or mix each drop with needle wire and observe the changes in drop solution. Precipitate formation of blood drop shows that blood group presence in subject. Precipitate formation in anti-sera D, meant positive. Precipitate formation in any anti-sera A, B and D, then A⁺, B⁺ blood group. If precipitates were formed in all three anti-sera A, B and D, then blood group was AB⁺. If precipitates were formed in only anti-sera D blood group was O⁺ and no precipitate in any anti-sera, meant that blood group was O⁻. If precipitates were formed in either anti-sera A or B, or both then blood group was A⁻, B⁻ and AB⁻ respectively.

Project Designing

The topic we selected was bitter gourd relish. We asked subjects whether they like bitter gourd as a dish or not because of its bitter taste. Subjects also gave their consent to check their blood group. Then we organized the random data and did the statistical analysis. The subjects which we chose for our project, were the 176 students of Bahauddin Zakariya University, Multan Pakistan.

Statistical analysis

We did Statistical analysis by using MS Excel

Results and Dicussion

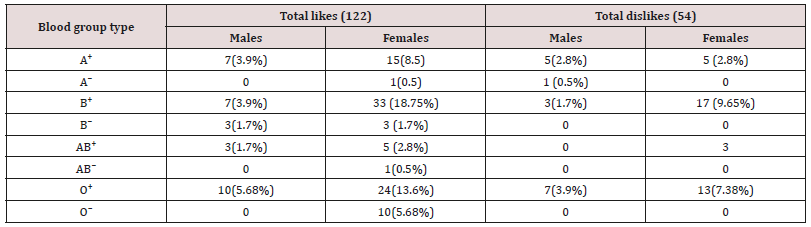
Studies based on questionnaire have given an important advancement in science [5-12]. No linkage or research work was found that correlated my topic (Table 1).

Table 1:

Lupinepublishers-openaccess-Research-Reviews

Conclusion

The present study concluded in figure (A) that bitter gourd fondness was shown mostly by B⁺ subjects. B⁺ blood group subjects liked the bitter melon most. The frequent occurrence of similar blood group of my subjects were B⁺. All the subjects of our research having O⁻ blood group were females and they all liked the bitter melon. The likeliness percentage of subjects with blood group O⁺ and B⁺ were same, (11%). All blood group AB⁻ and B⁻ subjects liked bitter squash. Out of 46 male subjects, bitter melon was liked by 30 males. Total 92 female subjects liked the taste of bitter squash as a dish out of 130.

Read More About Lupine Publishers Journal of Research and Reviews Health Care Please Click on Below Link:
https://lupine-publishers-research.blogspot.com/

Saturday, 11 March 2023

Lupine Publishers | British Non-Regular Services Health Professional Veterans’ Perceptions of Pre-Deployment Military Advice for The Gulf War

 Lupine Publishers | Journal of Research & Reviews Healthcare

Abstract

Little has been written about the receipt of advice and its perceived usefulness, or even if it was routinely provided by the British military to Voluntary and Reserve (non-Regular) Services troops in preparation for deployment to the Gulf War. The study in its entirety comprised data from three postal questionnaires (each six months apart) completed by 95 veterans commencing six months after their return home. Their perceptions of the usefulness of two forms of advice were explored] for domestic preparations (e.g. wills and insurance) and ii] for managing social relationships (close relationships and other military personnel) during pre- deployment to the Gulf War 1991. They also provided recommendations as to how such advice could be improved. Advice for domestic preparations (completion of wills and insurance, etc.) was received by 56% of the participants, but advice for managing social relationships with family and other military personnel once mobilised was sparse (8:8%) and in the main, was provided by charities. This last form of advice was perceived by most of the non-recipient veterans as being of a low priority for the military even though most of the veterans indicated qualitatively that it would have been useful. The veterans’ recommendations are discussed.

Keywords: Gulf War (1991); Voluntary Services Health Professional Veterans; Military Advice; Pre-Deployment

Introduction

The Mobilisation of British Voluntary Services and Reserve Health Personnel

In November 1990, the `British Government recognised that there was an insufficient number of Regular Services medical personnel to meet the projected casualties from the impending war with Iraq, commonly known as the Gulf War (GW). Part- time Territorial Army (TA) and equivalent Voluntary Services’ (VS) personnel working in health professional roles (doctors, nurses, and other professions allied to medicine) were invited to volunteer [1]. As the initial response proved to be inadequate, retired ex Regular Services health professional personnel whose names had been retained by the military on the Reserve List were compulsorily called up: an action not undertaken since the Korean War (1950-53). Several United States (US) authors [2,3] report that for US Reservists, pre-deployment to the GW proved to be an unusually short time in which to make domestic preparations; wind-up civilian work-life; mobilise into new military groups and receive training specific to the requirements of deployment to a war in the Middle East. Some US Reservists were reported as being dissatisfied and distressed because they had not anticipated either their call-up or their stressful transition from ‘civilian to soldier’ [3]. These reactions could well have been similar for the British health professional veterans (HPVs) who like their US Reservist counterparts, lived and worked in civilian communities and not in military establishments [4,5]. Those in the part-time TA received support from their community-based parent TA Units but the ex- Regular Reservists both called up and volunteers, often had not retained military connections. In effect and despite being on the Reserve List, they were no longer part of the ‘military family’ [6].

The importance of giving support to military families prior to and during British and other nations’ military separations in peace and war has been emphasised by many authors prior to the GW, as a means of avoiding disruption to the psychological wellbeing of service personnel during deployment [7-10]. Early evidence of such support for British families during the GW was found only in one small British study by Quinault (1992) in which 12 wives of RAF deployed personnel described their military support as adequate but found that as with US military families [11], a lack of accurate information-giving increased their levels of stress [12]. There appears to be a paucity of early research concerned with the reactions of British non-regular Services health professional troops towards the GW’s unique conventional and expected unconventional (chemical/biological) warfare context and circumstances. In its place, it seems that there has been a reliance upon the outcomes of the more extensive early US GW research [13,14] to fill the British experiential gaps with the assumption that socially, organisationally and culturally, US troops were ‘like with like’ in relation to their British counterparts. Therefore, despite the time lapse since data collection and this article, it is believed that this study and its findings remain relevant. In response to the paucity of literature, this part of the study incorporated 4 questions:

a) What advice was received by the HPVs from the military?

b) In what form was it received?

c) How effective was it according to the perceptions of the HPVs?

d) What recommendations do the HPVs suggest that could improve advice during pre-deployment.

Methodology

Design

The study utilised a longitudinal design comprising an initial postal questionnaire survey and two follow up postal questionnaires, each issued six months apart. The first questionnaire sought retrospective experiential data comprising reactions to warrelated (pre-deployment and deployment) circumstances; advice; health; social support, and social and professional relationships in the six months before and in the first six months following the return home. The second and third questionnaires requested the provision of prospective repeated data at 12 months and at 18 months post war in the above key areas of interest where change could be anticipated.

Recruitment of the Participant Sample

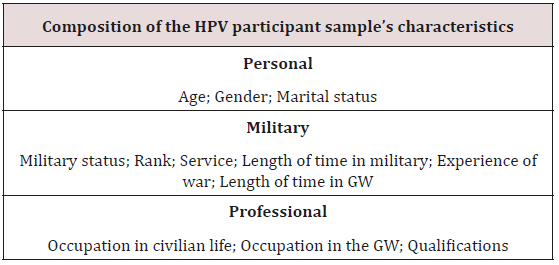
Recruitment was conducted between July and August 1991 some 4-5 months after the non-regular Services’ troops return home from the GW. The first of three stages of the recruitment of the non-regular Service troops as study’s participants was initially opportunistic. One HPV Reserve called-up nurse (a colleague known to the lead author) held a personal contact list of 74 HPVs who had returned home together by air in late March 1991 following the end of the GW. As it would have been unethical for the researcher to have had direct access to the contact list, the colleague acted as an intermediary by forwarding a letter from the author to those named with details of the study and a pre-paid postal return envelope for the return of completed contact details and consent form. In the event, 57 (47 ex regular Reservists and 10 Territorial Army personnel) of the 74 HPVs agreed to participate in the study: a return rate of 77%. In the second recruitment stage, a purposeful increase of the VS TA group to match the size of the Stage 1 recruited Reservists (n=47) and in similar health professional roles was sought. This was achieved by asking the 10 consenting VS TA participants from Stage 1, to act as ‘intermediaries’ in making a ‘snowball’ access to similar others within their own or other TA units. To facilitate this, each of them was supplied with 5 introductory letters (n=50) with pre-paid return contact slips for direct return to the author. As a result, a further 33 TA HPVs agreed to participate in the study raising the total for the VS TA to 43. Although there was no way of knowing if the total number of letters (n=50) had been issued by the initial TA HPV participants, the estimated percentage (assuming all letters had been issued) for recruitment in this stage was 66%. Finally, in a third recruitment stage, a GW veteran Welfare Officer in the Order of St John of Jerusalem (a voluntary service that provides welfare support to the army) having heard of the study, made direct contact with the author to seek inclusion for the 10 Welfare Officers (WOs) who had been volunteers in the GW. Using the same return system as in previous stages, 5 (50%) of these veterans agreed to become participants. Personal, professional and military demographic characteristic variables (as independent variables) of the participant sample of 95 HPVs are given in Table 1.

Table 1: Composition of the HPV participant sample.

Lupinepublishers-openaccess-Research-Reviews

Procedure

First a pilot study with 5 participant HPVs assisted the researcher through focus groups and interviews in the preparation of the first questionnaire that included the receipt and acceptability of advice from the military during pre-deployment. Each of the three questionnaires, issued at 6 monthly intervals, comprised closed questions followed by related free text justification. This dual approach provided opportunity for a greater depth of understanding more so than either could have achieved if employed alone [15]. The pilot study’s HPVs identified two forms of pre-deployment advice that they claimed to have received from the military:

a) advice for domestic preparations, e.g. wills, life insurance, work and domestic financial affairs, and

b) advice for managing social relationships at home and in the military.

These form the focus of this article and coupled with demographic data given in Table 1, enabled the analysis of advice to be seen from personal, civilian and military perspectives.

Variables of Interest and Data Analysis

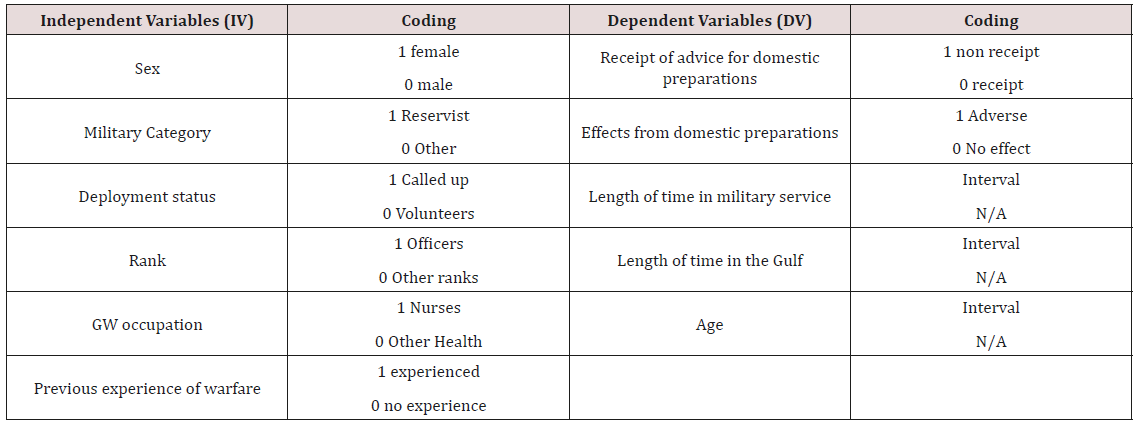
In 1993, the data were first analysed and then re-analysed in 2012 when presented as part of a successful PhD thesis. Quantitative data were analysed using the Statistical Package for the Social Sciences (SPSS) Version 20. Logistic regression was employed to establish the relationship between a categorical dependent variable (DV) with one or more of the above characteristic independent variables (IV). It calculates the likelihood (ratio of the odds) of an event occurring or not. Table 2 provides the two types of variables and their values of interest (given as 1). Qualitative data were examined by two researchers independently identifying and categorising the key words or phrase labels using Thematic Analysis [16]. The labels were devised to capture as closely as possible the meaning of the HPVs’ original words or phrases [16,17]. Where there were differences of interpretation between the researchers, a joint reanalysis of the data was made to facilitate consensus.

Table 2: Coding of IV and DV variables of interest for logistic regression.

Lupinepublishers-openaccess-Research-Reviews

Ethical Considerations

Although the study preceded the introduction of formal National ethical standards and procedures for British research, the general principles of: doing no harm; seeking participant informed consent; the acceptance of participant autonomy over compliance, and of respect for rights to privacy, anonymity and confidentiality [18] were upheld throughout the research process. Authoritative military and academic advice were taken before and throughout the study to avoid sensitive issues. All information forwarded to the HPVs cautioned them against breaching the Official Secrets Act. The data have been held securely and in accordance with the Data Protection Act, 1987 and its update in 1998. All data has been stored anonymously in digital format on a password-protected computer.

Results

Return Rate

A total of 134 contact letters were issued across the three recruitment stages resulting in 95 consenting HPVs and provided an estimated minimum overall response rate of 71%. It is of note that at the time of recruitment to the study, the total numbers of volunteer TA and Reserve personnel deployed to the GW had not been reported in the public domain but figures given some years after the GW suggest that the 95 HPVs in the participant sample represent a subset of some 9% of the total Reserve and TA (or similar VS organisations) health professional personnel sent to the GW [19].

Characteristics of the Participant Sample

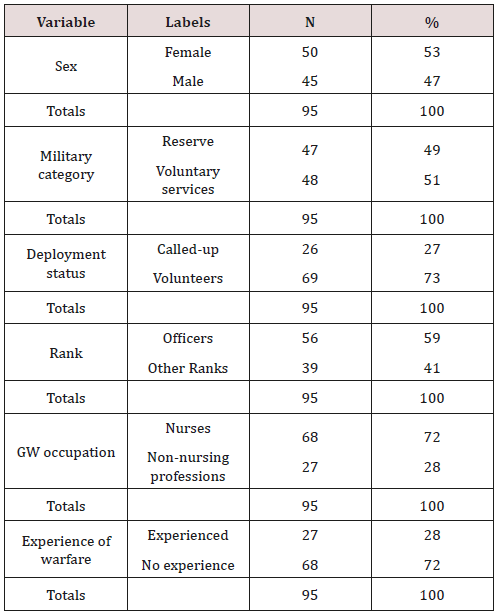
The personal, military and health professional details of the participants were collected. As shown in Table 3, there were 6% more females than males and the HPVs’ ages ranged from 23 to 53 years (mean=37; SD=8.59; median=35). Of the 48 in the Voluntary Services, all save the 5 Welfare Officers were in the Territorial Army [TA] and all were volunteers, whereas of the 47 in the Reserve, 26 (27%) were mandatorily called-up and the remaining 21 (21%) were volunteers. There were 18% more officers than those in other ranks. Sixty-eight (72%) of the HPVs were in nursing roles during the GW as compared with 27 (28%) in other health professions. Of the 95 HPVs, 27 (28%) had past warfare experience and of these, 17 (18%) were ex Regular Reservists and 10 (10%) were in the TA. The remaining 68 (72%) had no experience of warfare. Sixtyseven of the 68 nurses provided their civilian nursing qualifications (1 missing) and during the GW, 49 (73%) worked as Registered General Nurses; 4 (6%) as Registered Mental Nurses, and the remaining 14 (21%) were State Enrolled Nurses. All other health professionals (doctors, physiotherapists, etc.) were allocated to the same professional roles in the military as they held in civilian life. Only combat medical technicians (akin to civilian ambulance paramedics) worked in non-health civilian roles prior to the GW. The time spent in the Gulf for most HPVs was between 2 and 3 months. When the HPVs’ length of time in the Gulf was compared with their deployment military status using a Mann-Whitney U test, Reservists spent less time in deployment (mean rank=37.16) than those in the VS (mean rank = 58.61): a significant difference (U=618.500, Z= -2.414, p<0.01).

Table 3: The HPVs’ personal and military characteristics.

Lupinepublishers-openaccess-Research-Reviews

Types of Advice

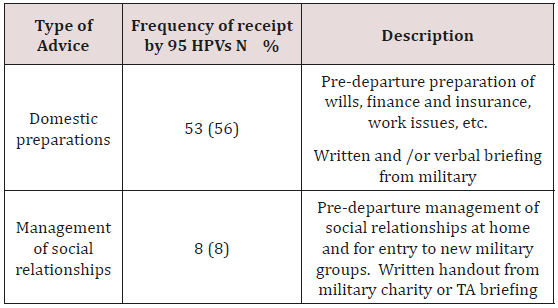
Table 4: Types of advice suggested in the Pilot Study as issued by the British military during pre-deployment (N=95).

Lupinepublishers-openaccess-Research-Reviews

The Pilot Study participants identified two forms of advice given by the military and/ or by related charities during pre-deployment to the GW with their respective frequencies of receipt by the 95 HPV participants, as shown in Table 4. ‘Advice for domestic preparations was the most frequently received form of advice (56%), whereas the receipt of advice regarding social relationships was considerably lower (8%). Both forms of advice were given in a written format and in the case of those in the TA, also in verbal briefings.

Frequency of Receipt of Advice for Pre-Deployment Domestic Preparations

Table 5: HPVs’ thematic comments for the receipt or not of advice for their domestic preparations.

Lupinepublishers-openaccess-Research-Reviews

Fifty-three of the 95 HPVs (56%) received advice from the military regarding their domestic preparations. Eight HPVs provided related descriptive comments and of these, five were in the TA. As shown in Table 5, Theme 1, those in the TA confidently recounted that their domestic affairs had already been adequately prepared as a routine annual requirement for all members of the part-time VS military and as such did not seem to need the advice. Of the remaining 42 (44%) participants who did not receive this form of advice, 33 provided written comments hypothesising on the effect such advice might have had if it had been received. Comments from the 33 non-recipients of advice for domestic preparations are given as Themes 2 and 3 in Table 5. In theme 2, some HPVs associated their non-receipt of advice with not having enough time between mobilisation and departure to the Gulf in which to access or put advice into practical use. It is also suggested that the timing of such preparations (during the run-up to Christmas 1990) had a negative effect upon their stress levels even before departure to the Gulf as they tried to juggle home commitments with military requirements. Furthermore, some Reservists called-up emphasised that they had civilian responsibilities that required additional attention (e.g. rearranging care for dependent relatives, arranging work cover if self-employed) but the military were perceived as making little or no allowances for these issues. As indicated in the last comments in Table 5, the making of wills raised the HPVs’ consciousness of the gravity of their situation and its potential for life-threat (injury or death). This was likely to have been particularly difficult for Reservists call-up, who had no choice in having to place their lives at risk.

Predicting the likelihood of Non-Receipt of Military Advice for Domestic Preparations

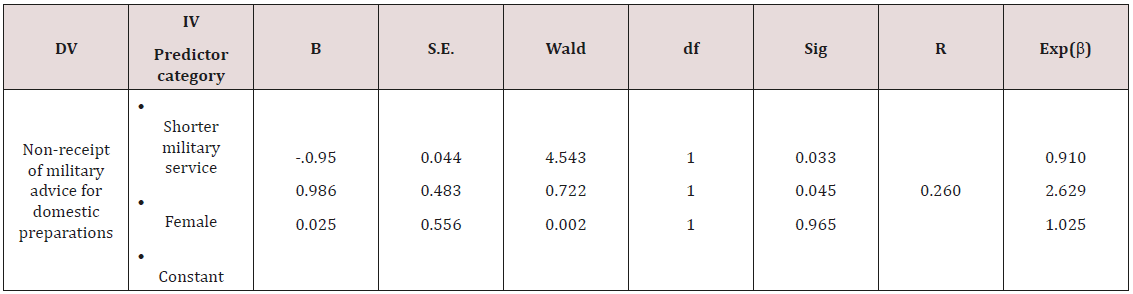
Table 6: Logistic regression to predict the likelihood of non-receipt of military advice for domestic preparations with sample characteristics (N=95).

Lupinepublishers-openaccess-Research-Reviews

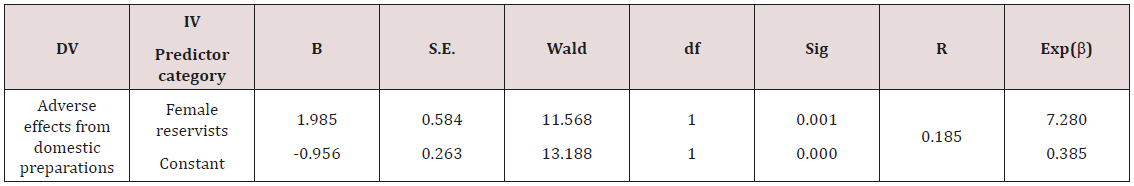
Using logistic regression as shown in Table 6, ‘time in military service’ (shorter time) and gender (females) were the best predictors of the ‘non-receipt of advice’. When both variables were re-entered into the Logistic regression model as the interaction term ‘gender/time in the military’, the output was not significant. Thus, those who were female and those with a shorter length of military service each had a significant and independent likelihood of being the non-recipients of advice (shorter military service R=0.260, β=0-910, p=0.033; female R=0.260, β=0.0986, p=0.045). When the 95 HPVs were asked to indicate if they had experienced any effects (practical or psychological) from undertaking domestic preparations, 34 (36%) HPVs described experiencing ‘adverse’ effects and 57 (60%) stated that they had ‘no effects’. The remaining 4 (4%) HPVs perceived these effects as ‘positive’ indicating a sense of relief at having made adequate provision for themselves and their families (in some cases, will-making was a task that had been put off in the past). Of those with adverse effects, a majority (28:82%) provided written comments indicating that making their wills heightened a morbid anticipatory fear about going to war. As shown in Table 7, using logistic regression to predict those most likely to have adverse effects from domestic preparations, a significant interaction between gender and military status indicated that female reservists were those most likely to have adverse effects (R=0.185, β=7-280, p=0.001). Using chi-square, no significant relationship was found between those in receipt of advice for domestic preparations with those with adverse effects arising from undertaking such preparations (χ2 =0.33, df=1, p>0.05).

Table 7: Logistic regression to predict the likelihood or not of effects from domestic preparations in sample characteristics (N=91).

Lupinepublishers-openaccess-Research-Reviews

*4 values excluded

Receipt of Pre-deployment Military Advice Regarding the Management of Social Relationships

Four TA respondents commented that they had received good advice from their TA Unit in the form of a ‘briefing’ for the management of their social relationships prior to departure to the Gulf. A further 4 Reservists stated that they had been recipients of handouts from military charities such as Soldiers, Sailors, Air Force Association (SSAFA) but had received nothing directly from the military. The remaining 87 (92%) stated that this type off advice had not been received. Thirty-two HPVs provided related comments. Of these, 8 had received advice and 24 were from non-recipients, who speculated upon the potential usefulness of such advice had they received it. Examples drawn from both sets of comments are given below in Table 8 under thematic headings. Thematic analysis of the 24 non-recipient HPVs’ comments given in Table 8 revealed that all participants believed hypothetically that if they had received advice on how to manage their social relationships, it could have been beneficial. Those with close partners (Theme 3) suggested that such advice could have lessened their tendency towards selfcentredness and withdrawal which caused spousal resentment and upset with other family members prior to departure. Other HPVs hypothesised that the receipt of this advice could have been beneficial in their coping with the relationship difficulties that arose when joining new military groups both during pre-deployment training and following arrival in the Gulf (Theme 4).

Table 8: Thematic comments for advice for the management of social relationships.

Lupinepublishers-openaccess-Research-Reviews

HPVs’ Recommendations to Improve Advice During Pre-deployment

Table 9: HPVs’ recommendations to improve advice for pre-deployment.

Lupinepublishers-openaccess-Research-Reviews

Ninety-seven recommendations were given by 81 (85%) of the 95 HPVs, regarding improvements to all aspects of the experience of pre-deployment to war. Of these, the most frequently suggested recommendation by 48 (59%) of the 81 HPVs) was to improve advice for domestic preparations. Of these, three themes were formed as given in Table 9. In theme 1, some HPVs recommended that they should be pre-warned regarding the reality of the war that lay ahead as part of their preparations and most wanted this to be delivered by an experienced war veteran. Others (theme 2) wanted written information listing the practical domestic requirements to be met before departure as described above but they also included a direct military contact via letter to partners explaining why the non-regular health professionals had been requested to volunteer or had been called up. The final theme addressed the psychosocial issue of entry to new groups and recommended being forewarned of the likelihood of inter-group difficulties and how to manage these. The remaining 14 (15%) said that ‘no improvements were necessary’.

Discussion

The study aimed to describe the frequency of receipt of the two forms of advice received during pre- deployment by the HPVs, how they were accessed and their perceived quality and usefulness. The small number of VS TA recipients of pre-deployment advice for domestic preparations accessed it through their units with delivery from personnel with experience of participation in previous wars. As such, there appears to have been dissemination of verbal and written advice concerning these TA preparations. From the comments, the TA HPVs appear to have had their domestic preparations well in hand as a requirement for their military routine preparations for annual exercises. As they appeared to regard their upkeep as a personal responsibility rather than a pressure from the military, this might suggest that they had adopted a problem-focussed coping strategy towards domestic preparations rather than the emotion-focussed coping strategy apparent in the comments from some Reservists. Meredith [20] contend that by adopting the first approach, it is likely that the sense of internal control and resilience to stress could increase [21]. The above findings are akin to other published findings from this study showing that the TA HPVs were more satisfied with their pre-deployment training for the GW than their Reservist counterparts [22].

The non-receipt of pre-deployment advice for domestic preparations was associated independently with the HPVs who were female and those with a shorter military service. One tentative explanation for this gender effect could lie in the observed unequal distribution in civilian life in the undertaking of housework workload where the greater share is more likely to be undertaken by females rather than males [23]. Conversely males tend to attend to matters of family finances. These factors, coupled with the additional family pressures associated with the festive season at the end of 1990, may have led a significant number of females to become overwhelmed by the enormity of juggling personal, family and military tasks in the short pre-deployment time. Females were the most likely non-recipients of advice for their domestic affairs, but female Reservists were those most likely to have reported adverse stress effects from undertaking them. The latter took the form of anticipatory morbid thoughts of death and injury when making wills or taking out new or additional insurance. It seems plausible that the lack of adverse effects from domestic preparations in VS TA females could have been influenced by their close alignment with males through shared military training and roles; mutual commitment to the TA’s organisational requirements, and their self-confidence in having relatively unproblematic and in-place preparations. Additionally, Wood [24] suggest that females can learn male dominance behaviours through shared training, which in turn can lead to greater gender equality [24].

In this study, those with a shorter military service were more likely to have had less advice for domestic preparations than those with a longer service. This is not dissimilar to the findings of McCubbin [25] who found that younger service personnel (i.e., by default, those who are the most likely to have a shorter military service experience) were those who tended to avoid formal and informal advice. Case [26] in reviewing the knowledge-base for people’s assessment of threat report that the uptake of information is determined by the nature of the stressor, the would-be recipient’s appreciation of the effectiveness of responses to the threat (response efficacy), and their beliefs about their own ability to carry out effective responses (self-efficacy) [26]. Thus, it seems that HPVs with shorter service time could have had less anticipatory understanding about warfare; less recourse to war-related advice, and less belief that such advice could make a difference to their actions. For them, advice could have seemed irrelevant. In a study of US females deployed to the more recent Iraq and Afghanistan wars, Carter-Visscher [27] reported that females perceived themselves as having a lower level of preparedness for deployment and exhibited greater pre-deployment concerns about family than males [27]. These findings re-echo some of the present study’s gender findings, despite differences in sampling, military structures and cultures.

Pincus [28] notes that as the military person becomes more involved with military preparations for deployment so too is there a gradual withdrawal from family up to the date of departure [28]. Although the importance of the provision of military support to families prior to and during the time of military separation has been emphasised by many authors before the GW [7-10], there is little evidence of any prioritisation for the issue of British military advice for managing social relationships before departure to the GW. Less than ten per cent of the HPVs received advice for the management of their social relationships prior to departure (even though the pilot study respondents raised it as an available form of military advice). However, had it been received, the non-recipient HPVs believed that the pre-departure strain on family relationships, arising all be it understandably from the HPVs’ self-confessed war-focused attitudes since call-up, could have been eased. Others hypothesised that had it been received, it could have reduced the inter-personal tensions reported in other parts of this study concerned with the HPVs’ entry into new military groups during pre-deployment and later during deployment. The paucity of such advice could be of relevance to other published data from this study whereby it has been suggested that the HPVs’ lack of stress management training from the military during pre-deployment [22] showed a tendency towards avoidance by the military of issues that were perceived to be of ‘psychosocial’ origins.

It is not possible from these data to quantify whether the receipt or not of either form of advice is related to: its availability from the military; the ability and desire of the individual to access it; the receptiveness of the individual’s open or closed mind towards its content; avoidance or denial of its context, or anticipation of its relevance to a given situation [29]. For these, further research with the close co-operation of the military would be necessary. Certainly, as the receipt or not by the HPVs of advice for domestic preparations was not significantly associated with its effects, this could suggest that even when there was receipt of this form of advice, it did not appear to act as a stress moderator, as previously reported in a study of the receipt of health care advice [30]. Furthermore, in comparative research by Sharpley [31], no evidence was found that military pre-deployment stress briefings reduced psychological stress [31]. It could be argued that advice for social relationships from any source was so low that it is impossible to determine its therapeutic value, but the HPVs’ recommendations were clear that more effort should be made by the military to target audiences where there is likely to be the most need; and that the form of the advice (content, presentation), and logistics (its timing) are tailored to meet the reality of their needs.

Limitations

The study in its entirety is believed to be one of the earliest of the British GW studies and although some 28 years have passed since the War’s end and the study’s data collections began, interest in the GW and its unique circumstances (including the unresolved illness in some veteran troops) has not waned. Indeed, unlike this study, many British Gulf War studies have been based upon data collected not months but many years after the GW. Such lengthy delays have been recognised as raising the possibility of increasing error in participants’ recall [32,33]. As with many studies that seek to explore, describe and explain unforeseen life events (and including aspects of warfare), the ideal of representative samples and controls before, during and after such events [34] was neither feasible nor realistic for the present study. It is acknowledged that the non-random sample selection could have caused bias but it is believed that the efforts to ‘engineer’ the same-subject sample with participant representation in the key military dimensions of military category (Reserve/ VS), deployment category (called up/ volunteer) and GW occupation (nurses/ CMTS/ other health professionals), go some way towards lessening this potential effect. It can also be suggested that the study’s reliability is strengthened by the high ‘acceptance to participate’ of the HPVs (71%) and the high HPV participation retention level (90.5%) across the 18 months of the duration of the study.

Conclusions

Although those in the TA were comparatively well organised for the GW due to their annual domestic preparations for military exercises, this was not the case for some of the female Reservists who qualitatively showed morbid stress responses to their preparations. Overall females and those with a shorter military service were the least likely to have received this form of advice. Advice for the management of social relationships with families and with new military groups during the pre-deployment phase did not appear to have been recognised by the military as areas where advice could be useful. In contrast, veterans were clear in their recommendations as to how future need for advice for these social relationship’s difficulties could be met. We suggest that listening to the voices of those who have experienced warfare can better support the development of advice with relevant content and an efficacious mode of delivery in the future. By doing so, some of the stress of pre-deployment could be reduced.

Read More about Lupine Publishers Journal of Research & Reviews Please Click on Below Link:
https://lupine-publishers-research.blogspot.com/

Saturday, 21 January 2023

Lupine Publishers | Keratin

 Lupine Publishers | Journal of Research and Reviews on Health Care


Abstract

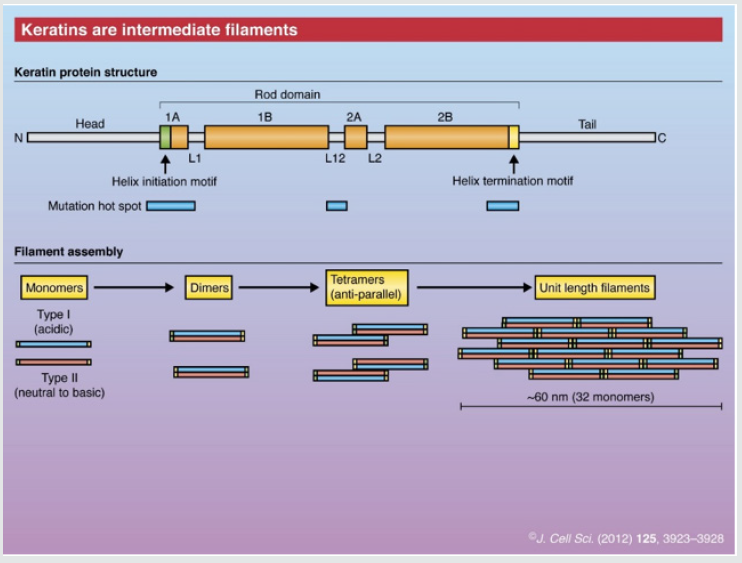
Eating foods high in protein gives the body the amino acids it needs to make keratin. Red meat, fish, chicken, pork, eggs, milk and yogurt all protein rich. The best plant sources of protein include beans, nut, Nat butters and quinoa. Most adults need two to three servings of protein each day to meet their daily requirements. Keratin is more of a restorative treatment borday says “Elen if you have a good hair type, it still strengthens the hair shaft and makes your hair mover salient. Sadock recommends checking with a demonologist before getting a keratin treatment if you have protasis or seborrheic dermatitis (Figure 1).

Figure 1.

Lupinepublishers-openaccess-Research-Reviews

Keywords: Foods; Protein; Nut Butters; Strengthens; Keratin

Introduction

“Keratin treatment” has become the term of choice for hair- smoothing processes that leave your hair frizz-free for weeks (even months) but forget about the word keratin. “It’s just a make ting buzz word – it’s not doing anything to smooth the hair”, first, a quick chemistry lesson. Think of straight hair as a lader and curly hair as a spiral staircase. The steps on both are the hair’s bonds. If you break those bonds, you can rebuild the spiral stair case as ladder so curly hair becomes straight. Ammonium thiol collate and sodium hydroxide permanently break the bonds that’s how traditional relaxers and “jopynose straightening” treatments transform the texture of the hair, “these treatments last until your hair grows out, bat they can be damaging, say schaeller. (And they will subject you to a very awkward growing-out phase.) some “keratin treatment” (and the popular brozillinbleu out original solution) saturate the hair with of onal dehyde solution before its dried and flat ironed; the format dehyde (yes, it’s a suspected cancer gen for human) looks the hair into that straighter positions. Its stays smooth beyond your next shampoo. Your natural texture then gradually returns over two five months.

Materials and Methods

Keratin treatments won’t make your hair break, but the flatironing might. “The hair breakage has nothing to do with the treatments and everything to do with the flat irons that are used to dry and seal the hair a fleruard”, some stylists may use a flat iron that is way too hot and scorches hair making it break off”. Think of straight hair as a ladder and curly hair as a spiral staircase. The steps on both are the hair’s bonds. If you break those bonds. You can rebuild the spiral staircase as ladder-so curly hair becomes straight. No hair treatment will technically contain formaldehyde (because a little more chemistry you it’s a gas). What they are able contain are methylene glycol, formalin, methanol, and methane did – ingredients that release formaldehyde when heated or mixed with water. Several new hairs-smoothing treatments use glyoxylic acid (or a derivative of it) to lock the hair into a straighter position. Results don’t usually last more than two or three months and these treatments won’t dramatically soften your curl pattern the way formaldehyde solution can.

Biotin-Rich Foods

Biotin is needed to metabolize the amino acids that create keratin and is generally recommended to strengthen hair and nails. Dietary sources of biotin contain nut, beans, wholegrains, caul flower and mushrooms.

Foods with Vitamin A

Vitamin A is needed for keratin synthesis good dietary sources of vitamin A contain orange fruits and vegetables like pumpkin, sweet potatoes, butternut squash, raw carrots and cantaloupe. Kedgerees like spinach, kale and collards are also high in vitamin A. Boost your hair, nails and skin from within care for your precious hair by eating the right vitamins and foods that increase keratin production. Included is knowledge on why keratin is important and which foods and vitamins will offer the best support.

Increasing Keratin Production

a. Fruit and vegetable: It aren’t a surprise that increase keratin production include fruits and veggies. Produce that orange, such as mangoes, carrots, sweet potatoes, and cantaloupe are high in carotene, which helps your body produce keratin. Carotene can also found in spinach, green peppers and squash.

b. Meat and dairy: Iron-rich protein can boost the production of keratin in the body and improve the health of skin, hair and nails, liver, fish and lean meats build keratin in your body.

c. Iron rich foods: Iron-rich animal protein includes turkey, duck, chicken, pork, shrimp, eggs, lean beef and lamb. Plant foods that contain iron-rich protein include beans, spinach, black-eyed peas, soybeans, to fuand lenticls.

d. Vitamin C: foods rich in vitamin C include brocade, frazzles sprouts, kale, peppers, guava, papaya, grape fruit, oranges, pine apples, strawberries and lemons.

e. B vitamins: Foods with folate include a meal, fortified whole grain cereal, spinach, beets, parsnips, broccoli, okra, black-eye peas and soybeans.

f. Zinc: Consume foods with zinc, such as asters, crab, pork, ronde lain, turkey, veal, chicken, peanut butter, wheatgerm and chick peas.

Result and Discussion

Keratin treatments won’t make your hair break, but the flat-ironing might. No Nair treatment with technically contain formaldehyde (because - a little more chemistry you it’s a gas). Results don’t usually last more than two- or three-month biotin contain nut, beans, wholegrains, cauliflower and mushrooms. Vitamin A contain orange fruits and vegetables.

a. Like pumpkin, sweet potatoes.

b. Fruit vegetables

c. Spinach, green peppers and squash.

d. Meat and dour: liver, fish and lean meats build keratin in body.

e. Iron: beans, spinach, black-eyed peas, soybeans, tufa and lentils.

f. Vitamin C: include: broccoli, brussels sprouts kale, peppers, guava, papaya.

g. B vitamin: broccoli, okra, black-eye peas and soybeans.

h. Zink: turkey, veal, chicken, peanut, wheatgerm and chick peas.

Acknowledgement

I am thanking of my mother and father that support me. And news agency (Mehri, Fars, Isnad, Iran, Mojo, mina) and (Aftab- Yazd, redeemer, Khorasan) that published my subject science. And journal healthy house plant (Mrs. Julie Boudin Davis. of Dr. Alfred French and thanks that accepted my abstract for meeting. Of Prof. Hermann Hege am thanks that my subject used on university kiel Germany. Of kew garden (UK) am thanks that every month send your newsletter.

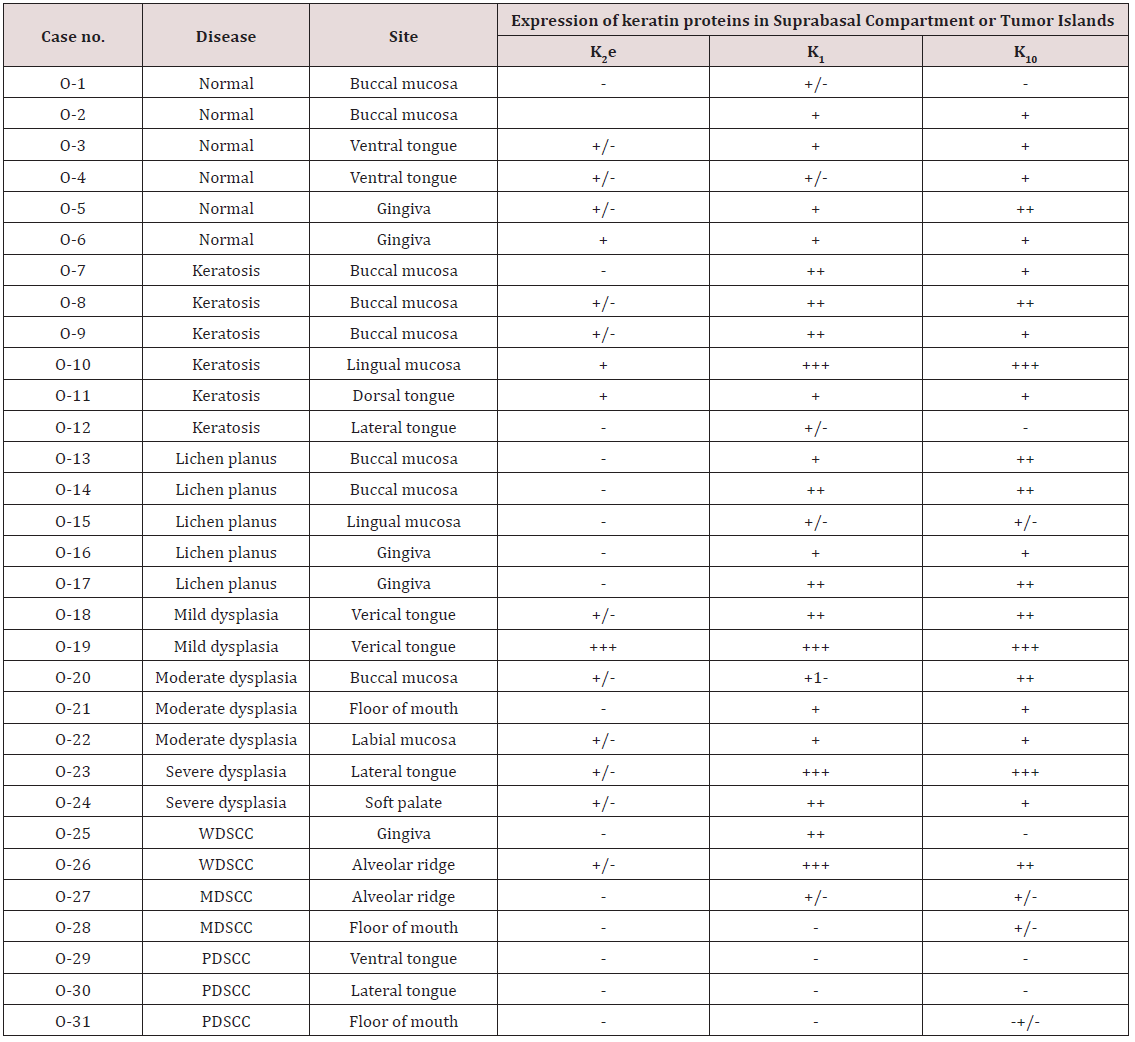
On finish of aces that every day send abstract journal and I was support to (Figure 2) and (Table 1).

Figure 2.

Lupinepublishers-openaccess-Research-Reviews

Table 1

Lupinepublishers-openaccess-Research-Reviews

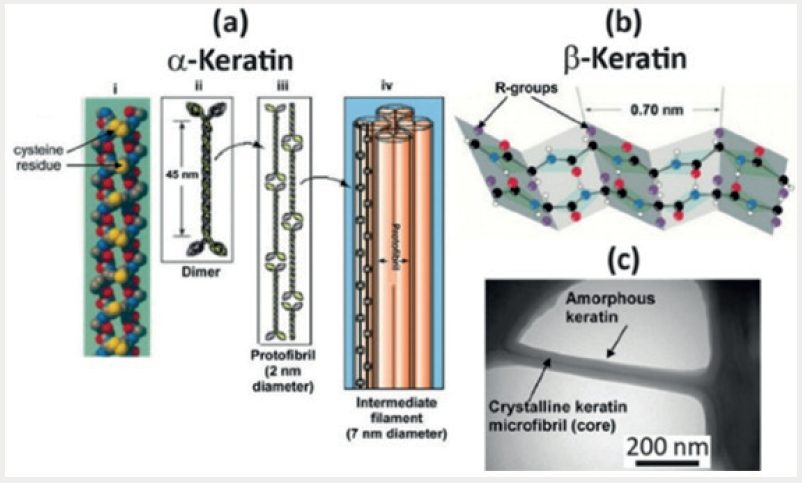
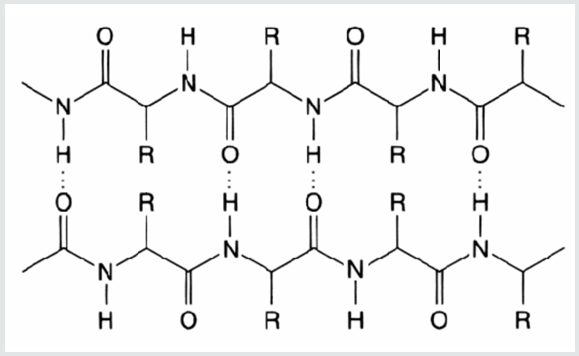
Aspergillus Niger is one of the most important microorganisms in biotechnology. It has been already used to produce extracellular enzymes such as glucose oxidase, pectinase, α-amylase and glucoamylase, organic acids, and recombinant proteins. In addition, A. Niger is used for bio transformations and waste treatment [1-3]. Among the various enzymes produced by the fungus are included proteases. The major extracellular proteolytic activities in A. Niger appear to be due to acid proteases [4]. Acid proteases [E.C.3.4.23] are endopeptidases that depend on aspartic acid residues for their catalytic activity and show maximal activity at low ph. These enzymes offer a variety of applications in the food, beverage industry, and medicine [5]. Keratin is a fibrous protein that occurs in vertebrates and exerts protective and structural functions. It is the major component of feathers, wool, scales, hair, stratum corneum, horns, scalps, and nails [6]. Keratin is insoluble and presents high mechanic resistance, as well as recalcitrance to common proteolytic enzymes like pepsin, trypsin, and papain [7]. This resistance is because of the tight folding of protein chain in α-helix (α-keratin) and β-sheets (β-keratin) in a super-coiled polypeptide chain, kept by strong association by disulfide bonds [8,9]. Keratinases [EC 3.4.21/24/99.11] are specific proteases that display the capability of keratin degradation. These enzymes are gaining importance in the last years, with many applications associated with hydrolysis of keratinous substrates, mainly byproducts of agroindustry processes [10]. Generally, keratinases have optimum pH from neutral to alkaline [11]. The utilization of agroindustry wastes may represent an added value to the industry and meets the increasing awareness for energy conserving and recycling [12]. This fact stimulates the investigation for alternatives to convert keratinous waste into valuable products [10]. One example is the poultry industry that generates huge number of byproducts, which may represent a potential environmental hazard if they are incorrectly destined or processed. The processing and/ or treatment of slaughterhouse waste have been one of the great concerns of poultry industry, mainly because of the restrictions on environmental questions [13]. In this work, the production of proteolytic enzymes by a new keratinolytic strain of A. Niger was investigated. The enzyme activity was partially characterized, and a culture medium based on keratinous substrate was selected, evaluating the influence of growth substrate concentration and medium pH on the production of proteolytic enzymes (Figure 3).

Saturday, 19 November 2022

Lupine Publishers | Relationship of Blood Group with Rice Likeliness

 Lupine Publishers | Journal of Research & Reviews Healthcare


Abstract

The main objective of the recent study was to interlink blood grouping with rice likeliness. The subjects who participated in this study were 146. The subjects were the students of Bahauddin Zakariya University Multan (Pakistan). The blood group of any individual is controlled by his gene which is the main concern of classical genetics. Rh illustrates the presence or absence of negative factor which is known as “Rhesus factor”. Rice is most favorable foods especially in India and Pakistan and also available at comparatively cheaper rates. Therefore, more people like to eat rice. By using MS- Excel I performed the statistical analysis about this study. Questionnaire based study revealed an important advancement in current researches.

Keywords: Blood Grouping; Brown Rice; Antigens; Staple Food; Classical Genetics

Introduction

The blood group of any individual is controlled by his gene which is the main concern of classical genetics. There are different types of blood group system but the most common is ABO. It is discovered by Karl Landsteiner in 1901. The ABO blood group system is controlled by three alleles of the same gene. It is also identified in some individuals of the animal kingdom such as bonobos, apes gorillas and rodents. Blood group A is controlled by the allele IA but allele IB gives the phenotype of blood group B, and type O is determined by allele ii. Blood group of a person remains the same throughout his life because it is the inherited trait [1]. Rh is the second very important type of blood group system. It illustrates the presence or absence of negative factor which is known as “Rhesus factor”. It was also determined by Karl Landsteiner [2]. Rice is one of the most favorable and staple foods especially in Asian countries, and also available at comparatively cheaper rates. In India and Pakistan, restricting rice eating is really next to impossible, but yes how you eat or cook rice, type of rice used does matters a lot when we consider rice benefits. Many people are rice lovers in such a way they always ready to eat rice in every condition such as illness, tension and depression. When they want to change their taste or mood, they wish to eat rice. They feel everything tasteless except rice in this condition. But it is the controversial issue for eating rice. Some people think rice is a light food and can be eaten by everyone in every situation. But some other people have conflict about this idea because they think that weight is gained by eating rice. However, those people who like the rice , eat rice without any danger. Therefore, more people like to eat rice.

Objective

Objective of the present study was to correlate blood grouping with rice likeliness.

Materials and Methods

There were 146 subjects who participated in this study. The subjects were the students of Bahauddin Zakariya University Multan (Pakistan)

Blood Grouping

In blood grouping, first of all, blood was collected from the body of different people by a needle known as lancet. Then, this blood was put on the glass slide and antiserums of antigens are mixed with this blood. A chemical reaction occurred that illustrates that this person has this type of blood group. If the red blood cells of the individual get clump with antibodies, it shows that this is the blood of that person.

Project Designing

A question was thought that why different people have different choices about the same thing. To solve this problem, it was thought that either it may have relation with blood group. That is why a lot of people were questioned about their type of blood group and point of view about rice. These were 146 subjects who told about their choices. All of them have different choices but people with B+ blood group were more rice lover. In this way blood group was correlated with rice likeliness.

Statistical Analysis

By using MS-Excel I performed the statistical analysis about this study.

Results

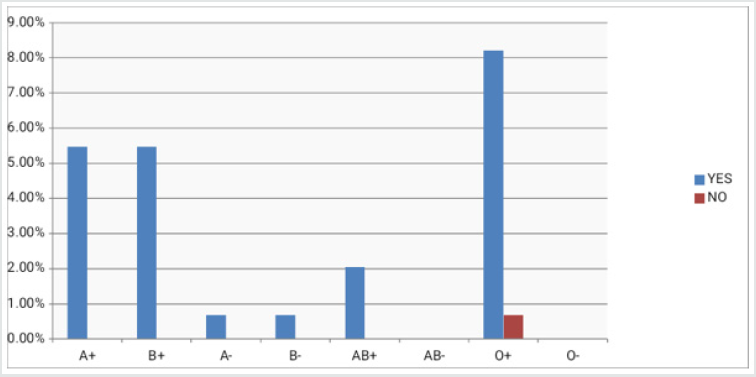
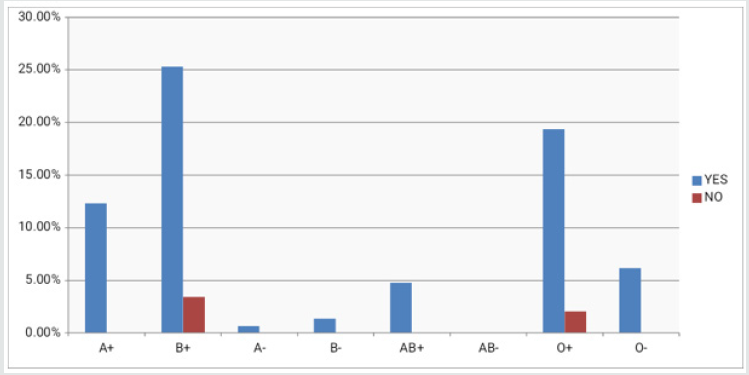
Relationship of blood group with rice likeness is given as below: (Graphs 1& 2).

Graph 1: Graph-1 for Male.

Lupinepublishers-openaccess-Research-Reviews

Graph 2:Graph for Female.

Lupinepublishers-openaccess-Research-Reviews

Discussion

The Questionnaire based study revealed an important advancement in current researches [3-10]. Most of the people studied about this topic. But all have different point of views about rice likeness. Venkatraman Sivasankaran said that it’s the climate that decides the food of people. So due to have specific pattern of climate, people like to eat rice. Aniruddha Banerjee said that most people like to eat rice because they cultivated much more rice in their own field.

Conclusion

From this study, it was concluded that people with B+ blood group are more rice lover but those who have AB- are least lover.

Read More About Lupine Publishers Journal of Research & Reviews Please Click on Below Link:
https://lupine-publishers-research.blogspot.com/

Friday, 24 June 2022

Lupine Publishers | To Examine the Relationship and Strength of Alcohol-Related Intimate Partner Violence in sub-Saharan Africa

 Lupine Publishers | Journal of Research & Reviews


Abstract

Alcohol-related intimate partner violence (IPV) is a serious public health issue which has attracted a lot of research and debates. While some studies have reported the relationship between alcohol and IPV to be linear, others have reported threshold effects. While some studies have found the link to be strong, others have reported weak or no association. Using Logistic regression and meta-analysis, the relationship, strength of relationship and possible moderators of the alcohol-IPV link are investigated in ten sub-Saharan African countries. The results indicates that while alcohol consumption is associated with IPV in three of the countries, alcohol abuse was associated with IPV in the other seven countries lending support for both the linear and threshold effects in sub-Saharan Africa. The meta-analysis showed a strong association between alcohol and physical IPV while a weaker association was observed for the alcohol- sexual IPV link. Moderator analysis showed that the strength of the alcohol-IPV link in sub-Saharan Africa varies with wealth index, marital length, and marital status, and jealousy, place of residence and justification of the use of violence. The nature of moderation was different between countries. The results of this study can be applied to plan country specific and multi-faceted intervention programs.

Keywords: Alcohol; Intimate Partners; Violence; Sub-Saharan Africa

Introduction

Intimate partner violence (IPV) is defined as any physical, psy-chological or sexual harm that is caused by the actions of a present or previous intimate partner [1]. It a major public health issue and violates women's human rights [1]. Cross sectional studies have shown that 10-69 per cent of women of reproductive age experience physical violence at least once in their lifetime while 6-59% report an attempt or actual sexual violence by their intimate partners [2]. Intimate partner violence takes place in all backgrounds and among all socioeconomic, religious and cultural groups with women bearing the global burden [1]. Prevalent rates are different across countries with rates between 11-52% in developing coun-tries [3]. IPV has been reported to lead to physical injuries, loss of pregnancy and complications during pregnancy [2]. It can also result in emotional problems such as depression and suicide [2] and victims have been reported to resort to use of drugs and alcohol as a means of coping with the abuse [4].

Several risk factors such as young age, low education, occu-pation, experiencing parental violence, drug and alcohol use, con-trolling behaviour by the husband [5], justification of wife beating [6] and so on has been reported to increase the odds of IPV; of these, alcohol consumption has been consistently implicated [2,7] with the prevalence of alcohol-related IPV differing in diverse countries [2]. Although an association between alcohol and IPV has been established in previous studies, there are arguments on the role of alcohol in IPV, the effect of alcohol and the strength of the association between alcohol and IPV. Although alcohol-related IPV is a widely researched topic, only some research has been done in sub-Saharan Africa [8,9] and none has investigated the magnitude of the association across countries in Sub-Saharan Africa. The aim of this study was to determine the type of association between alcohol and IPV in sub-Saharan Africa and also examine the strength of the relationship between alcohol and IPV in Sub-Saharan Africa.

Methodology

For the quantitative study, secondary analysis and meta-analy-sis were used to analyze cross-sectional data from the demographic and health surveys of ten countries in sub-Saharan Africa (Burkina Faso, Ghana, Kenya, Liberia, Malawi, Nigeria, Sao Tome and Prin-cipe, Tanzania, Zambia and Zimbabwe). Since the aim of this re-search was to determine the relationship between alcohol and IPV in sub-Saharan Africa, a quantitative research design was adopted because it is an appropriate method for showing associations and quantifying relationships between variables [10]. In order to examine the relationship and moderators of the alcohol-IPV link in sub-Saharan Africa, a secondary analysis of previously conducted primary studies of ten countries in sub-Saharan Africa was carried out. This is the method of choice for this research as it takes a cross national perspective which requires that data from several countries in sub-Saharan Africa be analysed. Data sets for this study were also easier to access and raise little or no ethical issues as re-spondents are already made anonymous.

Data Collection Methods

This study did not collect primary data but accessed data of the demographic and health survey of ten sub-Saharan Africa countries (Burkina Faso, Ghana, Kenya, Liberia, Malawi, Nigeria, Sao Tome and Principe, Tanzania, Zambia and Zimbabwe). Large sample sizes were used with high response rate thereby ensuring that statistically significant relationships are detected. Access to the data sets was gained by requesting permission from Demographic and Health Survey (DHS). Approval from DHS was granted by email. Data was identified using the domestic violence questionnaire. The identified data sets were downloaded to the researcher's personal computer using SPSS (version 19) software. Variables in the study were identified using the DHS recode manual.

Sample/Sampling Strategy

This study used quota sampling to identify DHS surveys con-ducted between 2006 and 2011 made available by 2012 in sub-Sa-haran Africa. For this research, only countries from sub-Saharan Af-rica were included because the main independent variable (alcohol consumption) was not measured in North African countries as con-sumption is prohibited. The data for each country was the most re-cent. This was to ensure that results reflected the current strength of the alcohol-IPV link and that recommendations are made based on current evidence. All datasets included asked questions on domestic violence and covered the topic of alcohol consumption and frequency at which husband/partner gets drunk because of the fact that the focus of this study is on alcohol-related IPV.

Data Analysis

Data analysis was carried out using SPSS (version 19.0) and Revman Meta-analysis software.

Univariate Analysis: Frequencies were used to determine the prevalence of the different forms of IPV, alcohol consumption and alcohol related IPV in the ten countries included in this study.

Logistic Regression: In order to determine the type of relationship between alcohol and intimate partner violence in sub-Saharan Africa, a logistic regression of the four category alcohol measure was carried out by comparing non-drinkers to drinkers (drinkers who never got drunk, who got drunk sometimes and those who got drunk often). Results are reported as B (Standard Error), odd ratios (OR) and 95%CI for OR. A significant Wald test p-value indicates a significant difference between the categories and non-drinkers.

Meta-Analysis: In order to investigate the strength of the alcohol-IPV link in sub-Saharan Africa, a meta-analysis was car-ried out using the Revman software. This was done by comparing non-abusers (non-drinkers and drinkers who never got drunk) and abusers of alcohol (husbands who got drunk sometimes and often). Based on the assumption that effects may vary across samples and studies [11], random effects model was used. The random effects model was used in this study because of the heterogeneous nature of the studies and because this model generates results that are generalisable to the sub-Saharan Africa population. The heteroge-neity of the result was investigated using the Cochran's Q test [12]. A significant I2 shows heterogeneity among included studies with higher values indicating increased differences within study [12]. Due to the high heterogeneity between countries included in the meta-analysis, further moderation analysis was carried out.

Hierarchical Logistic Regression: Using the method described by Field [13], hierarchical logistic regression was used to study the moderator effects of the independent variables on the al- cohol-IPV link. In order to account for the complex sampling used in the DHS survey, the probability of being administered the domestic violence questionnaire and to adjust for the probability of non-re-sponse [14]; all analyses were conducted using the domestic violence sample weight.

Ethical Issues

One of the ethical issues with conducting a secondary data anal-ysis is the permission to access datasets. Approval was sought by the researcher and access was granted. The DHS also operate a no data sharing policy. To ensure data protection, memory sticks and computers were password protected to guard against unauthorised access. It is also important to confirm that the data obtained from the primary study was ethically obtained. The primary DHS study was done with the informed consent of the subjects and confidenti-ality obtained with the National ethics committees of the different countries approving the surveys. Furthermore, the datasets have been made anonymous by removing all identifier information.

Results

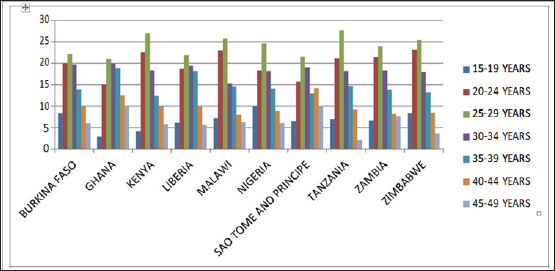
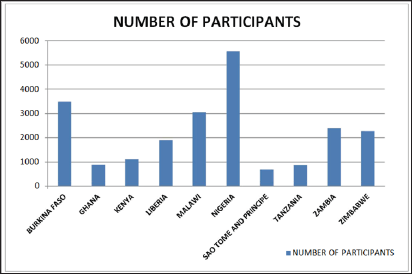
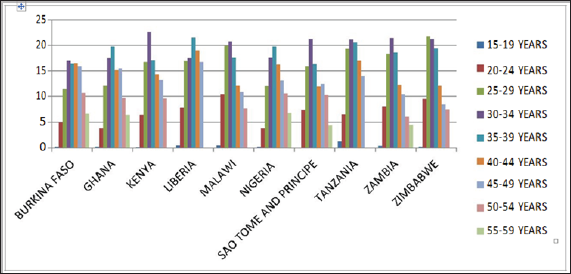
The study population consisted of women aged 15-49 years old and men aged 15-59 years old in ten countries in sub-Saharan Af-rica. Six hundred and eighty-two couples were interviewed in Sao Tome and Principe, 873 in Tanzania and 883 in Ghana. The largest numbers of 5566 couples were included in Nigeria while 3488 and 3051 couples participated in Burkina Faso and Malawi respectively (Figure 1). Of these numbers, the highest percentage of women were in the 25-29 years' age group with this group accounting for 22.1% of the women in Burkina Faso, 27% in Kenya, 25.8% in Malawi and 27.7% in Tanzania. For the men, 22.6%, 20.8%, 21.3% and 21.4% were in the 30-34 years' age group in Kenya, Malawi, Zimbabwe and Zambia respectively. In Ghana (19.8%), Liberia (21.5%) and Nigeria (19.8%), the highest proportion of the male participants were in the 35-39 years’ age group (Figures 2a & 2b).

Figure 1: Number of Participants in the Study.
Lupinepublishers-openaccess-Research-Reviews

Figure 2a: Age group of the Women

Lupinepublishers-openaccess-Research-Reviews

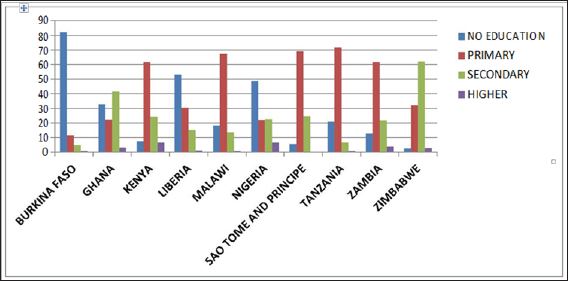
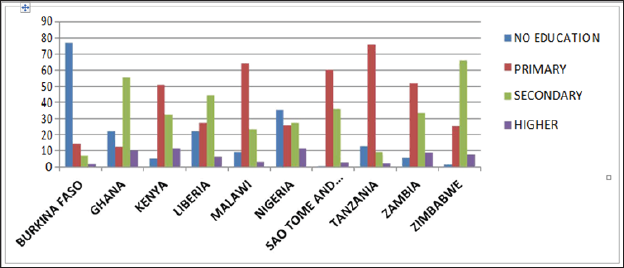
In Burkina Faso, 82.3% of the women had no education compared to 77.0% of the men. Zimbabwe and Sao Tome and Principe were found to have the highest number of couple who have had any form of education with 94.2% of the women and 99.4% of the men having a primary, secondary or higher education in Sao Tome and Principe. In Zimbabwe, only 2.7% of the women and 1.2% of the men have had no education at all. 5.2% of the women in Burkina Faso and 6.6% of the women in Tanzania reported having a second-ary education compared to 41.5% and 62.1% in Ghana and Zimbabwe respectively (Figures 3a & 3b).

Employment Status

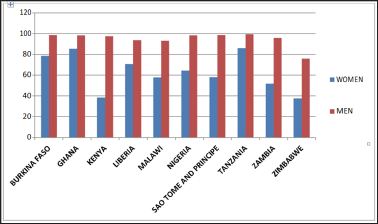
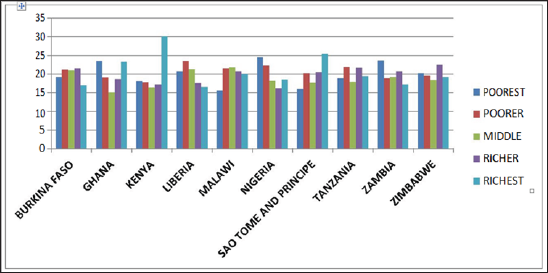
Highest proportions of women who are unemployed were in Zimbabwe, Kenya, Zambia and Malawi with 62.3%, 61.6%, 48.3% and 42.3% of the women reporting that they have no paid employment respectively. The highest number of women who were em- ployed was reported in Ghana (88.5%), Tanzania (86%), Burkina Faso (78.6%) and Nigeria (64.4%). For the men, the highest rate of unemployment was in Zimbabwe (24.2%), Malawi (6.9%) and Liberia (6.3%) (Figure 4). When wealth index was considered, Figures 5 show that 24.5% and 22.3% of Nigerians in the study population were in the poorest and poorer wealth indexes respectively. Kenya, Sao Tome and Ghana have the highest percentages of 30.2%, 25.4% and 23.4% of the couples in the richest wealth index while 21% of the couples in Burkina Faso, 21.4% in Liberia, 21.9% in Malawi and 19.2% in Zambia were in the middle wealth index.

Figure 2b: Age Group of the Men.
Lupinepublishers-openaccess-Research-Reviews

Figure 3A: Education Level of the Women.
Lupinepublishers-openaccess-Research-Reviews

Prevalence of Intimate Partner Violence

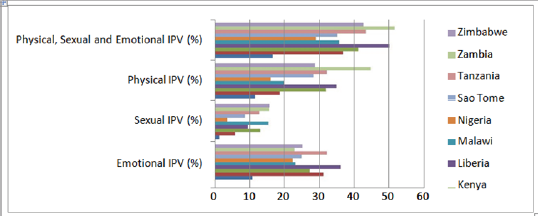
The prevalence of emotional IPV was lowest in Burkina Faso (10.8%) and highest in Liberia (36.3%). In Ghana, 31.4% of the women reported experiencing emotional IPV while 32.3% reported same in Burkina Faso. The percentage of emotional IPV is closest in Sao Tome and Principe and Zimbabwe with 25% of the women reporting emotional IPV in Sao Tome and Principe and 25.2% in Zimbabwe. The percentage of women who reported sexual IPV ranged from as low as 1.2% in Burkina Faso to as high as 15.8% in Zimbabwe. Figures in Zambia and Malawi are closest to Zimbabwe with 15.6% of the women in Zambia and 15.4% of the women in the study population experiencing sexual violence from their husbands or partners. Zambian women reported the highest prevalence of physical IPV (44.9%) while the lowest percentage of reported physical IPV was 11.5% in Burkina Faso.

Figure 3b: Education Level of the Men.
Lupinepublishers-openaccess-Research-Reviews

Figure 4: Employment Rate.

Lupinepublishers-openaccess-Research-Reviews

Figure 5: Wealth Index of Participants in the Study.
Lupinepublishers-openaccess-Research-Reviews

In Kenya and Liberia, 32% and 35% of the women reported physical IPV. When all three forms of IPV were considered, prevalence rate was highest in Zambia (51.9%) followed by Liberia (50.3%) and lowest in Burkina Faso (16.7%). In general, the prevalence of physical and emotional IPV were higher than that of sexual IPV indicating that women are less likely to experience or report sexual IPV in sub-Saharan Africa (Figure 6).

Figure 6: Prevalence of Intimate Partner Violence in sub -Saharan Africa.
Lupinepublishers-openaccess-Research-Reviews

Prevalence of Alcohol-Related Intimate Partner Violence

Figure 7: Prevalence of Intimate Partner Violence in sub -Saharan Africa.
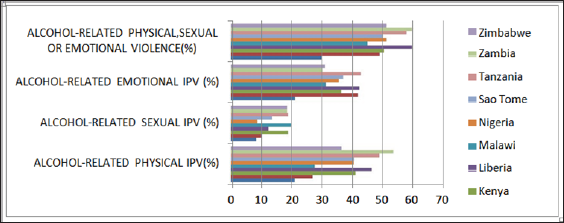
Lupinepublishers-openaccess-Research-Reviews

Figure 7 shows the prevalence of alcohol-related intimate part-ner violence among married and cohabiting women in sub-Saharan Africa. The prevalence of alcohol related physical IPV was between 21.2 to 53.9% in this study. The highest prevalence rate of alcohol-related sexual violence was 19.9% in Malawi while the lowest prevalence of 8.8% was reported in Nigeria. The prevalence of alcohol-related emotional IPV ranged from 21.3% in Burkina Faso to 43.1% in Tanzania. When all three forms of IPV were considered, prevalence rates ranged from as 16.7% in Burkina Faso to as high as 51.9% in Zambia.

Relationship between Alcohol and Intimate Partner Vi-olence

The relationship between alcohol and intimate partner violence was investigated by conducting a logistic regression of intimate partner violence (physical, sexual or emotional IPV) and the four level drinking variables. The significance of the effect of each level of the drinking variable on IPV was assessed using the Wald's test. Odd ratios (Exp B) with the 95% confidence intervals, standard error and Wald's test p values are presented. In Burkina Faso, the odds of women experiencing any form of IPV (physical, sexual or emotional IPV) is 1.7 times higher in women whose husbands never got drunk than in women whose husbands never drink while the odds of experiencing IPV is 2.23 (1.66-3.00) and 2.77 (1.82-4.21) greater in women whose husbands never got drunk compared to women whose husbands never drink in Nigeria and Sao Tome and Principe respectively. The Wald’s test shows that there is a significant difference in the odds of experiencing IPV by women whose husbands drink but never got drunk and women whose husbands never drink. The results show that in Burkina Faso, Nigeria and Sao Tome and Principe, alcohol consumption rather than alcohol abuse is associated with intimate partner violence indicating that there is a linear relationship between alcohol and IPV in these countries.

In Ghana, the odd of perpetrating intimate partner violence is 2.29 (1.66-3.16) in men who got drunk sometimes and 3.36 (2.04-5.54) in men who got drunk often compared to non-drinkers. While the OR for experience of intimate partner violence is 7.12 (4.3011.81) in women whose husbands often abuse alcohol in Kenya, the OR for IPV by women whose husbands often get drunk is 2.72 (1.81-4.08) in Liberia. In Malawi, husbands/partners who get drunk sometimes are 1.45 times more likely to abuse their partners compared to men husbands or partners who do not drink alcohol while the odds of perpetrating IPV is 4 times higher in husbands who get drunk often. Wald's test p values showed that there is no significant difference in the odds of women experiencing intimate partner violence in women whose husbands drink but never got drunk and women whose husbands never drink in Ghana, Kenya, Liberia, Malawi, Tanzania, Zambia and Zimbabwe. This indicates that it is alcohol abuse rather than drinking of alcohol that is associated with intimate partner violence. These full results are presented in Table 1 below.

Table 1: The effect of alcohol on intimate partner violence in sub
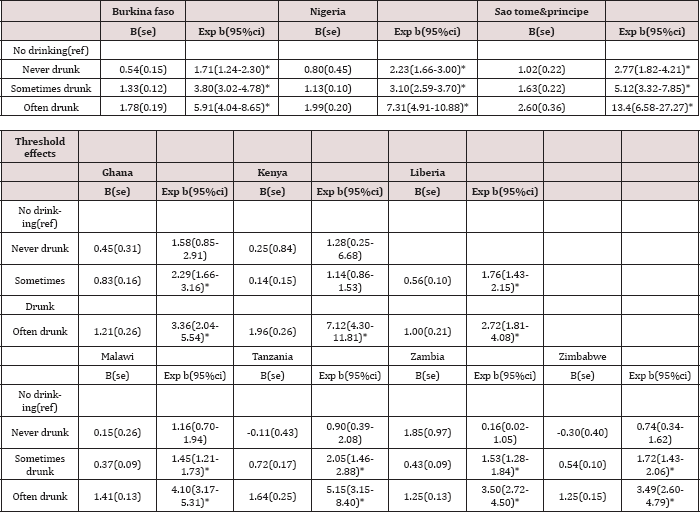
Lupinepublishers-openaccess-Research-Reviews

The Strength of the Alcohol-Intimate Partner Violence Link in sub-Saharan

a. Effect of Alcohol on Physical Intimate Partner Violence

Figure 8 showed the result of the meta-analysis to determine the strength of the alcohol-physical intimate partner violence in ten sub-Saharan Africa countries. A total of 22,120 participants were used in the study. Of these numbers, 6,271 were in the group of women whose husbands drink abuse alcohol while 15,849 were in the group of were in the group of women whose husbands/partners do not abuse alcohol. While 2,576 women reported experiencing physical intimate partner violence in the first group, a total of 2,698 women reported physical IPV in the other group. The results show the test for heterogeneity, I2=93% indicating a high degree of heterogeneity between the ten countries included in the analysis. The odds ratio is 2.91 (95% CI (2.24-3.79) showing that there is a strong association between alcohol and physical intimate partner violence in sub-Saharan Africa. The overall effect Z =7.96 and was statistically significant (p<0.00001). This indicates that the strength of the alcohol-physical IPV link is strong in sub-Saharan Africa.

Figure 8: Effect of Alcohol on Physical IPV in SSA.
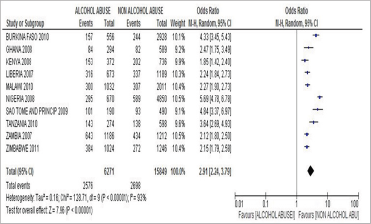
Lupinepublishers-openaccess-Research-Reviews

b. Effect of Alcohol on Sexual Intimate Partner Violence

The meta-analysis to determine the effect of alcohol on sexual IPV is presented in Figure 9. A total of 22,104 women were included in the study. 6,266 were in the alcohol abuse group while 15,838 were in the non- alcohol abuse group. Of the 6,266 women in the alcohol abuse group, 971 reported experiencing sexual IPV while 1,006 reported sexual IPV in the non-alcohol abuse group. The above results show an I2 value of 70% indicating heterogeneity between studies. An OR of 2.15 (95%CI=1.78-2.60) means that women in sub-Saharan Africa are two times more likely to report sexual violence when their husbands/partners abuse alcohol than when they do not. An odd ratio of 2.15 shows that there is a small effect size for the alcohol-sexual violence link in sub-Saharan Africa. The overall effect Z=7.87 (0.00001) is highly significant indicating that the effect of alcohol on IPV is highly significant. These results imply that the strength of the alcohol-sexual IPV link is weak in sub-Saharan Africa.

Figure 9: Effect of Alcohol on Sexual Intimate Partner Violence in sub-Saharan Africa.
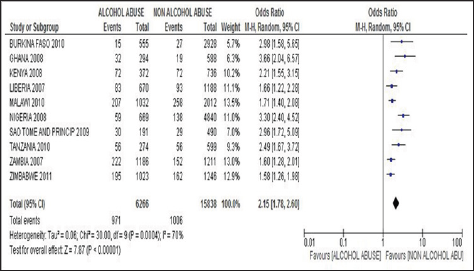
Lupinepublishers-openaccess-Research-Reviews

c. Effect of Alcohol on Emotional Intimate Partner Violence

A total of 22,112 respondents took part in the study to deter-mine the effect of alcohol on emotional intimate partner violence. A total of 5,151 participants reported experiencing emotional intimate partner violence. Of this number, 2,182 reported that their husbands abuse alcohol while 2,969 reported that their husbands never abuse alcohol. The result of the meta-analysis is presented in Figure 10 below. The results above show that women whose husbands abuse alcohol are 2.36 times more likely to report emotional intimate partner violence in sub-Saharan Africa OR=2.36 (95%1.96-2.83). This means that there is a moderate effect size for the association between alcohol and emotional intimate partner violence in sub-Saharan Africa. An I2 value of 85% indicates high heterogeneity between studies. The overall effect Z was highly significant (Z=9.15, p<0.00001)

Discussion

Prevalence of Intimate Partner Violence in SSA

In this study, the prevalence of physical intimate partner violence is 44.9% in Zambia, 28.9% in Zimbabwe and 19.9% in Mala wi. These values are similar to the 45%, 28% and 20% reported by Hindin et al. [15] for Zambia, Zimbabwe and Malawi respectively. On the other hand, the 32% and 32.2% prevalence rates reported for Kenya and Tanzania herein are lower than the 39% reported by Hindin et al. [15] and the 48% observed by Tumwesigye et al. [16] for Uganda which is a neighboring East African country. The percentage of physical IPV in other countries in this study ranged from between 11.5% in Burkina Faso to 28.5% in Sao Tome and Principe. While some of these rates are similar to figures reported in other sub-Saharan African countries, others are less. For instance, the 28.5% prevalence reported here is similar to the 29% reported for Rwanda [15]. However, the 11.5% reported for Burkina Faso is lower than rates reported anywhere in sub-Saharan Africa but similar to the 12% reported for Haiti [3]. These differences in prevalence rates may be as a result of the questions used to assess physical IPV.

Figure 10: Effect of Alcohol on Emotional Intimate Partner Violence in SSA.
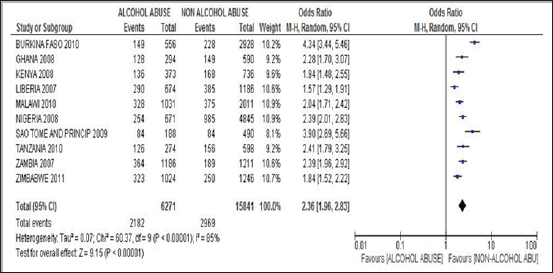
Lupinepublishers-openaccess-Research-Reviews

This study asked respondents whether husband/partner has ever threatened or attacked them with a gun/knife or other weapons while the Hindin et al. [15] separated this question into threat and actual attack. Combining these two questions would mean that women who have experienced both threat and the act can only give one response to both questions leading to the lower rates obtained in this study. In this study, 16.1% of women in Nigeria re-ported physical IPV. This is slightly higher than the 15% reported by Antai et al. [17] using the same study data. While the Antai et al. [17] study used the individual recode which is a sample of legally married women, the present study used a sample of currently married/cohabiting women. This is consistent with findings that the prevalence of IPV is higher in currently married than legally married women [15]. In spite of these observed differences in the prevalence of physical IPV in some sub-Saharan African countries in this study, the observed prevalence of 11.5 to 44.9% in this study is consistent with that reported in other studies [2,3,16-18].

Apart from physical IPV, the prevalence of sexual and emotion-al IPV was also examined. Results indicated that the rates of sexual IPV ranged from 1.2% in Burkina Faso to 15.8% in Zimbabwe. These rates are similar to the 3 to 16% prevalence rates reported in existing literatures for sub-Saharan Africa [15,17]. The prevalence of emotional IPV in this study ranged from 10.8% in Burkina Faso to 36.3% in Liberia. This is higher than the prevalence rates of 10.4 to 22.7% reported elsewhere [19]. When all three forms of IPV were considered, the prevalence rates increased for all ten countries and were higher than that reported in previous studies. For example, Hindin et al. [15] reported a prevalence of 45% for Zambia in their studies while this study shows a prevalence of 51.9% for Zambia when all forms of IPV were considered. It can thus be argued that studies investigating only one form of IPV result in an under estimation of the magnitude of IPV. Overall, the prevalence of sexual violence in this study was consistently lower than that reported for physical and emotional violence across all countries included in this work.

Prevalence of Alcohol-Related Intimate Partner Violence

The prevalence of alcohol IPV was between 29.9% to 60.1% when of physical, sexual or emotional IPV is considered. These rates are higher than the 33.9 to 49.5% reported for countries in sub-Saharan Africa [15,16] and 10.5 to 55% reported elsewhere [2]. However, this is lower than the 65% rate reported in South Africa [2]. The higher rates reported in this study is as a result of the fact that this study investigated the experience of all three forms of IPV indicating that previous studies may have been subject to an under reporting of prevalence rates of IPV as only physical or sexual IPV are usually investigated. The lower prevalence of alcohol-related IPV in this study compared to the 65% prevalence reported in South Africa can be explained by the fact that while the present study investigated the prevalence of women ever experiencing alcohol-related IPV, the South African study reported prevalence for the past twelve months.

Following the same trend as IPV, it is possible that the occur-rence of current alcohol-related violence may be higher than past occurrence. Women who have experienced alcohol-related violence may recall these incidents more since they are more recent than if they took place a long time ago. Another possible explanation for this is that in South Africa, it is believed that alcohol causes aggres-sion and this has led men to drink in order to carry out violent acts [2] thereby increasing the rate of alcohol-related violence in South Africa compared to other sub-Saharan African countries.

The Relationship between Alcohol and Intimate Partner Violence in SSA

In all ten countries, alcohol was consistently linked to women's experience of intimate partner violence with the nature of the re-lationship varying across different countries. The findings of this study showed that in seven out of the eleven countries (Ghana, Ken-ya, Liberia, Malawi, Tanzania, Zambia and Zimbabwe), there was no significant difference in the odds of experiencing IPV in women whose husbands/partners never consumed alcohol and those whose husbands/partners never got drunk. This is consistent with the findings in several literatures [2,3,16]. This can be explained by the fact that for alcohol to significantly increase the odds of perpetrating intimate partner violence, alcohol consumption has to surpass a particular amount or rate of consumption.

This explanation is consistent with that put forward by propo-nents of the threshold effect who argue that it is not alcohol con-sumption per se that contributes to intimate partner violence but alcohol abuse. Conversely, in Burkina Faso, Nigeria and Sao Tome and Principe, women whose husbands consumed alcohol but never got drunk were significantly more likely to experience any of physical, sexual or emotional intimate partner violence than women whose husbands never consumed alcohol. This is similar to the report of Bangdiwala et al. [20] who reported a strong linear re-lationship for the alcohol-IPV link. These results are in agreement with the justification put forward by the proponents of the linear effect conceptualization who maintain that alcohol abuse increases the odds of intimate partner violence and that these odds increases with increase in the quantity of alcohol consumed.

In Kenya alone, the odds of alcohol increasing the odds of in-timate partner violence only reached statistical significance in the women whose husbands/partners often got drunk. This indicates that in Kenya, it is the frequency of alcohol abuse and not abuse alone that contributes to the alcohol-IPV link. Drawing from the multiple threshold conceptualisation [21], it is possible that the likelihood of experiencing intimate partner violence in Kenya is already very high that alcohol consumption or less frequent alcohol abuse does not significantly contribute to an increased odd of intimate partner violence while more frequent alcohol abuse may increase the frequency and severity of intimate partner violence in this sample thereby increasing the likelihood of intimate partner violence in this group.

The findings of this study support both the linear and threshold conceptualisation of the alcohol-IPV link. This suggests that the type of relationship between alcohol and intimate partner violence varies across countries in sub-Saharan Africa with most countries showing a threshold effect. This observed difference could be as a result of differences in drinking pattern. In the seven countries where threshold effects were observed, large percentages (86.3 to 99.1%) of men who drink get drunken showing drinking cultures that are supportive of alcohol abuse.

Strength of Alcohol-Intimate Partner Violence Link in SSA

A meta-analysis of the ten countries included in this study showed an odds ratio of 2.91 (95%CI, 2.24-3.39) for physical IPV which shows that women whose husbands abuse alcohol are almost thrice as likely to experience IPV than women whose husbands do not abuse alcohol. This shows a strong association between alcohol and intimate partner violence in sub-Saharan Africa. This is consistent with the strong association reported in a meta-analysis by Gil-Gonzalez et al. [22]. The strong association between alcohol and physical IPV in this study can be explained by the culture of masculinity in sub-Saharan Africa. It is considered masculine for men to drink and it is also seen as a thing of pride for a man to be feared and respected by his wife. It is also generally acceptable for men to physically reprimand their wives if they feel that the women have erred in anyway.

On the other hand, a small but significant relationship was observed for alcohol and sexual intimate partner violence in this study. This is similar to the report of Tang and Lai [23] who report-ed a significant but weak association between alcohol abuse and sexual intimate partner violence. This weak association could be as a result of the fact that in African society, sex is considered a private matter not to be discussed with strangers. There is also shame as-sociated with being raped and made to perform unwanted sexual acts and women are often blamed for it and this may result in under reporting. Women may also consider that being made to perform any form of sexual act is acceptable so long as it is within a marriage or committed relationship and may not consider this as IPV. For example, it is commonly believed in Africa that a man cannot rape his wife. Hence forced sexual intercourse in a marriage is not considered rape but seen as a normal part of the relationship. When the severity of intimate partner. Based on the results from this re-search, it can be argued that the strength of the alcohol-IPV link in sub-Saharan Africa depends on the type of IPV measured.

Conclusion

The purpose of this research work is to identify the relationship, strength of relationship between alcohol and intimate partner violence in sub-Saharan Africa. Results of this study show that alcohol is consistently associated with intimate partner violence in all ten countries included in this study with the strength of this relationship depending on the form of intimate partner violence. While a linear relationship was found between alcohol and intimate partner violence in Burkina Faso, Nigeria and Sao Tome and Principe, a threshold effect was observed in the remaining seven countries with the odds of alcohol-related intimate partner violence increasing with increase in alcohol consumption and alcohol abuse. The strength of the alcohol-intimate partner violence link was also found to be dependent on the effects of other variables in some countries with the direction of moderation different in the countries where these moderation effects are present.

The results also show that when the three forms of IPV were measured, the prevalence of both IPV and alcohol-related IPV were higher than that of existing literatures suggesting that studies of IPV estimating only one or two forms of IPV are subject to under es-timation of the magnitude of his huge public health problem. These findings have potentially important implications for public health promotion, policy and practice. The implication of the findings of this research is that interventions for tackling alcohol-related IPV should be multifaceted and should address behavioural, cultural and social change

Study Limitations

Despite the above strengths, the result of this study should be interpreted bearing in mind several limitations. First, because the information on problem drinking was provided by women, there is the possibility of misclassification bias. Responses were not taken from men about their drinking and IPV perpetration and this would have been valuable in corroborating the women report. There is also a tendency for recall bias as IPV may have taken place at a different time from alcohol abuse. Classification of drinking as sometimes or often drunk makes the report subjective rather than objective and may have led to results showing a stronger relationship between alcohol and IPV in sub-Saharan Africa. This is because studies have shown that studies assessing alcohol abuse is more associated with IPV than those measuring quantities [24].

Even though the results of this research are to a great extent consistent with those reported for community samples in other studies, it cannot be generalised to clinical samples of alcohol abusers or IPV perpetrators because studies have shown that the magnitude of the association between alcohol and IPV is stronger in clinical than community samples [24]. Finally, because this study analysed data from cross sectional studies which are ecological in nature, it is difficult to know if problem drinking took place before IPV or vice versa. It is possible that perpetrators of IPV are more likely to misuse alcohol or that individual's use alcohol to cope with stressful life events hence causality cannot be assumed.

Read More about Lupine Publishers Journal of Research & Reviews Please Click on below Link:
https://lupine-publishers-research.blogspot.com/