The strategy of price liberalisation and Privatization had been
implemented in Sudan over the last decade and has had a
positive result on government deficit. The investment law approved
recently has good statements and rules on the above strategy in
particular to pharmacy regulations. Under the pressure of the new
privatization policy, the government introduced radical changes
in the pharmacy regulations. To improve the effectiveness of the public
pharmacy, resources should be switched towards areas
of need, reducing inequalities and promoting better health conditions.
Medicines are financed either through cost sharing or full
private. The role of the private services is significant. A review of
reform of financing medicines in Sudan is given in this study. Also,
it highlights the current drug supply system in the public sector, which
is currently responsibility of the Central Medical Supplies
Public Corporation (CMS). In Sudan, the researchers did not identify any
rigorous evaluations or quantitative studies about the
impact of drug regulations on the quality of medicines and how to
protect public health against counterfeit or low-quality medicines,
although it is practically possible. However, the regulations must be
continually evaluated to ensure the public health is protected
against by marketing high quality medicines rather than commercial
interests, and the drug companies are held accountable for
their conduct.
Keywords: Counterfeits Medicines; Drug Importers; Quality of Medicines; Regulatory Authorities
Abbrevations:CMSPO: Central Medical Supplies Public Organization; CRC: Centre of Regulation and Competition; DAP: Drug
Action Programme; DOP: Department of Pharmacy; FGDOP: Federal General Directorate of Pharmacy; FMOH: Federal Ministry of
Health; FPPB: Federal Pharmacy and Poison Board; GMP: Good Manufacturing Practice; KS: Khartoum State; MOAR: Ministry of
Animal Resources; MOH: Ministry of Health; NGOs: Non-Governmental Organizations; NDP: National Drug Policy; RDFs:
Revolving Drug Funds; SPSS: Statistical Package for Social Sciences; UK: United Kingdom; USA: United States of America; WHO:
World Health Organization.
Introduction
The World Health Organization [1] has defined drug regulation
as a process, which encompasses various activities, aimed at
promoting and protecting public health by ensuring the safety,
efficiency and quality of drugs, and appropriateness accuracy of
information [1]. Medicines regulation is a key instrument employed
by many governments to modify the behaviour of drug systems. The
regulation of pharmaceuticals relates to control of manufacturing
standards, the quality, the efficacy and safety of drugs, labelling
and information requirements, distribution procedures and
consumer prices [2]. To assure quality of medicines, in most
countries registration is required prior to the introduction of a
drug preparation into the market. The manufacturing, registration
and sale of drugs have been the subject of restricts regulations and
administrative procedures worldwide for decades [3]. Nobody
would seriously argue drugs should be proven to be 100% safe.
No set of regulations could achieve that goal argue, because it
is impossible, and all drugs carry some risk [4]. Stringent drug
regulation was introduced across many countries in the 1960s
following the thalidomide disaster and had since been embraced by
the industry as a commercial essential seal of safety and quality [5].
In spite of the measures, many countries, especially developing one
face a broader range of problems. In several developing countries
drug quality is a source of concern. There is a general feeling of
high incidence of drug preparations that are not of acceptable
quality [6]. For example, about 70% of counterfeit medicines
were reported by developing countries [7]. Reports from Asia, Africa, and South America indicate 10% to 50% of consider using
prescribed drugs in certain countries may be counterfeit [8]. For
instance, in Nigeria fake medicines may be more than 60 -70% of
the drugs in circulation [9], and 109 children died in 1990 after
being administered fake Paracetamol [10]. In Gambia the drug
registration and control system resulted in the elimination of ‘drug
peddlers’ and certain ‘obsolete and harmful’ drugs, as well as a large
decrease in the percentage of brand and combination drugs [11]).
The percentage of drugs failing quality control testing was found
to be zero in Colombia, but 92% in the private sector of Chad [12].
Hence, it is very difficult to obtain accurate data. The proportion of
counterfeit drugs in the USA marketplace is believed to be small -
less than 1 percent [12]. In [13] reported two cases of counterfeit
medicines that found their way into legitimate medicine supply
chain in the UK in 2004.
Poor quality drug preparations may lead to adverse clinical
results both in terms of low efficacy and in the development of drug
resistance [14]. Regulations are the basic devices employed by
most governments to protect the public health against substandard,
counterfeit, low quality medicines, and to control prices. Thorough
knowledge of whether these regulations produce the intended
effects or generate unexpected adverse consequences is critical. The
World Health Organization (WHO) undertook a number of initiatives
to improve medicines quality in its member states and promote
global mechanisms for regulating the quality of pharmaceutical
products in the international markets. Yet, there are not any WHO
guidelines on how to evaluate the impact of these regulations. There
are numerous reports concerning drug regulations [15], but the
published work on the impact of these regulations on the quality of
medicines moving in the international commerce has been scarce.
Findings from most published studies lack comparable quantitative
information that would allow for objective judging whether and
by how much progress on the various outcomes have been made
by the implementation of the pharmaceutical regulations. To
ignore evaluations and to implement drug regulation based on
logic and theory is to expose society to untried measures in the
same way patients were exposed to untested medicines [15].
The present policy of the national health-care system in Sudan is
based on ensuring the welfare of the Sudanese inhabitants through
increasing national production and upgrading the productivity of
individuals. A health development strategy has been formulated in
a way that realises the relevancy of health objectives to the main
goals of the national development plans. The strategy of Sudan at
the national level aims at developing the Primary Health Care (PHC)
services in the rural areas as well as urban areas. In Sudan 2567
physicians provide the public health services (554 specialists, 107
medical registrars, 1544 medical officers, 156 dentists, and 206
pharmacists) [16]. Methods of preventing and controlling health
problems are the following:
a) Promotion of food supply and proper nutrition
b) An adequate supply of safe water and basic sanitation;
c) Maternal and child health-care
d) Immunisation against major infectious diseases
e) Preventing and control of locally endemic diseases
f) Provision of essential drugs.
This will be achieved through a health system consisting of
three levels (state, provincial and localities), including the referral
system, secondary and tertiary levels. Pharmacy management
should be coordinated and integrated with other various aspects of
health. The following are recommended:
a. The community must be the focus of benefits accruing
from restructures, the legislature should protect community
interest on the basis of equity and distribution, handover the assets
to the community should be examined; and communities shall
encourage the transfer the management of health schemes to a
professional entity.
b. The private sector should be used to mobilise and
strengthen the technical and financial resources from within and
outside the country to implement the services, with particular
emphasis on utilisation of local resources.
c. The government should provide the necessary financial
resources to guide the process of community management of
pharmacy supplies. The government should be a facilitator through
setting up standards, specifications and rules to help harmonise
the private sector and establish a legal independent body by an act
of parliament to monitor and control the providers. Government
should assist the poor communities who cannot afford service cost
and alleviate social-economic negative aspects of Privatization.
d. The sector actors should create awareness to the
community of the roles of the private sector and government in the
provision of health and pharmacy services.
e. Support agencies should assist with financial and
technical support, training facilities, coordination, development
and dissemination of health projects, as well as evaluation of
projects.
Aims and Objectives
The main purpose of this study is to analyse and determine
the opinion of a group of pharmacists who are the owners or
shareholders in the Sudanese medicine importing companies and
their perception concerning the effects of the government’s new
Pharmacy, Poisons, Cosmetics and Medical Devices Act has had
on the quality of medicines in Sudan. To achieve this purpose the
following questions would be answered:
A. Do the Sudan pharmacy legislations prohibit marketing of
low-quality medicines?
B. What is the impact of the transfer of veterinary medicines
registration system to the Ministry of Animal Resources
after the approval of the Pharmacy and Poisons Act 2001?
C. Does pre-marketing analysis of medicines help to detect
the counterfeit medicines?
D. Does importation of non-registered medicines by the
government and non- governmental organizations exacerbate
the problem of low-quality medicine if any?
In Sudan, the researchers did not identify any rigorous
evaluations or quantitative studies about the impact of drug
regulations on the quality of medicines and how to protect public
health against counterfeit or low-quality medicines, although it is
practically possible. However, the regulations must be continually
evaluated to ensure the public health is protected against fake
medicines by ensuring the exclusive marketing of high-quality
medicines rather than commercial interests, and the drug
companies are held accountable for their conducts [17].
Medicines Legislation Framework in Sudan
The availability of medicines in Sudan is controlled on the
basis of safety, quality and efficacy. Thus, the government effects
control in accordance with the Pharmacy, Poisons, Cosmetics and
Medical Devices Act 2001 and its instruments. The Federal or State
Departments of Pharmacy (DOP) and directives issued orders.
The primary objective of both Federal and States’ Departments of
Pharmacy is to safeguard public health by ensuring all medicines
and pharmaceuticals on the Sudan market meet appropriate
standards of safety, quality and efficacy. The safeguarding of
public health is achieved largely through the system of medicines’
registration and licensing of pharmacy premises. The first
Pharmacy and Poisons Act was enacted in 1939. This Act had been
amended three times since then. In 2001 amendments, cosmetics
and medical devices were also brought under its purview. Thus,
the name was changed to Pharmacy, Poisons, Cosmetics and
Medical Devices Act (hereafter the Act). The Act regulates the
compounding, sale, distribution, supply, dispensing of medicines
and provides different levels of control for different categories,
e.g., medicines, poisons, cosmetics, chemicals for medical use and
medical devices. The Act makes provision for the publication of
regulations and guidelines by the Federal Pharmacy and Poisons
Board (FPPB), the pharmaceutical regulatory authority and its
executive arm - the Federal General Directorate of Pharmacy
(FGDOP). The FGDOP regulates mainly four aspects of medicines
use: safety, quality, efficacy and price. Traditionally, governments
in many countries, particularly developed nations have attempted
to ensure the efficiency, safety, rational prescribing, and dispensing
of drugs through pre-marketing registration, licensing and other
regulatory requirements [18]. When applying to register the
medicine manufacturers and importers are required to furnish the
FGDOP with a dossier of information including among others, the
indication of the medicine, its efficacy, side effects, contraindication,
warnings on usage by high risk groups, price, storage and disposal
[18]. The role of the FGDOP includes among others:
a) Regulation and control of the importation, exportation,
manufacture, advertisement, distribution, sale and the use of
medicines, cosmetics, medical devices and chemicals;
b) Approval and registration of new medicines - the Act
requires FGDOP should register every medicine before be sold or
marketed. Companies are required to submit applications for the
registration of medicines for the evaluation and approval;
c) Undertake appropriate investigations into the production
premises and raw materials for drugs and establish relevant quality
assurance systems including certification of the production sites
and regulated products;
d) Undertake inspection of drugs’ whole and retail sellers
owned by both public or private sectors;
e) Compile standard specifications and regulations and
guidelines for the production, importation, exportation, sale and
distribution of drugs, cosmetics, etc.
f) Control of quality of medicines: This will be done by
regular inspection and post-marketing surveillance;
g) Licensing of pharmacy premises (i.e., pharmaceutical
plants, wholesalers and retail pharmacies);
h) Maintain national drug analysis laboratories for the preand
post- marketing analysis of medicines;
i) Coordination with states departments of pharmacy to
ensure the enforcement of the Act and its rules and directives.
Health and Pharmacy Systems:
The health system in Sudan is characterised by heavy reliance
on charging users at the point of access (private expenditure on
health is 79.1 percent), with less use of prepayment system such as
health insurance. The way the health system is funded, organised,
managed and regulated affects health workers’ supply, retention,
and the performance. Primary Health Care was adopted as a main
strategy for health-care provision in Sudan and new strategies were
introduced during the last decade, including:
i. Health area system.
ii. Polio eradication in 1988.
iii. Integrated management of children illness (IMCI)
initiative.
iv. Rollback malaria strategy
v. Basic developmental need approach in 1997.
vi. Safe motherhood, making pregnancy safer initiative,
eradication of harmful traditional practices and emergency
obstetrics’ care programmes.
The strategy of price liberalization and privatization had been
implemented in Sudan over the last decades and has had a positive
result on the government deficit. The investment law [19] approved
recently has good statements and rules on the above strategy in
particular to health and pharmacy areas. The privatization and
price liberalization in healthy fields has to re-structure (but not
fully). Availability and adequate pharmacy supply to the major
sectors. The result is that the present situation of pharmacy
services is far better than ten years ago. The government of Sudan
has a great experience in privatization of the public institutions, i.e.,
the Sudanese free zones and markets, Sudan telecommunications
(Sudatel) and Sudan airlines. These experiences provide good
lessons about the efficiency and effectiveness of the privatization
policy. Through privatization, the government is not evading its
responsibility of providing health-care to the inhabitants, but
merely shifting its role from being a provider to a regulator and
standard setter. Drug financing was privatized early in 1992.
Currently, the Federal Ministry of Health (FMOH) has privatized
certain non-medical services in hospitals such as catering services,
security and cleanings.
The overall goal of the CMS ownership privatization is to
improve access to essential medicines and other medical supplies
in order to improve health status of the inhabitants particularly
in far states (e.g., Western and Southern States). Establishment
of alternative ownership for the CMS can be achieved by selling
the majority of shares to the private sector. This will achieve the
following objectives:
a. High access to essential medicines of good quality and
affordable prices to the states’ population and governments.
b. Efficiency and effectiveness in drug distribution system to
avoid the serious pitfalls and incidences that was reported during
the last ten years in the CMS.
c. Equity by reaching all remote areas currently deprived
from the formal drug distribution channels.
d. Improvement of the quality and quantity of delivery of
medicines to the public health facilities.
The above objectives are expected to:
a) Increase geographical and economic access to essential
medicines in all states (i.e., in both rural and urban areas) to reach at
least 80% of the population (currently less than 50% of population
have access to essential medicines).
b) The tax collection from the new business becomes more
efficient and will increase after privatization. The tax revenues
could be used to finance other health-care activities.
c) If the government reserves some shares (not more than
50%) in the new business, then its shares’ profit could be used
to finance free medicines project in hospitals outpatients’ clinic,
and other exempted medicines, e.g., renal dialysis and hemophilic
patients’ treatment.
Privatization of Public Pharmaceutical Supplies:
The term Privatization has generally been defined as any
process that aims to shift functions and responsibilities (totally
or partially) from the government to the private. More broadly
meaning, it refers to the restriction of government’s role and putting
forward some methods or policies in order to strengthen the free
market economy [20]. Privatization can be an ideology (for those
who oppose government and seek to reduce its size, role, and costs,
or for those who wish to encourage diversity, decentralisation,
and choice) or a tool of government (for those who see the private
sector as more efficient, flexible, and innovative than the public
sector) [20]. In [20]contends that “the invisible hand of the market
is more efficient and responsive to the consumer needs and the
public administrative budgets consume large portion of tax monies
that could otherwise be used for service delivery”. The emphasis
is on improving the efficiency of all public enterprises, whether
retained or divested.
Privatization May Take Many Forms Including:
Elimination of a public function and its assignment to the private
sector for financial support as well as delivery (police, and fire
departments, schools, etc.). Opponents characterize this as “loadshedding”.
Deregulation: The elimination of government responsibility
for setting standards and rules concerning goods or services.
Assets sales: The selling of a public asset (city buildings, and
sports stadiums) to private firms.
Vouchers: Are the government provided or financed cards or
slips of paper that permit private individuals to purchase goods or
services from a private provider (food stamps) or circumscribed
list of providers.
Franchising: The establishment of models by the public
sector that is funded by government agencies but implemented by
approved private providers.
Contracting: The government financing of services, choice of
service provider, and specification of various aspects of the services
laid out in contracts with the private-sector Organization that
produces or delivers the services.
User fees: Public facilities such as hospitals that maximise
their income or finance some goods from private sources, either
through drug sales or other services. This kind of Privatization has
been applied in Sudan since the early 1990s, as the health financing
mechanism (especially for medicines).
In Sudan, the government has decided to distance itself from
direct involvement in business, and thus divest most of its interests
whether in loss- or profit-making public enterprises. The public
reform programme was set firmly in the context of the broader
reforms [20], which were introduced in 1992. It had become clear
the previous policies had delivered led to poor results. This reform
based on the transfer of activities vested with the government
institutions to the private sector. It signaled the government
intention to reduce its presence in the economy, to reduce the level
and scope of public spending and to allow market forces to govern
economic activities. Privatization also forms part of the government
strategy of strengthening the role of the private in the development
to achieve the vision of the 25 years strategy in which the private
sector will be the engine for economic growth. The privatization
started in 1992 by liberalization of local currency, foreign exchange
transactions, internal and external trade, prices and health services
(e.g., user fee as a mechanism of drug financing and other services).
This reform had led to greater reliance on individual initiative
and corporate accountability rather than on government as a
decision-maker in business matters. The Privatization policy goal
is to improve the performance of the public sector companies, so
that they can contribute to the growth and the development of the
economy by broadening ownership, participation in management,
and stimulating domestic and foreign private investment. The
following are the primary objectives, which have been defined in
the government’s policy statement on public sector reform [20]:
a. Improve the operational efficiency of enterprises that are
currently in the public sector by exposing business and services
to the greatest competition for the benefit of the consumer and
the national economy.
b. Reduce the burden of public enterprises on the
government’s budget by spreading the shares’ ownership as
widely as possible among the population.
c. Expand the role of the private sector in the economy
(permitting the government to concentrate on the public
resources) on its role as provider of basic public services,
including health, education, social infrastructure, and to
compact the side effects of the Privatization.
d. Encourage wider participation of the people in the
ownership and management of business.
In pursuing the primary objectives, the privatization policy aims
to transform the performance of most significant enterprises in the
public sector and ensure liquidation of all viable and non-viable
public enterprises as soon as possible through commercialization,
restructuring and divesture. Public sector reform efforts are thus
aimed at reducing government dominance and promoting a larger
role for the private sector, while improving government’s use of
resources. Movement towards those goals in some countries is
supported by components of a structural adjustment loan, which
helped initiate the programme and establish the legislative and
institutional base. Opponents argue that the original objectives of
state ownership were to ensure the corporate sector of the economy
was in national hands rather than being controlled by either foreign
investors or the minorities that enjoyed business dominance upon
independence. A further objective was to use investment in state
firms to accelerate development in a situation, in which private
sector was reluctant to take risks.
Medicines Legislation Framework in Sudan:
The availability of medicines in Sudan is controlled on the
basis of safety, quality and efficacy. Thus, the government effects
control in accordance with the Pharmacy, Poisons, Cosmetics and
Medical Devices Act 2001 and its instruments. The Federal or
State Departments of Pharmacy (DOP) and directives issue orders.
The primary objective of both Federal and States’ Departments of
Pharmacy is to safeguard public health by ensuring all medicines and
pharmaceuticals on the Sudan market meet appropriate standards
of safety, quality and efficacy. The safeguarding of public health is
achieved largely through the system of medicines’ registration and
licensing of pharmacy premises. The first Pharmacy and Poisons
Act was enacted in 1939 and has been amended three times since.
In the 2001 amendments, cosmetics and medical devices were
also brought under its purview. Thus, the name was changed to
Pharmacy, Poisons, Cosmetics and Medical Devices Act (hereafter
the Act). The Act regulates the compounding, sale, distribution,
supply, dispensing of medicines and provides different levels of
control for different categories, e.g., medicines, poisons, cosmetics,
chemicals for medical use and medical devices. The Act makes
provision for the publication of regulations and guidelines by the
Federal Pharmacy and Poisons Board (FPPB), the pharmaceutical
regulatory authority and its executive arm - the Federal General
Directorate of Pharmacy (FGDOP). The FGDOP regulates mainly
four aspects of medicines use: safety, quality, efficacy and price.
Traditionally, governments in many countries, particularly
developed nations have attempted to ensure the efficiency, safety,
rational prescribing, and dispensing of drugs through pre-marketing
registration, licensing and other regulatory requirements. When
applying to register the medicine manufacturers and importers are required to furnish the FGDOP with a dossier of information
including: the indication of the medicine, its efficacy, side effects,
contraindication, warnings on usage by high risk groups, price,
storage and disposal.
Sudan Medicines’ Quality Measures
The following summarises the quality measures of all medicines.
Registration of Medicines
The FGDOP is responsible for the appraisal, and registration
of all medicines and other pharmaceuticals for both human and
veterinary use on the Sudan market. It is also responsible for
the verification of the competence of manufacturing companies,
the manufacturing plants, the ability to produce substances or
products of high quality before registering these companies
and allowing them to apply for registration of their products in
Sudan. When necessary, visits conducted to those companies
and their manufacturing units, to verify their compliance with
good manufacturing practice recommended by the WHO. The
applicant for registration of pharmaceutical product must submit
all prescribed data and the certificates required under the WHO
certification scheme for a pharmaceutical product moving into
international commerce, and any other information that is
necessary for assuring the quality, efficiency and stability of the
product through its shelf life [20].
Licensing of Pharmacy Premises
The licensing is a registration exercise to provide the DOP at
state level (Federal level in case of local manufacturing plants) with
the information necessary for the full implementation of the Act.
Licenses are granted for a period of one year and may be renewed
at the end of December every year (applications to the relevant DOP
before expiry of the current license). To improve the effectiveness
of the public pharmacy, resources should be switched towards
areas of need, reducing inequalities and promoting better health
conditions. Medicines are financed either through cost sharing
or full private. The role of the private services is significant. The
present policy of the national health–care system in Sudan is
based on ensuring the welfare of the Sudanese inhabitants through
increasing national production and upgrading the productivity of
individuals. The strategy of price liberalisation and Privatization
had been implemented in Sudan over the last decade and has had a
positive result on government deficit.
There are three major licenses as follows:
License A (Wholesaler License): The pharmaceutical
importing companies have subjected to two broad categories of
regulation. Those are the registration and administrative process,
and the regulation of quality manufacturing standards, efficacy
and information disclosure. License A authorises the holder to
sell a registered medicine to a person who buys the medicine for
the purpose of sale or supply to someone else under the direct
supervision of a registered pharmacist or licensed medical doctor.
Licensing of the wholesalers involves identification of the wholesaler
and suitability of the premise. There are 175 wholesalers in Sudan.
The majority (162 wholesalers) are local agents for the goods
manufactured from abroad. The rest are 13 “local manufacturer”
wholesalers at Khartoum State (KS) and distribute the medicines
to the whole country. Wholesalers are inspected by the state DOP
before license is granted and thereafter at least once per year.
License B (Retail Pharmacy License): Authorises the
holder to sell a registered medicine to a patient on prescription or
over-the counter basis under direct supervision of the registered
pharmacist. The pharmacies are inspected before a license is issued
and thereafter at least twice per year.
License D (Manufacturer’s License): Manufacturing
includes many processes carried out in the course of making a
medicinal product. A manufacturer’s license covers all aspectsbulk
drug, product manufacture, filling, labelling and packagingunder
supervision of a registered pharmacist. There are 13
generic manufacturing sites at Khartoum State (KS). The Federal
DOP inspects each one. Good manufacturing practice (GMP) is
the basis of the inspection. Effective control of quality requires a
manufacturer possess, and the appropriate facilities with respect
to premises, equipment, staff, expertise and effective well-equipped
quality control laboratory. Normally, before a license is granted, an
inspection of premises is made, and Federal DOP takes this into
account. The local manufacturers produce 65 pharmaceutical
dosage forms of essential drugs and cover 60% of the Central
Medical Supplies Public Organization (CMSPO) purchases.
In Sudan there are two types of retail pharmacy:
Commercial Private Pharmacies
These are private establishments retailing registered drugs and
medical supplies at a mark-up of 18%. The source of the drugs and
pharmaceuticals is private wholesalers. In 2002, though unlawful,
the CMSPO started to sell its non-registered medicines to the private
pharmacies. By the end of 2004, there were 779 private pharmacies
in Sudan.
People’s Pharmacies
These are quasi-public establishments retailing drugs and
medical supplies below the market prices to improve access and
availability of pharmaceuticals. They were founded in the early
1980s as a pilot study for a drug cost recovery system. Those differ
from the private commercial pharmacies. Firstly, in having access to
the CMSPO drugs, i.e., generic and large pack products, in addition
the brand products from the private wholesalers. Secondly, the
peoples’ pharmacies are only owned by public organizations
(e.g., hospitals, peoples’ committees, trade unions and Non Governmental Organizations (NGOs)). Mark-up on cost for drugs
from the CMSPO (35%), and from private drug wholesalers (profit
margin is 10%). However, they have become commercialized now
and operate in a similar way to private pharmacies. The total
number of such pharmacies was approximately 200 in Sudan.
Public Sector Medicines Supply System: In Sub-Saharan
Africa countries discussions about medicine distribution system
reform have concentrated on ways to improve sustainability
and quality of access to essential medicines. These discussions
also include debate on the impact of Privatization of public drug
supply Organizations on effectiveness, efficiency, quality and
cost of medicines in the public health facilities, as well as on the
respective role of the public and private sectors. Until the mid-
1980s, some governments in Africa (i.e., Mali and Guinea) assumed
responsibility for providing drugs to their citizens. The private
distribution of all drugs including aspirin was illegal. In many
countries, including Sudan there were two parallel government
distribution systems. The public health network of hospitals and
health centers gratuitously distributed drugs. In the public sector
pharmacies, the drugs were sold to the public at subsidized
prices. During the 1990s, Sudan initiated a number of initiatives
to establish drug-financing mechanisms as part of the health
reform process and decentralised decision-making at a state level.
In 1992 when a law was passed, medicines were no longer free of
charge (i.e., privatised) in the public health system. The aim of the
government is to increase equitable access to essential medicines,
especially at the states’ level. As a result, the Central Medical Stores,
which was responsible for medicines supply system of the public
health facilities, became an autonomous drug supply agency, and
was renamed as the Central Medical Supplies Public Corporation
(CMS) and operated on cash-and-carry basis. It was capitalised and
an executive board was installed. Since states and federal hospitals
have to buy their own medicines, and other medical supplies.
They organised their own transport means and distribution to
their primary health-care facilities and hospitals. In addition, all
hospitals became financially autonomous entities and have had to
organise their own medicines procurement system. The public drug
supply system has not been working well throughout Sub-Saharan
Africa and this includes Sudan. There are serious shortages or no
medicines at all, particularly in rural areas. A study in Cameroon
found the rural health centres received only 65% of the stock
designated for them, and 30% of the medicines that arrived at
the centres did not reach the clients. The loss rate after arrival in
hospitals was estimated at 40%. In Sudan, Graff and Evarard (2003)
who visited the country on a WHO mission reported, “Although the
cash-and-carry system took off well, but lack of sufficient foreign
exchange hampered the CMS procurement activities and resulted
in low stock levels of all medicines and even stock out of life-saving
products. Hospitals had to purchase the medicines from elsewhere
and often had to buy from private sector. Overall hospitals’
budgets were tied to allocate drug budget and sales income was
not sufficient to cover the purchase of needed medicines supplies.
This resulted the medicines were not available most of the times.
The in- or outpatients with their prescriptions were directed to
the private pharmacies. In 2003, Khartoum Teaching Hospital-the
biggest hospital in Sudan (not further than 5 km away from the
CMS) had a medicine stock of only LS 83,000 (US$ 31). This would
not fill one prescription for an anaemic patient as a result of renal
failure. This is a common practice that patients or their relatives
are given prescriptions to buy any pharmaceutical supplies that
are needed including drugs and other disposables from private
sector pharmacies. Many ministries of health, services’ providers
and researchers have identified many characteristics that lead to
poor performance in Africa public drug supply systems. These
characteristics include:
Absence of Competition: Competition is the best way to ensure
the goods and services desired by the consumer are provided at
the lowest economic cost. Given the customers (i.e., public health
facilities) freedom of choice enables market forces to provide
sustained pressures on companies to increase efficiency. Privatised
companies generally operate in a competitive market environment.
Insufficient Funding: For example, in Sudan with exception of
Khartoum, Gezira and Gedaref states, all other states do not have
enough funds to establish an efficient drug supply system. In spite
of being profit-making organization, the CMS failed to avail such
funds during the past 14 years.
Inefficient Use of Available Resources: Since CMS was
established in early 1990s working as a profit-making organization.
Due to the absence of privatization the CMS engaged in an instalment
of repackaging joint venture pharmaceutical factory in 1999 and
recently announced its commitment to build a pharmaceutical
city with not less than US$ 20 million, despite the lack of lifesaving
medicines in the public health facilities. Such amount could
be sufficient to establish a reliable supply system for all states of
Sudan. The lack of prioritization is a typical symptom and sign of
most public organizations.
Poor Management: There are a number of constraints inherent
in operating government drug supply service. These constraints
comprise:
a) Civil servants are hired, rather than persons with business
experience and skills. Managers confront different challenges
in public setting. They are not easily hired or fired. The lack of
accountability results from the lack of shareholders, who would
be free to remove incompetent administrators.
b) Even if the services can recruit outside of civil service,
the wages are often too low to attract experienced managers.
In addition, the managers do not share in dividends or other monetary activities as do private managers and incentives for
doing well are often attenuated in a bureaucracy.
c) There are cultural and structural conditions that promote
corruptions including enormous pressure of wages earners to
support an extended family and a strong incentive to more than
their fixed government wage, traditional gift giving practice and
a proprietary view of public offices.
Privatization of the CMS’s Ownership: The public
sector drug supply institutions have not succeeded (CMS is not
exceptional) so far in organising a reliable and regular essential
drug supply for the public health facilities (Huss, 1996). One of
the most criticisms of the public drug supply system generally in
Africa and particularly in Sudan is how badly they are internally
managed. There are those who agree the greater amount of real
pharmaceutical resources could be made available to the public
health- care system and the access to essential medicines could
be significantly increased, if managerial efficiency of the system
improved (Akin, 1987). Given the limitation of the public sector
- due to constraints inherent in operating a government drug
supply Organization even after autonomous experience - and the
stabilised role of the private sector Organizations such as private
pharmaceutical sectors Organizations (rapid increase in importing
companies, manufacturers and pharmacies). Telecommunications,
e.g., Sudatel is one of the obvious solutions of choice for the
government pharmaceutical policy would be to privatise the
ownership of the CMS to the extent possible.
Advantages of Private Agencies: There are many
arguments in favour of Privatization of public institutions.
Advocates of this method claim privatization have the following
advantages:
a. Privatization is efficient and effective because it fosters
and initiates competition. The competition among firms drives the
cost down. Empirical studies clearly prove the cost of the services
provided by the government is much higher than when the services
are provided by private contractors. For example, CMS’s declared
mark-up on cost (35%) amounted to 2.3 times the private markup
(15%). In addition, private sector pays taxes, customs and other
governmental fees (CMS exempted).
b. Privatization also provides better management than the
public management. Because decision making under Privatization
is directly related to the costs and benefits. In other words, the
Privatization fosters good management because the cost of the
service is usually obscured.
c. Privatization would help to limit the size of government at
least in terms of the number of employees. On the other hand, it is a
fact that overstaffing is common in publicly owned enterprises.
d. Privatization can help to reduce dependence on
a government monopoly, which causes inefficiencies and
ineffectiveness in services.
e. Private sector is more flexible in terms of responding
to the needs of citizens. Greater flexibility in the use of personnel
and equipment would be achieved for short-term projects, parttime
work, etc. Bureaucratic formalities are very common when
government deliver the service. Less tolerance and strict hierarchy
in bureaucracy are the reasons of the inflexibility in publicly
provided services.
Medicines Supply System: The Act, for the first time in
Sudan has given the responsibility of veterinary medicines to
separate committees. The Ministry of Animal Resources took the
law “in hand” and started the registration of veterinary medicines
and the licensing of the veterinary medicines premises. The conflict
in the shared authorities between the Ministry of Health and the
chairman of the FPPB lead to the freezing of the Board since October
2002. The FGDOP continues in the process of medicines registration,
inspection of the pharmaceutical premises and the licensing as
before establishment of the FPPB. The Act also obliges the states’
governments to take all steps necessary to ensure compliance with
marketing of registered medicines in licensed premises. But, the
weaknesses of the regulatory infrastructure and lack of political
commitment at state levels, the leakage of low quality, unregistered
medicines to those states are highly suspected. This left the door
widely opened for informal marketing of medicines particularly
in far states. The states regulatory authorities should take the
advantage of the legal authority granted by the Sudan constitution
and the Pharmacy, Poisons, Cosmetics and the Medical Devices Act
2001 to enforce the regulations and increase the frequency of the
inspection visits to drug companies and retail pharmacies.
Experience has shown the poor regulation of medicines can
lead to the prevalence of substandard, counterfeit, harmful and
ineffective medicines on the national markets and the international
commerce. The Sudanese pharmaceutical legal framework was
described as one of the strictest pharmaceutical system in the
region. One of the great loopholes in this system was found to be
the increased number of non-registered medicines-governmental
sources such as the Central Medical Supplies Public Organization
(CMSPO) and not-for-profit non-governmental Organizations
(NGOs). Respondents were hopeful the double standard of
rules enforcement would be lifted after the new national unity
government take over, arguing the current situation in which public
Organizations (such as the CMSPO) sell non-registered medicines
to the private pharmacies could enhance trading of counterfeit
medicines and create unfair competition environment.
One of the respondent reported, “It is disturbing, in spite of
the existence of appropriate legislation, illegal distribution of
medicines by the CMSPO. The CMSPO continues to flourish, giving
the impression the government is insensitive to harmful effect on
the people of medicines distribution unlawfully, and some are of
doubtful quality”. During the past three years the CMSPO started to
sell unregistered medicines to the private pharmacies. The CMSPO
practice (he added) will undermine the inspection and medicines
control activities and ultimately jeopardise the health of the people
taking medication.
Not surprisingly all respondents strongly agreed the increased
number of sources of non-registered medicines will lead to entrance
of low-quality medicines. This result is in line with the WHO
recommendation, which encourages the regulatory authorities and
state members` government to register all medicines before the
marketing. The medicines imported by public sector Organizations
are not excluded. The FGDOP should define the norms, standards
and specifications necessary for ensuring the safety, efficacy
and quality of medicinal products. The availability, accuracy and
clarity of drug information can affect the drug use decisions. The
FGDOP does not have a well-developed system for pre-approval of
medicines labels, promotional, and advertising materials. The terms
and conditions under, which licenses to import, manufacture and
distribute will be suspended, revoked or cancelled. This should be
stringently applied to public, private and not-for-profit NGOs drug
supplies Organizations. The predominant view shared between the
medicines’ importers is the current pharmacy legislation to some
extent satisfactory and managed to prohibit the marketing of low
quality medicines. The recent post-marketing study carried by the
National Drug Quality Control Laboratories, suggested the power
of the current regulation is overestimated. The finding of this
communication indicates the application procedures of the current
measures to ensure the quality of medicines should be revisited.
The technical complexity of regulations, political, commercial
and social implications, makes necessary a degree of mutual
trust between concerned stakeholders (i.e., suppliers, doctors,
pharmacists, consumer representatives and government agencies).
Rational for the Research
The drug distribution network in Sudan during the past
few years was in a state of confusion. It consists of open
market, drug vendors (known as home drug store), community
(private) pharmacies, peoples’ pharmacies, private and public
hospitals, doctors’ private clinics, NGOs clinics, private medicines
importers (wholesalers), public wholesalers (i.e., Central Medical
Supplies and Khartoum State Revolving Drug Fund) and local
pharmaceutical manufacturers. It is a common phenomenon in
far states (e.g., Western and Southern states) to see street sellers
or mobile sellers (hawkers) sell cigarettes, perfumes, orange and
astonishingly medicines that range from Paracetamol and Aspirin
tablets to antibiotics and anti-malarial drugs including injections.
The medicines are usually left under the sun, and such conditions
could facilitate the deterioration of the active ingredients. The
states’ departments of pharmacy statutorily licensed community
and Peoples’ pharmacies. A superintending pharmacist, who
is permanently registered with the Sudan Medical Council and
licensed, oversees the pharmacy any time it is opened for business
[20]. With such pharmacies there should not be any serious of
the sale of fake drugs. Unfortunately, however there are many
pharmacies working without qualified pharmacists. This study is
significant because the people right to health includes the right
access to a reliable standard of health care and assurance the
medicines received are not only genuine but also safe, effective,
of good quality and affordable [21]. The Sudan government has
designed various ways to protect the public against low quality
medicines. It is expected to equip the departments of pharmacy
especially in remote areas, poor states with material and trained
staff to effectively perform duties. A recent unpublished postmarketing
surveillance revealed that 35% of the CMSPO samples
and 16% of the private companies (registered products) samples
obtained from different pharmacy shops failed to pass the quality
test [21]. However, very few studies if any have been undertaken
to evaluate the impact of the regulations put in place by the
government long time ago. This study should reveal strength and
weaknesses of the legal pharmaceutical framework in Sudan from
drug importers perspective. The findings of this investigation
would be instructive to regulatory authorities in the developing
countries. It also highlights how systematically the drug companies
perceived the role of pharmacy regulations in assuring high quality
of medicines and what suggestions (if any) they had to make in
order to improve the regulatory framework.
Methodology
The study proposal was discussed to identify and improve the
quality of medicines in Sudan. The survey was deliberately drug
importers biased, as low-quality medicines from informal sources
will affect their business [22]. The authors then designed a selfadministered
questionnaire of 14 close-ended questions and one
open question. The questionnaire was designed to address main six
issues:
A. The quality of medicines.
B. The consequences of splitting of the regulatory authority
functions between the Federal Ministry of Health (FMOH) and
the Ministry of Animal Resources (MOAR).
C. Views on the role of the recently established Federal
Pharmacy and Poisons Board, and Pre- and Post- Marketing
Surveillance.
D. Decentralisation, and
E. Increased number of suppliers of non-registered
medicines.
The final version of the questionnaire had been tested (three
pharmacists working with drug companies in Sudan were asked to
fill the questionnaire and feed the authors back whether there was
unclear question or not). The questionnaire was tested to make sure
all relevant issues were covered, pre-coded and adjusted before its
distribution (Appendix 1). The questionnaire was distributed to
all forty participants at a seminar held in July 2004. Total numbers
of drug importers companies were 175 in 2004. The seminar was
organised by the FGDOP on the new proposal to limit (agree a ceiling
for each item) the number of commercial brand product registered
from each generic drug (the current situation is open). The owners
and shareholders of drug companies were the participants. This
was seen by the authors as a great opportunity to collect data of the
drug importers’ perspective on the quality of medicines. Hence, the
study participants were so busy and it was very difficult to devote a
time to be interviewed by the authors. In addition, the postal services
in Sudan are poor (too slow and unreliable). Before the beginning
of the seminar, the participants were requested by the secretariat
to complete the questionnaire and hand it back to the secretariat
before departure. The participants were informed it is anonymous
questionnaire. The reasons given to the participants for filling out
the questionnaire was to enable an academic research to assess the
impact of the new Act on the quality of medicines. Finally, at the end
of the seminar, the secretariat managed to get 30 questionnaires,
representing 75% out of 40 distributed. The information necessary
to conduct this evaluation was collected from 30 pharmacists
working with medicines’ importing companies. Data gathered by
the questionnaire were electronically analysed using Statistical
Package for Social Sciences (SPSS) version 12.0 for windows.
Result and Discussion
The drug distribution network in Sudan consists of open
market, drug vendors (known as home drug store), community
(private) pharmacies, people’s pharmacies, private and public
hospitals, doctors’ private clinics, NGOs clinics, private medicines
importers (wholesalers), public wholesalers (i.e., Central Medical
Supplies and Khartoum State Revolving Drug Fund) and local
pharmaceutical manufacturers. The states’ departments of
pharmacy statutorily licensed community and Peoples’ pharmacies.
A superintending pharmacist, who is permanently registered with
the Sudan Medical Council and licensed, oversees the pharmacy
any time it is opened for business [23]. With such pharmacies there
should not be any serious of the sale of fake drugs. Unfortunately
however, there are many pharmacies working without qualified
pharmacists [24]. During the last decade, the pharmacy workforces
have witnessed a significant increase in the number of pharmacies,
drug importing companies and pharmaceutical manufacturers as
shown in Table 1. In the public sector, adoption of cost sharing
policy as a mechanism of financing for essential medicines at full
price cost requires far more expertise than simply distributing free
medicines. This policy increases the demand for pharmacists in
hospitals. The new concept of pharmaceutical care and recognition
pharmacists as health care team members will boost the demand
for the skilled pharmacist registered (PHRs). The Federal Ministry
of Health (MOH) faces two major issues with the PHRs: first, the
current shortage of pharmacists in the public sector; secondly, the
future role of pharmacists within the health cares system. Around
3000 pharmacists are registered in Sudan. Only 300 (10%) works
with the public sector. 25, 25, 20 pharmacists were employed in
Khartoum, Khartoum North and Omdurman hospitals respectively.
Some states (e.g., Southern states has only 2 pharmacists) were
not included in Table 2. This anomaly seems to imply the number
of pharmacists in the public sector (has not only been insufficient
in absolute terms, but also has been inefficient in its distribution).
This number will be depleted and the situation may be getting
worse. One reason is migration to the private sector. The results are
described in Figure 1.
Table 1: Pharmacists labour market [24].
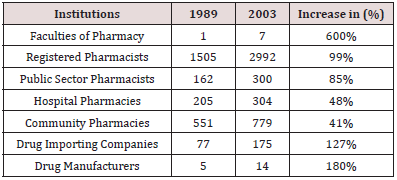
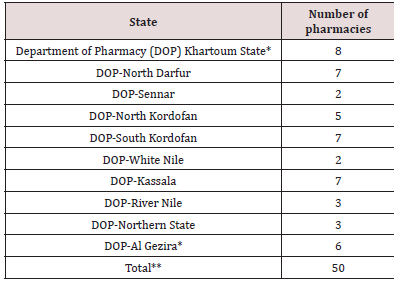
Table 2: Pharmacists’ distribution at state levels [27].
In the absence of past baselines data, decisive conclusions
should not be drawn from this article regarding the impact of the
pharmaceutical regulations on ensuring good quality medicines.
Nevertheless, the survey did serve to confirm the general impression
about medicines of good quality on the Sudanese market.
89% of respondents considered the medicines on the Sudanese
market are generally of good quality. Although 55% of the study
population either strongly agree (21%) or agree (34%) with the
statement the drug legislations in Sudan prohibit marketing of low
quality medicines. 35% believe the transfer of authority to recently
established the Federal Pharmacy and Poisons Board (FPPB) will
undermine on medicines quality assurance system. 38% of the
participants thought the replacement of the FGDOP by the FPPB
will improve the medicines quality control system. Only one-fourth
of respondents were not very confident in current systems and
safeguard to ensure the quality of medicines. 69% of respondents
were somewhat confident in the FGDOP regulates and monitors
quality of medicines. The majority 79% of respondents agree
with the statement ‘‘decentralisation of licensing and inspection
of pharmaceutical premises will improve the pharmaceutical
control’’. After the approval of the Pharmacy and Poisons Act 2001,
the Ministry of Animal Resources (dominated by veterinarians)
took the responsibility of registration of veterinary medicines
and the licensing of the whole and retail sellers of veterinary
medicines. As expected, 91% of respondents thought, the splitting
of drug registration between the MOH and the MOAR weakens
the medicines control, compared with only 9% who thought the
arrangement would improve the quality of medicines. One of the
respondents added: “The splitting of the drug authority between
MOH, which according to the Sudan constitution is fully responsible
for the public health and MOAR will create contradiction in lines
of commands and public health would be compromised”. 84% of
respondents agreed with the statement “This new arrangement
could cause conflict between two regulatory authorities” 93%
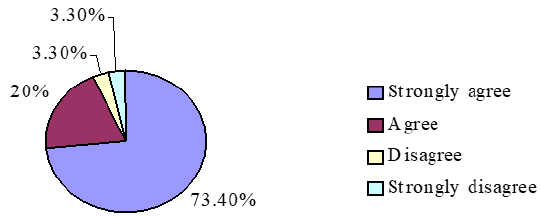
of participants either strongly agree (73%) or agree (20%) the
increased number of non-registered medicines distributors will
facilitate the marketing of low-quality medicines (Figure 1). When
asked about updated requirements of medicines registration, only
25% of respondents thought the updated requirements are not
sufficient to prevent marketing of low-quality medicines. Nearly
three-quarters (71%) agreed the pre-marketing surveillance is
not enough to ensure the quality of medicines. The law regulating
medicines was judged by the respondents as generally adequate
(68%).
Figure 1: The increased numbers of non-registered medicines importers will facilitate the marketing of low quality medicines.
Medicines Supply System
The Act, for the first time in Sudan has given the responsibility
of veterinary medicines to separate committees. The Ministry of
Animal Resources took the law “in hand” and started the registration
of veterinary medicines and the licensing of the veterinary
medicines premises. The conflict in the shared authorities between
the Ministry of Health and the chairman of the FPPB lead to the
freezing of the Board since October 2002. The FGDOP continues
in the process of medicines registration, inspection of the
pharmaceutical premises and the licensing as before establishment
of the FPPB. The Act also obliges the states’ governments to take
all steps necessary to ensure compliance with marketing of
registered medicines in licensed premises. But, the weaknesses of
the regulatory infrastructure and lack of political commitment at
state levels, the leakage of low quality, unregistered medicines to
those states are highly suspected. This left the door widely opened
for informal marketing of medicines particularly in far states. The
states regulatory authorities should take the advantage of the legal
authority granted by the Sudan constitution and the Pharmacy,
Poisons, Cosmetics and the Medical Devices Act 2001 to enforce the
regulations and increase the frequency of the inspection visits to
drug companies and retail pharmacies.
Experience has shown the poor regulation of medicines can
lead to the prevalence of substandard, counterfeit, harmful and
ineffective medicines on the national markets and the international
commerce. The Sudanese pharmaceutical legal framework was
described as one of the strictest pharmaceutical system in the
region. One of the great loopholes in this system was found to be
the increased number of non-registered medicines-governmental
sources such as the Central Medical Supplies Public Organization
(CMSPO) and not-for-profit non-governmental Organizations
(NGOs). Respondents were hopeful the double standard of
rules enforcement would be lifted after the new national unity
government take over, arguing the current situation in which public
Organizations (such as the CMSPO) sell non-registered medicines
to the private pharmacies could enhance trading of counterfeit
medicines and create unfair competition environment.
One of the respondent reported, “It is disturbing, in spite of
the existence of appropriate legislation, illegal distribution of
medicines by the CMSPO. The CMSPO continues to flourish, giving
the impression the government is insensitive to harmful effect on
the people of medicines distribution unlawfully, and some are of
doubtful quality”. During the past three years the CMSPO started
to sell unregistered medicines to the private pharmacies. The
CMSPO practice (he added) will undermine the inspection and
medicines control activities and ultimately jeopardise the health
of the people taking medication. Not surprisingly all respondents
strongly agreed the increased number of sources of non-registered
medicines will lead to entrance of low quality medicines. This result
is inline with the WHO recommendation, which encourages the
regulatory authorities and state members` government to register
all medicines before the marketing. The medicines imported by
public sector Organizations are not excluded [25]. The FGDOP
should define the norms, standards and specifications necessary
for ensuring the safety, efficacy and quality of medicinal products.
The availability, accuracy and clarity of drug information can affect
the drug use decisions. The FGDOP does not have a well-developed
system for pre-approval of medicines labels, promotional, and
advertising materials. The terms and conditions under, which
licenses to import, manufacture and distribute will be suspended,
revoked or cancelled. This should be stringently applied to public,
private and not-for-profit NGOs drug supplies Organizations. The
predominant view, shared between the medicines’ importers is
the current pharmacy legislation to some extent satisfactory and
managed to prohibit the marketing of low-quality medicines. The
recent post-marketing study carried by the National Drug Quality
Control Laboratories, suggested the power of the current regulation
is overestimated [26]. The finding of this approach indicates the
application procedures of the current measures to ensure the
quality of medicines should be revisited. The technical complexity
of regulations, political, commercial and social implications, makes
necessary a degree of mutual trust between concerned stakeholders
(i.e., suppliers, doctors, pharmacists, consumer representatives and
government agencies).
Worldwide there are different systems for providing pharmacy
services. Most countries have some element of state assistance,
either for all patients or selected groups such as children, and some
private provisions. Medicines are financed either through cost
sharing or full private. The role of the private services is therefore
much more significant. Nationally, there is a mismatch between
the numbers of pharmacists and where are they worked, and the
demand for pharmacy services. The position is exacerbated locally
where in some areas of poor; there is a real need for pharmacy
services, which is not being met and where pharmacists have little
spare capacity. Various changes within the health-care system
require serious attention be given to the pharmacy human resources
need. In order to stem the brain, drain of pharmacists, it is, however,
necessary to have accurate information regarding the reasons
that make the pharmacists emigrate to the private sector. Such
knowledge is an essential in making of informed decisions regarding
the retention of qualified, skilled pharmacists in the public sector
for long time. There are currently 3000 pharmacists registered with
the Sudan Medical Council of whom only 10% are working with the
government. The pharmacist: population ratio indicates there is
one pharmacist for every 11,433 inhabitants in Sudan, compared
to the World Health Organization (WHO) average for industrialized
countries of one pharmacist for 2,300 inhabitants. The situation is
particularly problematic in the Southern states where there is no
pharmacist at all [27]. The distribution of pharmacists indicates
the majority are concentrated in Khartoum state. When population
figures are taken into consideration all states except Khartoum
and Gezira states are under served compared to the WHO average.
This mal-distribution requires serious action as majority of the
population is served in the public sector. This study reveals the
low incentives, poor working conditions, job dissatisfaction and
lack of professional development programmes as main reasons for
the immigration to the private sector. The objective of this article
is to highlight and provide an overview of the reasons that lead
to the immigration of the public sector pharmacists to the private
sector in Sudan. The survey has been carried out in September
2004. Data gathered by the questionnaires were analysed using
Statistical Package for Social Sciences (SPSS) version 12.0 for
windows. The result has been evaluated and tabulated in this
article. The data presented in this paper can be considered as
nucleus information for executing research and development for
pharmacists and pharmacy. More measures must be introduced to
attract pharmacists into the public sector. The emerging crisis in
pharmacy human resources requires significant additional effort to
gather knowledge and dependable data that can inform reasonable,
effective, and coordinated responses from government, industry,
and professional associations.
Discussions
In Sudan, with more than ten million people don’t have
adequate access to health care; twenty million inhabitants are
without access to pharmacy, and a very low proportion of people
being treated in hospitals. The investment, which is needed to fund
the extension and improvement of these services, is substantial.
Most governments in developing countries are ready to admit that
they lack the financial resources for proper health and pharmacy
schemes. Moreover, historically, bilateral and multilateral funding
accounts for less than 10% of total investment needed. Thus the
need for private financing is imperative. Many healthy utilities
in developing countries need to work in earnest to improve the
efficiency of operations. These improvements will not only lead
to better services but also to enhanced net cash flows that can be
re-invested to improve the quality of service. Staff productivity
is another area where significant gains can be achieved. Failure
of subsidies to reach intended objectives is due, in part, to lack of transparency in their allocation. Subsidies are often
indiscriminately assigned to support investment programmes that
benefit more middle and high-income families, which are already
receiving acceptable service. Consumption subsidies often benefit
upper-income domestic consumers’ substantially more than
low-income ones. Many developing countries (Sudan is not an
exception) are encouraging the participation of the private sector
as a means to improve productivity in the provision of health and
pharmacies services. Private-sector involvement is also needed
to increase financial flows to expand the coverage and quality of
services. Many successful private-sector interventions have been
under taken. Private operators are not responsible for the financing
of works, nonetheless they can bring significant productivity gains,
which would allow the utility to allocate more resources to improve
and extend services. Redressing productivity, subsidy and crosssubsidy
issues before the private sector is invited to participate, has
proven to be less contentious.
Despite the constraints, over the last decade the rate of
implementation of rural and peri-urban pharmacy supplies and
healthy programmes has increased considerably, and many people
are now being served more adequately. The following are Sudan
experience in pharmacy supply and healthy projects:
At Community level:
i. Participatory approaches in planning, implementation
and monitoring.
ii. Establishment and training of reliable financial and
maintenance management.
iii. Sensitive timing of health and hygiene education.
At State and National level:
i. Integrated multi-sectoral approach development.
ii. Training approach and material development for state
and extension staff.
iii. Continuing support from integrated multi-sectoral
extension team.
iv. Establishment of technical support system.
v. Multi-sectoral advisory group including training and
research institutions.
vi. Development and dissemination of relevant information
for state and extension staff.
The respondents recommended continuing pharmacy
professionals’ development to assure the role of the pharmacists in
the health care, creation of new jobs, increase the salaries of public
sector pharmacists and activation of federal pharmacy and poisons
board.
Public Sector Pharmacists: The total number of
respondents from public sector was 26 pharmacists (53.8%) of
them were males. The majority (73%) of respondents graduated
within or after 1991. Most (69%) of them had studied in Sudan.
Surprisingly, (57%) of pharmacists (53.8% male) were employed
in the private at some time in the past before joining the public
sector. This is due to the fact some of the current pharmacy
managers in Federal and Khartoum State Departments of Pharmacy
had private sector experience. The top three reasons that demotivate
pharmacists who had experience with the private were
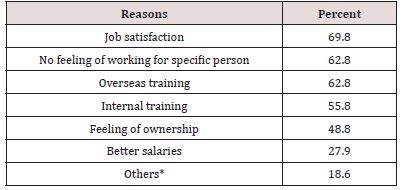
lack of ownership feeling (21.4%), sense of working for specific
person (21.4%) and job dissatisfaction (14.3%). Most (80.8%) of
respondents joined the public sector due to job satisfaction and
feeling of ownership (65.4%) as illustrated in Table 3. In answering
the question: ‘Do you have intention to leave the public sector at
some time in the future?’ (61.5%) of respondents answered ‘Yes’.
The vast majority (87.5%) of them owing their intention to leave
for better benefits in the private sector compared with the public
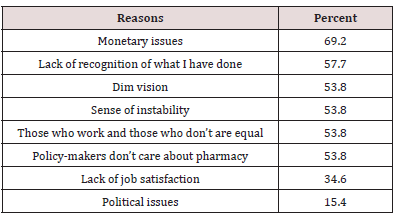
sector as given in Tables 4 & 5 shows (69.2%) of respondents
mentioned monetary issues as one of the reasons discourages them
from continuing with public sector.
Table 3: Reasons for choosing public sector (N = 26).
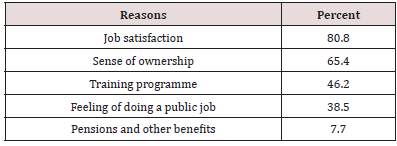
Table 4: ‘Why are you intending to leave the public sector?’ (N=
16).
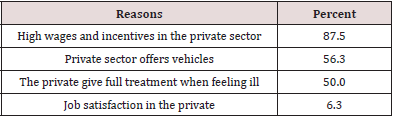
Table 5: Reasons discourage you to continue with public sector
(N = 26).
Private Sector Pharmacists: The number of respondents
from the private sector was 54 (80%) of them were male. (77.8%)
had studied in Sudan and the majority (74%) graduated during
or after 1991. 32 (59.3%) of the respondents worked with
community pharmacy whereas, 22 (40.7%) were drug companies
employees. Salaries in the private sector ranged from LS 500,000
to LS 2,500,000 Sudanese pound (LS) or more (1 US$ = LS 2500).
35 (65%) pharmacists had previous public sector experience.
In answering the question ‘Why did you leave the public sector?’
(51.4%) of respondents had left the public sector because policymakers
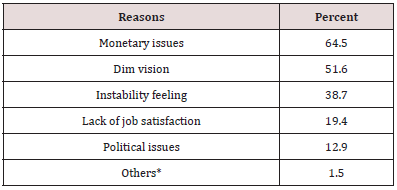
did not care of pharmacy (Table 5). The main reasons for
choosing the private sectors mentioned by respondents are the
salaries (61.8%); the job satisfaction (52.9%) and the vehicle
(26.5%) are shown in Table 6 and Figure 2. Substantial percentage
(78.4%) of the respondents answer “yes” to the question: thinking
about your own job; could you leave the private and join the public
sector at some time in the future? Table 7 shows the reasons,
which encourage pharmacists who were in the private sector (at
the time of the study) and are willing to join the public sector. The
most important reasons discourage the pharmacists who were in
the private sector during the study period from joining the public
sector are presented in Table 8.
Figure 2: Reasons for preferring the private sector.
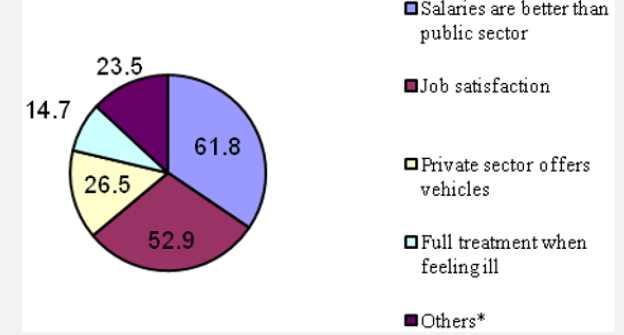
Table 6: ‘Why do you leave the public sector?’ (N = 35).
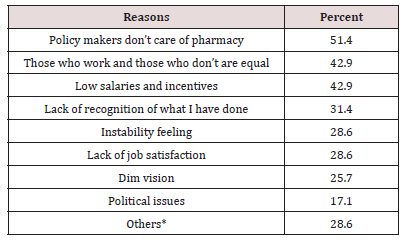
Table 7: Reasons for choosing the private sector (N = 34).

Table 8: ‘What encourages you to join the public sector?’ (N =
43).
Public Sector Pharmacy Workforces: The public health
sector reform seems to have undermined pharmacy human
resources in health sector as often as making a positive contribution.
Without motivated, competent, and well-funded pharmacy
workforces, there is a dangerous infusion of money for establishing
drugs revolving funds in different states. To address the national
problem of access to essential medicines will be either misused
or wasted, or both. Challenges with respect to pharmacy human
resources vary greatly between and within states, and associated with the political commitment of the states` government and
their ministers of health. The public sectors’ pharmacists in many
states are adversely affected by sever under investment from the
states and national funds, as well as external sources. For example,
pharmacy budget from World Health Organization (WHO) reduced
from US$ 200,000 in 2003 to only US$ 93,000 in 2004. Driven by
financial limitations, pharmacy workforces planning at federal and
states ministries of health has been unable to match pharmacists
requirements, the needs of community and the health system
as whole. It has been quite evident the civil service management
system is detrimental to the retention of skilled pharmacists (Table
9). Like other disciplines, the service affair authority determines
the number of pharmacists` jobs in the public sector. It also sets
salary scale and other incentives schemes in coordination with the
Federal Ministry of Finance and Economic Planning. Although health
professionals in hospitals tend to work in shifts and have to face
different working conditions, the incentive system was not flexible
enough to cope with differences between health professionals and
other civil servants. Notably, the gap in the pharmacy workforces
don’t generally relate to pharmacists, but to pharmacy assistants
who constitute the bulk of the workforces. The difficulties caused
by low pharmacy staff numbers are compounded by morale
problems, skill balances and geographical mal-distribution, most
of which are related to poor human resources management. How
can the ministry of health grapple successfully with the demands
of pharmaceutical care crises and the requirements of transformed
pharmacy profession, if it lacks the very foundation of pharmacy
care -motivated, trained and supported pharmacists.
Table 9: ‘‘Why didn’t some private-sector pharmacists like to
join the public sector?’ (N = 31).
Mal-Distribution: Around 3000 pharmacists are registered
in Sudan. Only 300 (10%) works with the public sector. 25, 25,
20 pharmacists were employed in Khartoum, Khartoum North
and Omdurman hospitals respectively. Some states (e.g., Southern
states has only 2 pharmacists) were not included in Table 10. This
anomaly seems to imply the number of pharmacists in the public
sector (hasn’t only been insufficient in absolute terms, but also has
been inefficient in its distribution). This number will be depleted
and the situation may be getting worse. One reason is migration to
the private sector.
Table 10: Pharmacists’ distribution at state levels
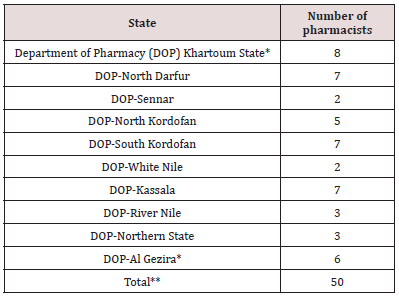
Working Conditions: Sudan like many developing countries,
the essential working conditions is not met. Social or personal
development opportunities are limited. Therefore, it is difficult for
health professionals in general and pharmacists in particular to
remain satisfied. The poor working conditions, remuneration and
other factors pushed pharmacists out of the public sector. To be
successful, user fee mechanisms must generally be accompanied
by perceived quality improvements in services. The World Bank
suggests the improvement in the quality of services would
compensate the negative impact of prices. This implies that
improved supply mechanisms for drugs are both prerequisites
and outputs of successful programmes. The properly designed cost
recovery programmes can encourage higher demand for modern
health care and, as a result, higher level of utilisation. If all are true,
it is unsurprising the utilisation of Sudan health services in the
public sector was low during the 1980s and personnel, especially
in peripheral health facilities, idle most of the time. In 1992, Sudan
had introduced cost recovery measures as a part of its programme
of economic reforms, following a course taken by many developing
countries. During the 1990`s, Sudan initiated number of initiatives
to establish medicine financing mechanisms as part of health
reform process and decentralised decision-making at state level.
In 1992, the government abolished the constitutional right of free
health care. There is interest by the states to introduce a medicine
financing mechanism based on the Revolving Drug Fund (RDF)
experience of Khartoum State (KS).
Nanomedicines
Nanomedicine is defined as the medical application of
nanotechnology. Nanomedicine can include a wide range of
applications, including biosensors, tissue engineering, diagnostic
devices, and many others. In the Center for Nanomedicine at
Johns Hopkins, we focus on harnessing nanotechnology to more
effectively diagnose, treat, and prevent various diseases. Our entire
bodies are exposed to the medicines that we take which can lead to
unpleasant side effects and minimize the amount of medicine that
reaches the places where it is needed. Medications can be more
efficiently delivered to the site of action using nanotechnology,
resulting in improved outcomes with less medication. For example,
treating cancer with current chemotherapy delivery techniques is
like spraying an entire rose garden with poison in order to kill a
single weed. It would be far more effective to spray a small amount
of poison, directly on the weed, and save the roses. In this analogy,
a cancer patient’s hair follicles, immune cells, and epithelia are the
roses being poisoned by the chemotherapy. Using nanotechnology,
we can direct the chemotherapy to the tumour and minimize
exposure to the rest of the body. In addition, our nanotechnologies
are more capable of bypassing internal barriers, further improving
upon conventional nanotechnologies. Not only is our approach more
effective at eradicating tumours under Research), but it also results
in much higher quality of life for the patient. Nanomedicine is the
medical application of nanotechnology. Nanomedicine ranges from
the medical applications of nanomaterials and biological devices
to nano-electric devices, to nano-electronic biosensors, and even
possible future applications of molecular nanotechnology such as
biological machines. Current problems for nanomedicine involve
understanding the issues related to toxicity and environmental
impact of nano-scale materials and (materials whose structure is
on the scale of nanometres, i.e. billionths of a metre). Functionalities
can be added to nanomaterials by interfacing them with biological
molecules or structures. The size of nanomaterials is similar to that of
most biological molecules and structures; therefore, nanomaterials
can be useful for both in vivo and in vitro biomedical research
and applications. Thus far, the integration of nanomaterials with
biology has led to the development of diagnostic devices, contrast
agents, analytical tools, physical therapy applications, and drug
delivery vehicles. Tracking movement can help determine how well
drugs are being distributed or how substances are metabolized. It
is difficult to track a small group of cells throughout the body, so
scientists used to dye the cells. These dyes needed to be excited by
light of a certain wavelength in order for them to light up. While
different colour dyes absorb different frequencies of light, there
was a need for as many light sources as cells. A way around this
problem is with luminescent tags.
Conclusion and Recommendation
The study reveals the need for further research to find out how
efficient the regulatory authorities at both federal and state levels
are. The research also needed to discover whether or not counterfeit
medicines are sold on the Sudanese market. From the data obtained
in this article some general inferences could be made:
a. The brad outlines remain intact, but preventing drug
smuggling across national boarders (Sudan shares frontiers
with 9 countries) is hard to police.
b. The enforcement of the Act and its regulation governing
the manufacture, importation, sale, distribution and exportation
of medicines are not adequate enough to control the illegal
importation and sale of medicines in Sudan.
c. The splitting of the drug regulatory authority between
two ministries and the marketing of unregistered medicines by
public drug suppliers (namely the CMSPO, and RDFs), and NGOs
undermine the quality of medicines and ultimately jeopardise
the health of the people taking medication.
In the light of the findings the following recommendations
could be useful at various levels:
a. There is an urgent need for government to implement the
provisions of existing Act.
b. The government should adequately equip and fund
the National drug Analysis laboratories to start active postmarketing
surveillance.
c. A more spirited effort need to be made by the FGDOP
and the States’ Departments of Pharmacy to ensure all the
medicines on the pharmacies’ shelves are registered and come
from legal sources.
d. The states’ departments of pharmacies are not in existence
should be re-established and invigorated. They should be
adequately funded to be able to acquire the necessary facilities
for their operations.
e. The CMSPO should stop importation, manufacture and
distribution of unregistered medicines. It should also cease
selling the tenders’ product to the private pharmacies. The
latter practice undermines the inspection outcomes, because
it makes inspectors task too difficult (i.e., can not identify the
source of medicine whether it is CMSPO or not).
The public sector is rigid, bureaucratic personnel-management
practices, low incentives, poor job satisfaction and unsupportive
work environment compared to the private sector. Such situation
demoralised pharmacists and encourages them to join the private
sector. Many (65%) of surveyed private-sector pharmacists claimed
they were public sector pharmacists migrated to the private
sector. Although information on migration is sparse, anecdotal
evidence persuasively underscores the problem. An internal flow of
pharmacists plagues all states, since pharmacists move from poorer
states to wealthier ones and from the public sector to the private.
Strategies to meet current and future challenges in pharmacy
human resources are urgently needed. Approaches that focus on
the training of individuals, which do not take into account the job
satisfaction (i.e. the nature of the work itself) and pharmacists’
mobility, can enjoy only limited success. Increased production alone cannot compensate for weak motivation, high attrition and
increasing mobility. To reverse decades of neglect, policy-makers in
both (state and federal level) should begin now, first by recognising
the problem and secondly by fixing it through the immediate
implementation of potentially effective strategies. Although, we
do not advocate the creation of new barriers to the movement of
pharmacists between private and public sectors, steps should be
taken to redress the unbalanced situation. Ten immediate steps are
recommended:
Large-scale advocacy is needed to achieve heightened political
awareness within states and at federal level. One potential outcome
of large-scale movement would be the beginnings of introduction
of pharmacy care concept, which reshapes the pharmacy services
around the patients in hospitals and community pharmacies. This
concept will benefit the health care system users and motivate
pharmacists to do a good job to their clients and employers. The
employers need to foster an Organizational culture that recognises
and values staff contribution. Central to the delivery of effective
recognition are employees’ immediate bosses, where a participative
and considerate management style is shown as a major predictive
factor of retention.
The Federal Ministry of Health (FMOH) needs to learn from
the past experience of Khartoum, Red Sea, Northern, and Algadarif
States and current Gezira State then, identify success stories.
Pharmacists and their Organizations, and Ministries of Health
have not remained passive in confronting the crisis in pharmacy
workforces. The goodwill and commitment of public sector
pharmacists to provide quality care despite low wages (30% of the
average private salary) and medicines supply shortages at times of
appalling conditions should not be overlooked.
Pharmacist Job Satisfaction: Job satisfaction is how people
feel about their jobs. Experiencing job dissatisfaction leads to
withdrawal cognition and employee turnover. Job dissatisfaction
can be caused in many ways, including high centralisation,
routinisation, low integration, low communication and policy
knowledge. Pharmacy education has a key role to prepare pharmacy
student for practice and must anticipate the changing professional
role. New strategies need to be developed with the participation
of pharmacy professionals associations, unions, universities and
ministries of health and higher education representatives to
meet both; the short-term and long-term needs of pharmacists
as pharmacy care providers. Technology will, no doubt give
opportunity to join postgraduate studies (e.g., P.G. diploma or M.Sc.
courses) from overseas via e-learning or continuing pharmacy
professional development programmes.
Salaries and Incentives Structure: This includes the process
of creating new jobs, addressing low wages, as well as developing
incentives structure that supports pharmacists over the course of
their working lives. In order to stem the flow of pharmacists to the
private sector and increase their performance, the Ministry of Health
needs to pay incentives to its pharmacy staff on a semi-private basis.
Introduction of the employment contract and the application of the
incentive budget line opposite performance proved to be effective in
Khartoum State experience. The obligations of each part (employer
and employee) should be written in non-ambiguous language and
transparent reward system should be in place. When transparency
of reward system is poor, its credibility will be questioned and
pharmacists might not respond to the explicit incentive system
at all. IDS, 2000 pointed the lack of training and potential career
development is a particularly important contributor to voluntary
resignations. Uncompetitive pay is often debated as a reason for
employee turnover. The perception of receiving a fair salary is
a determinant of retention. It seems to be important both at the
recruitment stage and subsequently as a determinant of retention
rates is the perception that employees are receiving a fair salary. It
is important to note this doesn’t necessarily equate to a large salary,
since people often compare themselves with peers in the same
occupations or with friends and family rather than with better
paid or higher skilled workers. Also, when promises are broken
and expectations are perceived (haven’t been met), employees take
actions to withdraw from the Organization, which may include
actually quitting jobs.
Pharmacy Staff Motivation: In addition to financial incentives,
Ministry of Health should continue to invest in improving the
working conditions to ensure the suitable qualified and skilled
pharmacists are retained for longer periods. Recruitment of
qualified pharmacists (which may include looking outside the
public services). A clear definition of job assignments (staff at
hospitals` level enter into written contracts to perform according
to MOH guidelines) and regular supervision will assist MOH to
achieve a good staff performance. MOH should provide transport to
pharmacists (senior and specialised pharmacists could be offered
private vehicles) from their residence to the place of work to
increase their motivation. Company-paid private medical insurance,
and a company car for senior staff, child day care facilities, pension
and retirement plans are the most desired and lead to employee
retention.
Redistribution of Pharmacy Workforces: To address the
problems of pharmacy profession in Sudan, an increase in access
to essential medicines is insufficient. Far more important is the
need to strengthen the pharmacy workforce in localities, states
and federal health institutions to address the challenges and to
use the resources and interventions for provision of effective
pharmaceutical services.
Small Staff and Efficient Teamwork: The pharmacy workforces
are divided into two levels (1) Department of pharmacies at
Ministry of Health, and (2) Hospitals. The Department of pharmacy
at state level should consist of 6 pharmacists at maximum and 25 at
federal department of pharmacy including drug analysis laboratory.
The hospitals` department of pharmacies classified as follows:
i. Group A includes big hospitals (e.g., Khartoum and
Omdurman hospitals). The numbers of pharmacists in Group A
hospitals are 15 pharmacists in addition to pharmacy assistants
and other supportive staff to cover all shifts. One manager, 3
pharmacist work in Drug Information Centre, three for internal
hospital pharmacy, two in outpatient pharmacy, three in people
pharmacy and one in clinical pharmacist;
ii. Group B includes medium hospitals and capital cities
hospitals (e.g., Ibrahim Malik, and Medani Hospitals). The Hospital
Pharmacy Department (HPD) this group managed by 4 to 6
pharmacists;
iii. Group C includes small and rural hospitals. Two
pharmacists could run the HPD in these hospitals. Paying attention
to create more flexible and efficient system for PHRs management
in the government institutions might help improve the condition
of shortages of pharmacists in the public sector. The advantages
of small staff can be easily managed, trained and financed, and
teamwork could be developed. This also improves the performance
and productivity of the public sector pharmacists thereby reduces
the number of PHRs needed to provide satisfactory pharmaceutical
services in the public sector institutions. The best indicators of staff
retention are the fostering of friendships at work, and managers
in health cares should take time to get knowing people and foster
opportunities for friendship and socialising.
National leadership at the highest level is essential and will only
come to heighten the awareness of the fundamental importance of
pharmacists in health care in general and in the pharmaceutical care
in particular, and the development of new methods and strategies.
Continuing Pharmacy Professional Development: The most
important element of National Drug Policy (NDP) and 25 years
pharmacy strategy has yet to be tackled. MOH should fully recognise
its 25 years pharmacy strategy goals could be achieved through
people’s (especially pharmacists) expertise. Appropriate training
and development is the key to reach those goals and make strategy
visions become reality. A wide variety of external (e.g., distance
or e-learning in the developed world) and internal training and
development programmes for pharmacists should be introduced.
A pharmacist’s career or pathway should be developed. A policy for
active selection of training fields should be formulated according to
the priorities of health care needs. The career development relies on
individual training and development to enable employees to move
into more challenging roles and can provide enhanced rewards for
those who are promoted.
Pharmacy Staff Discipline and Accountability System:
Disciplinary procedures, which provide a range of possible responses
(from warnings through dismissal, depending on the severity and
frequency of the offence should be clearly stated in the new work
contracts). Pharmacy managers and team leaders in different
settings (administration or care providing, at both state and federal
levels) should be trained to invoke disciplinary procedures and to
bring criminal charges when necessary. Improving effectiveness
of the public pharmacy is by switching resources towards areas of
need, reducing inequalities and promoting better health. Unless
there are clear incentives for pharmacists, they can move away
from public sector.
Findings innovative approaches to stop brain drain of the
pharmacists from the public sector and to increase their productivity
and performance might be more appropriate strategies to solve
the problem in Sudan. These strategies comprise, for instance,
monitory incentives, continuing professional development, working
condition and job satisfaction of civil service PHRs. The study may
help the Ministry of Health to better look at the real issues of PHRs
in the public sector and formulate more relevant and useful policies
and plans to retain qualified and skilled pharmacists in the public
sector on a solid evidence base. Monitoring and evaluation of
information provided to MOH. The data must be accurate and up to
date. The study revealed low salaries, job dissatisfaction in relation
to the pharmacy practice and bureaucracy, working conditions, lack
of recognition for contribution at work, and lack of professional
development training programmes are the main factors influencing
the brain drain of the PHRs. These factors affect PHRs immigration
and retention concurrently rather than in insolation. Given the time
constraints required to get the new contracting arrangements in
place, there is a risk that good practice developments in options for
change for change field sites may not be used effectively (continue
to evaluate and disseminate the lessons that emerge from these
sites).
Ethical Clearance and Data Protection Consent
Before starting the data collection, ethical clearance was
obtained from the Federal Ministry of Health (MOH)-Research
Ethics Committee. The first author signed the data protection
consent and the respondents were informed it was an anonymous
questionnaire and all the data collected are for the FGDOP
assessment purpose. Nevertheless, the participants were also
informed the data processing would not be used to support any
decision-making and would not cause any damage and distress
them or to their business.
Research Limitations
The selection of one group of stakeholders and ignorance of the
rest (such as the CMSPO, retail pharmacies, drug manufacturers,
NGOs, consumers Organizations, policy-makers, regulators, police,
customs, doctors, other health care professionals, and health
professional unions, etc.) were not included. This means great caution must be exercised in any extrapolation to a country level
statistical analysis, and percentage given must be regarded as
rough estimates.
Reliability and Validity of the Research Instrument
The sample chosen is indicative rather than fully representative
and has been sized to be feasible in the time and resources available
for the authors. However, the sample is thought to be sufficient to
allow valid statistical analysis. Establishing the reliability and
validity of measures are important for assessing their quality [7].
The mentioned time, and resources constraints did not allow the
authors to test the reliability and validity of the research instrument.
Read More About Lupine Publishers LOJ Pharmacology & Clinical Research (LOJPCR) Please Click on Below Link: https://lupine-publishers-pharmacology.blogspot.com/