Showing posts with label Pediatric Dental Care Journal. Show all posts

Friday, 29 January 2021

Lupine Publishers | The Effects of Breastfeeding on the Process of Tooth and Jaw’s Development

 Lupine Publishers | Journal of Otolaryngology

Abstract

From the nutritional point of view, it has been proven that breast milk has many benefits for the baby, and it is advisable for all mothers to give their baby milk, and if possible do not replace that with the bottle. In other words, we can say that the sucking mechanism used during bottle-feeding is markedly different from that used during breast-feeding. The Federation of Orthodontists of France announced in a report that breastfeeding not only prevents allergies and gastrointestinal infections and overweight, it also promotes the regular growth of the baby’s face. Some of the researches prove this hypothesis.

Keywords: Bottle Feeding; Breast Feeding; Sucking Mechanism; Growth of Baby Face; Allergies; Gastro Intestinal Infections; Overweight

Introduction

After birth, the baby learns how to suck on her mother’s breast. She instinctively brings forward her lower jaw and tongue; then starts sucking with full power so that all the muscles of her tongue, cheeks, lips, and jaw are involved. In all infants, since jaws are not fully developed at birth, sucking breast milk helps the jaw to grow as well as the teeth in the future [1-3]. Breast-feeding has been indicated as one of the main factors which are responsible for the correct growth and formation of dentofacial structures during the infancy [1-3]. Breastfeeding is a useful action for developing and growing teeth and jaws of infants [1-4]. The mechanism used in for the time of bottle-feeding is markedly different from that used during breast-feeding [5-7]. In the course of sucking mother’s milk, more muscles are activated to get milk than to drink milk from the bottles. During this action, the baby inserts more of the nipple into his mouth, consequently, moves the jaw up and down, and sucks the breast with all force to release the milk. To achieve this, the facial and oral muscles of the baby are involved in milking activities. This improves the shape of the jaws, and healthy teeth are expected to be in the correct eruption direction without any deviation and abnormalities [1-4].

The Main Cause of Abnormal Tooth Formation During Infancy

One of the factors leading to abnormal teeth and also leading children to orthodontic or speech therapies [8] is the abnormal orofacial muscular imbalance pattern of the tongue [9-11] known as tongue thrust. This problem is more common among children who are fed through the bottle and is often not seen among those who are breastfed. In other words, the breast-fed baby has more forceful gums and mandibles to extract the milk from the mother’s breast while a baby who is fed with a bottle, does not have to use extra jaws force because by a simple sucking a rapid flow of milk will be obtained. Of course, it should not be taken for granted that all children who use the milk bottle suffer from jaw problems, but it should be remembered that breastfeeding give better evolution to the jaws and teeth than the nourishment from the bottle.

Overview of Some Researches

The early transition from breastfeeding to bottle-feeding may contribute to inadequate mandibular development which can be a dominant and deleterious factor in the development of occolusofacial problems. In this part, we look at some research which may point out this strong hypothesis. Some studies have cited that breastfeeding is a protective factor against malocclusion: Labbok and Hendershot have suggested that increased bottlefeeding duration may contribute to the prevalence of malocclusions [12].

Viggiano et al. and Karjalainen et al. have indicated that breastfeeding can be a positive factor to prevent the development of posterior cross bite in the primary dentition [6,13]. Warren et al. reported that breastfeeding promotes normal palate development and weakens the formation of a deep and high-arched palate [14]. Several studies agree that bottle-feeding may be responsible for the development of sucking habits which may lead to some forms of malocclusion [6,14,15].

Conclusion

Breastfeeding acts on the process of sucking which are influencing the development of facial bones and muscles. Infants who are breastfed have greater facial muscle activities compare to those who are bottle-fed. In other words, breast feeders present an excellent orofacial muscle work out which helps to develop good their bony jaw structures. Moreover, breastfeeding prevents against orthodontic problems and malocclusions (for instance: overbite, posterior crossbite, tongue thrust, oral habits and etc.) that are cited in some researches.

Read More Lupine Publishers Pediatric Dentistry Journal Articles: 
https://lupine-publishers-pediatric-dentistry.blogspot.com/


Friday, 15 January 2021

Lupine Publishers | Varied clinical and Oral Presentation of Beckwith – Wiedemann Syndrome - Report of a Case from Saudi Arabia

 Lupine Publishers | Journal of Pediatric Dentistry


Abstract

Beckwith – Wiedemann syndrome is congenital, genetic and epigenetic pathologies with low prevalence and diverse clinical presentations. It is characterized by triad of omphalocele, macroglossia and gigantism. This syndrome has been widely studied with a current emphasis on improvement of prenatal diagnostic techniques and a multidisciplinary approach towards treatment. We report a case of BWS from Saudi Arabia, with unique presentations and misleading history which delayed diagnosis, due to cultural and religion constraints.

Keywords:Congenital; Epigenetic; Genetic; Prenatal

Introduction

Genetic and epigenetic changes or a human genomic imprinting disorder is characterized by phenotypic variability which might shows its occurrence either as sporadic or inherited. The pathology presents wide range of effect on psychological and social wellbeing of patients and families. One such congenital, multigenic, multisystem human genomic imprinting disorder with complex molecular etiology and variable complex phenotype is Beckwith – Wiedemann Syndrome (BWS). Beckwith-Wiedemann Syndrome is most common overgrowth syndrome described by Beckwith in 1963 and Wiedemann in 1964 with similar findings. It is rare congenital deformity with low prevalence but at same time have high prevalence within genetic abnormalities of overgrowth [1]. The presentation of triad features of omphalocele (exomphalos), macroglossia and gigantism was described earlier as EMG syndrome which now is referred as Beckwith – Widemann Syndrome. The incidence of BWS reported is approximately 1:13700 births and the major cause is thought till date is genetic and epigenetic defects within the chromosome 11p15.5 regions [2].

BWS presents wide array of clinical manifestations such as congenital abdominal wall defects as hernia (exomphalos), gigantism, macroglossia, nevus flammeus, ear pits/hearing loss, midface hypoplasia, cardiac anomalies, hemihypertrophy, genitourinary anomalies and musculoskeletal abnormalities. To standardize the diagnostic criteria various attempts have been made to classify the major and minor criteria. Elliot et al described the diagnosis of BWS with the presence of either three major features (abdominal wall defect, macroglossia, gigantism) or two major and three minor features (ear pits, nevus flammeus, hemi hyperplasia, nephromegaly, neonatal hypoglycemia) [3]. In spite of diverse clinical presentations of BWS, most of the cases do not show characteristic features at birth but develop later in life. Also, children with BWS have significantly increased risk of cancer during early childhood which need strict follow up and monitoring. Here, we present a case of BWS with unique dental and medical presentation and its differential diagnosis with literature review.

Case Report

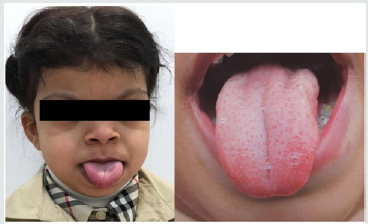
A 5-year-old female patient, accompanied by her mother, presented to the dental unit with complaint of decay tooth in upper front region of mouth. Extra oral examination revealed dysmorphic features, coarse facies and developmental problems (Figure 1). Intra oral examination of hard tissue showed high arched palate, decayed teeth in relation to 51, 52, 55, 61, 62, 74, 75, 84,85. Oral soft tissue examination revealed macroglossia, enlargement of fungiform papillae and mild loss of filiform papillae (Figure 2). Speech and feeding difficulty were noticed due to macroglossia. History revealed she is the youngest 7th child born out of consanguineous marriage in 30th week by cesarian section. She has a chronic history of constipation for 9 months of age. She passes hard stool once in every 8 to 10 days, by spending long time in washroom. It is associated with decrease in appetite and abdominal pain. She was given Movicol (half the adult dose) twice a day for constipation without any medical prescription. She was also tried with lactulose, glycerin suppository and mineral oil. Under medical supervision fleet enema and contrast enema were performed to relieve constipation and to rule out Hirschsprung disease.

Figure 1: Photograph showing dysmorphic features and hypertelorism.

Lupinepublishers-openaccess-pediatric-dentistry-journal

Figure 2: Macroglossia with enlarged fungiform papillae and loss of filiform papillae.

Lupinepublishers-openaccess-pediatric-dentistry-journal

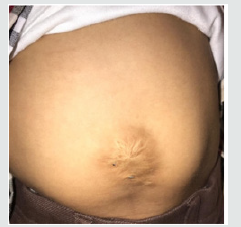
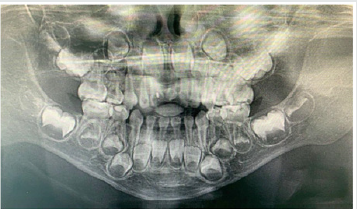
Other medical findings noticed omphalocele, ear pits, large child at 90th centiles, large rounded eyes with hypertelorism, abdominal soft lax, enlargement of kidney, distention of left renal pelvis with significantly distended urinary bladder, abnormal anatomy of the colon located in left abdomen and partial colonic non – rotation with no evidence of obstruction (Figure 3). Based on the clinical and past medical history a diagnosis of Beckwith – Wiedemann Syndrome (BWS) was made. Series of laboratory investigation were reviewed which presented negative urine examination, alpha – fetoprotein, karyotype, microarray and methylation analysis for BMS. Patient was advised for gene analysis and targeting testing for parents. The gene analysis of CDKN1C gene showed heterozygous alteration consistent with BWS but targeting gene tests were refused by parents. Panoramic radiograph was advised considering the patient chief complaint, which revealed multiple developing permanent tooth buds, protrusion of anterior teeth, open bite and increase in mandibular dimension (Figure 4). Under preventive measures the patient was treated for the decayed teeth and is under follow up from past 6 months.

Figure 3: Photograph showing abdominal wall defect with surgical scar.

Lupinepublishers-openaccess-pediatric-dentistry-journal

Figure 4: Panaromic radiograph showing multiple developing permanent tooth buds, open bite and increased mandibular dimension.

Lupinepublishers-openaccess-pediatric-dentistry-journal

Discussion

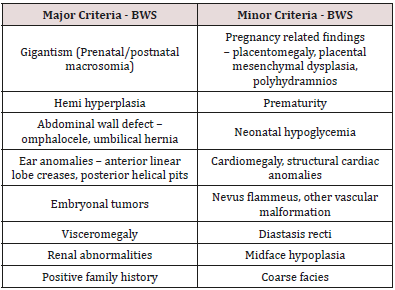
Diagnostic criteria for BWS is still a matter of research due to its varied clinical presentations and overlapping features with other various conditions. The presence of major and minor findings is generally helpful in establishing the clinical diagnosis (Table 1). The oral findings as mentioned in the literature and observed in our case has been tabulated in Table 2 [4,5]. The incidence of BWS is difficult to assess in Saudi Arabia, as most of the cases goes undiagnosed and unnoticed. Also attributed to its diverse clinical presentation and difficulty in diagnosing. In the present case, features of macroglossia, macrosomia, omphalocele, abdominal wall defect (treated immediately after birth and surgical scar observed clinically), Renal involvement, ear crease, high arched palate, open bite and increased mandibular dimension, leads to the diagnosis of BWS. Various molecular mechanisms and alterations have been involved in BWS such as abnormal methylation of H19DMR, loss of imprinting of IGF2, chromosomal rearrangements, loss of imprinting of LIT1, uniparental disomy of 11p15 and CDKN1C mutations [2]. The full gene analysis of CDKN1C gene profile were suggestive of BWS in our case and the alteration is thought to be located in the allele inherited from the mother. Parental testing was advised which was refused by the parents. There are various endocrine and overgrowth syndromes that was considered in the differential diagnosis. These included Simpson-Golabi-Behmel syndrome (mutation in X-linked gene, GPC3), Perlman syndrome (Increased risk of neonatal mortality), Costello syndrome (missense mutation in HRAS), Sotos syndrome (Mutation in NSD1) and Mucopolysaccharidosis type IV (lysosomal storage disorder) [6]. Oral findings like macroglossia of BWS needs differentiation from other lesions like lymphangioma, idiopathic muscular hypertrophy, hemangioma, rabdomyomas, amyloidosis, cretinism and acromegaly.

Table 1: Presenting major and minor features of BWS.

lupinepublishers-openaccess-pediatric-dentistry-journal

Table 2: Oral findings of BWS.

lupinepublishers-openaccess-pediatric-dentistry-journal

The overall risk of BWS for tumor development/malignancies is estimated to range from 4 – 21%. The tumors reported with BWS are mainly embryonal tumors such as Wilms tumor, hepatoblastoma, rabdomyosarcoma, adrenocortical carcinoma and neuroblastoma [7]. The prenatal diagnosis with current technology is increasing representing an important tool to determine some features of BWS before birth. In our case, parents were highly orthodox and refuse to share the detailed prenatal and ultrasonic reports. Few misguided information’s were given by mother which was later clarified with the reports from the subsequent medical hospitals. Patient’s parents were advised for periodic follow up with genetic counselling and the possibility of surgical interventions in the medical units, but they refused to follow and changed the hospitals every time. Hence, an effort was put forward to retrieve the information’s related to the patient while giving her the primary treatment for which she reported to our dental unit. This suggest the need of awareness required in the country like Saudi Arabia, where most of the cases goes unreported/unnoticed or parent’ consent not given or the cultural and religion barriers that prevent reporting such cases. Though the patient was treated with dental fillings, the follow up of the patients is been restricted by the family members.

Conclusion

Beckwith – Wiedemann Syndrome patients usually grow and do well despite being at increased risk of childhood cancer. Hence, strict follow up, awareness of parents and cancer screening is mandatory. Families, physicians and dentists should determine screening schedule including abdominal ultrasound in every three months, blood test to measure alpha-fetoprotein in every six weeks, dental check-up in every six months and other symptomatic treatment schedule as and when required.

Read More Lupine Publishers Pediatric Dentistry Journal Articles:
https://lupine-publishers-pediatric-dentistry.blogspot.com/

Thursday, 7 January 2021

Lupine Publishers | Mouth Guards: Guardians of the Dontium

  Lupine Publishers | Journal of Pediatric Dentistry


Abstract

Children and teens are more prone to injuries while playing, with most of the impact taken by the face especially the jaws and the teeth. The most significant factor in preventing sports-related or recreational  orofacial injuries is wearing basic protective devices such as properly fitting helmets, face masks, or mouth guards. A mouth guard, custom-fitted by your dentist and worn every time you play or train, will protect against dental injury. Mouth guards are available in 3 different variants which are stock, self-adapting, custom-made mouth guards. The benefits far exceed the expenditure when considering the fees and discomfort associated with a traumatic dental injury

Keywords: Mouth Guard; Orofacial Structures; Teeth; Custom; Sports; Injuries

Introduction

Physical activity forms a very important part of life. There have been constant reports of sedentary lifestyle being associated with disease processes and over the time a lot of importance has been emphasized on physical activities be it the gym or the sports. Children and teens are more prone to injuries while playing, with most of the impact taken by the face especially the jaws and the teeth. Hence, it becomes very important to wear protective gear as these injuries might not only cause temporary impairment but also cause hindrance to the growth and development of the facial structures and also may lead to an unaesthetic appearance of the child at the later stage. The injuries occurring in sports can range from a simple ball-hit to a serious impairment of the head, face or the mouth. It is very important to wear protective gear when you are actively participating in any recreational outdoor events and also in some instances in the indoor activities with the risk of injuries. The most significant factor in preventing sports-related or recreational orofacial injuries is wearing basic protective devices such as properly fitting helmets, face masks, or mouth guards. The use of the mouth guard forms the basic minimal requirement for protecting your mouth, which should form an essential piece of the athletic equipment that the athlete should use as the standard gear equipment from a very early age.

A mouth guard, custom-fitted by your dentist and worn every time you play or train, will protect against dental injury. Well-fitted mouth guards prevent violent contact between the maxillary and mandibular dentition, which can result in soft tissue lacerations, tooth avulsions, tooth or bone fractures, endodontic injuries, and concussions [1]. This being said it has been found that injury to teeth are 60 times more likely when the athlete is not wearing the mouth guard than when he/she is wearing it. Statistically, sporting activities contribute to nearly one-third of all dental injuries [2-4]. Mouth guards help buffer an impact or blow that otherwise could cause broken teeth, jaw injuries or cuts to the lip, tongue or face. Mouth guards also may reduce the rate and severity of concussions Consequently, the dentist plays an important role in informing patients, athletes and their parents, and coaches of the importance of prevention, diagnosis, and treatment of orofacial injuries in sports and recreational activities [1].

A mouth guard should be able to fulfill the following basic requirements:

a) Encompass all maxillary teeth extending up to the distal surfaces of the second molars in class I and class II patients [4-7].

b) Encompass all mandibular teeth extending up to the distal surfaces of the second molar on class III patients [4-7].

c) Mouth guard may be abridged to cover until the distal surfaces of the first molars, in case it is known to trigger the gag reflex of the patient [4].

d) The labial flange should range to within 2mm of the sulcus [5].

e) The palatal flange should range around 2mm above the gingival margin [5].

f) The margins of the labial flange should be rounded.

g) The margins of the palatal edge should be tapered [5].

h) Be easy to clean [8,9].

i) Not impede with breathing or speech activity [4].

j) Be fabricated from a material approved by the U.S. Food and Drug Administration that can reduce the impact force to teeth, surrounding soft tissues, and bone [4,9].

k) Be comfortable and retentive and fit properly [9].

Mouth guards are available in different variants

A. Stock

B. Self-adapting

C. Custom-made

A. Stock

These are readily available over the counter in different sizes, made from polyurethane, a copolymer of vinyl acetate, or ethylene. As they are produced in bulk and are of standard sizes, they remain inexpensive, however they offer a low level of protection with little retention and is not so easily accepted by the athlete. The need to hold the mouth guard in place by clenching his or her teeth together is another disadvantage.

B. Self-Adapting

Also known as the “boil-and-bite” type mouth guard. It is readily available over the counter and made from ethylene-vinyl acetate (EVA). Herein, it is heated in hot water and then placed in the mouth to be adapted to the teeth by biting down. It is relatively inexpensive and can be replaced frequently in athletes with a mixed dentition or by individuals who are experiencing rapid growth. It has the property of re-adaptability. However, it is often bulky and does not retain its shape over time.

C. Custom-Made

The custom-made mouth guard is fabricated in a dental laboratory on a cast taken from an impression made by a dentist. The custom-made mouth guard offers the best fit and the most protection of any of the protective devices [4,5,9]. It is usually made of a thermoplastic material that is heated and adapted to the cast under pressure or with a vacuum form machine. Due to the laborious work involved in the fabrication of this type of appliance, it is expensive but retentive. The American College of Prosthodontists (ACP) recommends the use of custom mouth guards for all contact sports and for any recreational activities that may hypothetically end in orofacial injuries. Accurate maxillary and mandibular alginate impressions in centric occlusion registration recorded by a qualified dentist at approximately 5-mm opening anteriorly shall be used for fabrication of the custom trays as recommended by the ACP.4,5 The standard thickness is 4-mm, however 5- or 6-mm thickness is recommended as it will be able to protect the athlete better in case of extreme sports [4].

Mouth guards can be either single-layered or multi-layered. Currently, the most commonly used materials in the construction of custom mouth guards are EVA copolymer, soft acrylic resin, polyvinyl chloride, polyvinyl acetate-polyethylene (pEVA), and elastomers [1,8,9]. Many different designs of multi-layered materials are available. The most frequently used is a double layer made of similar materials. Dual laminated mouth guards possess an outer hard shell of styrolbutadiene co-polymerisate, and a soft inner layer of ethylene copolymer and vinyl acetate. This design of a more rigid outer material with an inner softer material will reduce the impact force transferred to the teeth due to the shock-absorbing capability of the softer layer [4,5]. The critical areas in terms of energy absorption and transmitted forces are the incisal edges of the anterior teeth and the attached (marginal) gingiva. Therefore, an optimal thickness of the device is achieved by the application of vacuum forming pressure-lamination technique of two layers of a thermoplastic sheet (EVA copolymer) and if necessary, by placing two layers of protective air-cells against the critical areas. An acrylic-resin-based elastomer may be processed over the thermoplastic sheet to improve protection for the athlete [4]. Custom-made mouth guards have proved to be the most effective means of prevention of injuries to the orofacial structures [1,4,5]. They are superior in quality, comfort, retention, and prevention of injuries when compared to stock or self-adapting devices. Although custom-made mouth guards are the most expensive type of protective oral device, they are the most highly recommended.

Conclusion

The benefits far exceed the expenditure when considering the fees and discomfort associated with a traumatic dental injury. Further, it becomes the duty of the dentist to create awareness among the athletes and make it a habit for them to wear mouth guard as a part of their equipment for sports.

Read More Lupine Publishers Pediatric Dentistry Journal Articles:
https://lupine-publishers-pediatric-dentistry.blogspot.com/

Saturday, 19 December 2020

Lupine Publishers | Comparison of the Efficacy of Plaque Removal of Listerine Smart Rinse Kids and Vi– One Junior Fluoridated Mouthwash in Children Aged 6 To 10 Years

 Lupine Publishers | Journal of Pediatric Dentistry


Abstract

Objectives: In this study, a comparative study was done on the effects of Vi-One and Listerine fluoridated mouthwashes on the reduction of dental plaque in pediatric patients between 7-11 years of age in dental clinics of Sepideh and apple in Shiraz, Iran. Listerine Smart Rinse Kids is a product of the United States and Vi-One Junior mouth wash is the domestic production of the country at Rozhin Corporation. This research was conducted by Mohammad Karimi and Hassan Dehghan in 2018-2019.

Material and Methods: In this study, 100 individuals were selected and divided into two groups of 50. During the study, no other method of controlling the plaque was used. In this method, the first group first used Vi-One mouthwash for 10 days and after two weeks of rest and minimizing dental plaque, they used Listerine for 10 days. While the second group used Listerine first, then they applied Vi- One in the same way. The results of this review were then evaluated.

Results: The mean of plaque index in total mouth and in the posterior teeth area with the use of Listerine Smart Rinse Kids was lower than that of Vi-One Junior mouth rinse. In another words, Listerine had a better effect on plaque removal than the Vi-One mouthwash in the posterior mandibular region.

Conclusion: The results show that although Listerine mouthwash had a better effect on dental plaque removal, none of the two mouthwashes had a significant difference in effects on maxillary and mandibular jaws.

Keywords: Dental Plaque; Vi- One, Listerine, Fluoridated Mouthwash; Periodontal Diseases; Plaque Index

Introduction

Currently, dental caries and gingivitis are common oral and dental diseases in this country. One element that can prevent tooth decay is Fluoride. In the oral health program of the country, fluoride mouth wash 2% was used to prevent dental caries in elementary school students all over the country [1]. In the other hand, dental plaque is an important factor in the formation of dental caries and periodontal diseases. Leo and his colleagues have identified dental plaque as the main cause of gingivitis [2]. With the use of mouthwashes, one can control the dental plaque, chemically [3,4]. In fact, mechanical plaque removal is one of the most common and effective methods for preventing caries and inflammation of the gum [5]. Fluoride mouthwash usage is contraindicated in children younger than six years of age due to the risk of swallowing and causing systemic toxicity and fluorosis [6-8]. Symptoms of acute oral fluoride toxicity in children include severe nausea, vomiting, hyper salivation, abdominal pain, and diarrhea [9]. In severe or fatal cases, these symptoms can be followed by convulsions, cardiac arrhythmias, and coma [10- 12]. Laboratory and animal data have shown that prevention the accumulation of plaque and consequently, reduction in dental plaque can be achieved when fluorides is applied topically which inhibits the bacterial multiplication [13]. The fluoride from mouth rinse is retained in dental plaque and saliva to help prevent dental caries [14]. In one review, the average caries reduction in nonfluoridated communities attributable to fluoride mouth rinse was 31% [15]. Another study in Sweden reported that the use of fluoride mouthwash along with brushing has a significant effect in decreasing of dental caries [16]. Listerine Smart Rinse Kids has been used for the purpose of this study. This product is an alcoholfree mouthwash. The ingredients include Sodium fluoride 0.02% (0.01% w/v fluoride ion), Water, Sorbitol, flavor, phosphoric acid, Sucralose, Cetylpyridinium chloride, disodium phosphate, sodium saccharin, menthol, blue 1 and green 3 [17]. One study reported that use of this mouthwash can strengthen teeth 99% better than brushing alone [18]. Another source indicated that it gives 12- hour cavity protection [19]. Vi-one Junior Mouthwash is specially designed for children. This mouth rinse contains Sodium fluoride 0.05%, Cetylpyridinium chloride 0.05% and Disodium phosphate agents. The respective flavors contain sugar-free and harmless sweetener. This brand also is an alcohol-free product [20]. The purpose of this study was to compare the efficacy of two types of mouthwashes, one the domestic mouthwash (Vi-One Junior) and the other, the brand name Listerine Smart Rinse kids fluoridated mouthwash in the removal of the dental plaque.

Material and Methods

This study was a cross-over clinical trial. The eligibilities for entering in our study were as follow:

a) Children having at least 20 teeth with no large restorative area.

b) No history of periodontal Diseases.

c) Not having any Prosthodontic or Orthodontic appliances.

The condition for withdrawal from the study, if there was any sign of reactions to any of these mouth rinses. There was no obligation to have any food regimen.

The study population consisted of 100 patients who were in a 50-member group. Before taking oral mouthwash, plaque index was minimized, and all subjects underwent tooth scaling at the beginning and, if necessary, teeth polishing were done before taking mouthwash. Oral hygiene was assessed via a plaque index. First, in both groups, the Silness-Löe plaque index was recorded. It is an Index for evaluating the thickness of the plaque in the gingival region, which measures the thickness of plaque on all surfaces (M, B, D, and L) [21].

Coding for the plaque index was carried out according to the criteria [22]:

a) Code 0: No plaque

b) Code 1: A film of plaque is adhering to the free gingival margin and adjacent area of the tooth. The plaque may be seen in situ only after application of disclosing solution or by using the probe on the tooth surface.

c) Code 2: Moderate accumulation of soft deposits can be seen with the naked eye within the gingival pocket, the tooth, or gingival margin.

d) Code 3: Abundance of soft matter can be seen within the gingival pocket and/or on the tooth, and gingival margin.

In this index, each tooth is divided into four surface area but in our purposes in the present study, we modified the surfaces area from 4 to 6; thus, we have three surfaces in the buccal area (Mesiobuccal, Midbuccal, and Distobuccal) and three surfaces in the lingual area (Mesiolingual, Midlingual and Distolingual). The first group used Vi-One & Listerine mouthwash (kids mouthwash), for 10 days in the following way. Needless to say, this process was supervised by parents at home. The kids have to gargle 5 cc ’s of Vi-One mouthwash 2 times per day for 30 seconds, and during this period of time, no other plaque control methods and tooth brushing should be used. At the end of the period of 10 days, the plaque index was recorded again. Then, the subjects were given a week to rest and stop using the mouthwash while they had permission to start brushing like before. Again, the plaque index was minimized for patients with polishing the teeth, and they used Listerine mouthwash for 10 days. In the same way, 5 cc ‘s of the mouthwash twice daily was used for 30 seconds, and at the end of the one-week period, the plaque was recorded. For the second group, in the first 10 days, mouthwash. Listerine was prescribed and in the second 10 days, the Vi-One mouthwash was applied. All procedures were performed according to the above pattern.

Results

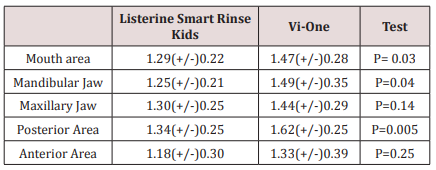
Paired T-test was used for statistical analysis of the findings. The findings showed when Listerine Smart Rinse Kids was used; the mean of plaque index in all area of the mouth (especially in the mandibular jaw and the posterior region) was significantly less than the time Vi-One was applied. However, there was no significant efficacy difference between the use of both types of mouthwash in the upper jaw and the anterior region.

There was no significant difference between the mean plaque index in Vi-One mouthwash between upper and lower jaw, and there was no significant difference between the maxillary and lower jaw in the case of Listerine Smart Rinse Kids either. The presence of this indicator in both types of mouthwash in the anterior region was significantly less than the posterior region. The mean and standard deviation of the plaque index in both groups, as well as in different regions of the mouth, are listed in Table 1.

Table 1: The amount of dental plaque in terms of area and type of Mouthwash.
lupinepublishers-openaccess-journal-pediatric-dentistry

Discussion

In general, the anti-plaque properties of mouthwashes are completed through bactericidal and bacteriostatic effects, separation of microorganisms from dental surfaces, loosening of joints to these surfaces or lowering of the surface tension of the tooth [2,21,23]. Some mouthwashes can be useful for preventing tooth decay or periodontitis [6,24]. Furthermore, mouthwashes are recommended for children and adolescents with orthodontic appliances or adults who need deep cleansing (such as curettage) [6]. These types of mouthwashes were generally used before and after surgery (especially Chlorhexidine) and have a very positive effect on the treatment of gum and ulcerative inflammation [6]. Use of this type of mouthwash should not last longer than 2 to 3 weeks due to some side effects such as staining the teeth and soft tissue staining, increased calculus deposition, unpleasant taste, burning sensation, and mucosal irritation [6]. It’s time to use this mouthwash after brushing and before bedtime, and it’s best not to eat anything after half an hour after use. Fluoride-containing mouthwashes are another type of mouth rinse that has a fairly large use. These mouthwashes have a significant effect on teeth strengthening. Fluoride in the mouthwash cause bonding with enamel and dentin, and with bonding with calcium and phosphorus, they form Fluorapatite, which is more resistant to caries than Hydroxyapatite. Fluorides also accelerate the mineralization, repair the decayed teeth surfaces, and help to increase the reverse processing of damaged tooth surface area [25,26]. Fluoride also reduces the effect of oral bacteria on teeth. It is done by interfering with the function and formation of the microorganisms. The best fluoride mouthwash protects the teeth against the acids which are produced by dental plaques. “Neglecting the oral hygiene of children leads to the accumulation of plaque and as a consequent the formation of dental calculus which will have a devastating effect on the both child’s gums and teeth” [27].

In one study, the statics showed an alcohol-free mouthwash containing a combination of 0.075% CPC and 0.05% Na F produces statistically significant reductions in dental plaque and gingivitis after three and six months compared to baseline [28]. In another research, Jessica E. Koopman, et al argued that the oral microbial community displayed remarkable resilience towards the disturbances it was presented with. The effects of the fluoride mouthwash on the microbial composition were trivial [29]. On the other side, in another study, the research showed that all four fluoride mouth rinses were effective in decreasing the plaque levels of S. Mutans [30]. In this study, we investigated the effect of two mouthwashes of Listerine Smart Rinse Kids and Vi-One in which Vi-One mouthwash in the posterior region was less efficient than the Listerine mouthwash, and the interesting point that most kids mentioned the taste of Listerine was more acceptable. Given that the contents of sodium fluoride were equal in both mouthwashes, due to the fact that Listerine mouthwash was more acceptable than the mouthwash, it could be related to the other materials present in this product which can be a part of the manufacturer’s secrets. This difference in taste can be a factor in the effect of improving Listerine’s efficacy in the posterior regions.

Conclusion

Listerine Smart Rinse Kids had a better effect on plaque removal than the Vi-One mouthwash in the posterior mandibular region. Both types of mouthwash had a better effect on the anterior region than the posterior region, but none of the two mouth rinses had a different effect on the maxillary and lower jaw. Although many popular types of mouthwash may help to control dental plaque and gingivitis, they should only be used as an adjunct to other oral hygiene measures such as brushing and flossing. Fluoride mouthwashes should be encouraged in children above the age of 6 with a high risk of caries.

Read More Lupine Publishers Pediatric Dentistry Journal Articles:
https://lupine-publishers-pediatric-dentistry.blogspot.com/


Thursday, 17 December 2020

Lupine Publishers | Acute Primary Herpetic Gingivostomatitis In A Child: Strategies for Pain Suppression and to Improve Oral Intake

 Lupine Publishers | Journal of Pediatric Dentistry


Abstract

This case report describes the management strategies and the evolution of the acute herpetic gingivostomatitis condition in a 3-year-old female child with a focus on suppressing pain and to improve oral intake with approaches to medicine and dentistry.

Keywords: Herpect Stomatitis; Drug Therapy; Child

Introduction

Herpetic gingivostomatitis is a condition that most often results from initial gingiva (gums) and oral mucosa infection with herpes simplex virus type 1 (HSV-1). While herpetic gingivostomatitis is the most common cause of gingivostomatitis in children before the age of 5, it can also occur in adults. The condition is characterized by a prodrome of fever followed by an eruption of painful, ulcerative lesions of the gingiva and mucosa, and often, yellow, perioral, vesicular lesions. HSV-1 is usually spread from direct contact or via droplets of oral secretions or lesions from an asymptomatic or symptomatic individual. Once a patient is infected with the herpes simplex virus, the infection can recur in the form of herpes labialis with intermittent re-activation occurring throughout life [1]. The pathogenesis of herpetic gingivostomatitis involves replication of the herpes simplex virus, cell lysis, and eventual destruction of mucosal tissue. Exposure to HSV-1 at abraded surfaces allows the virus to enter and rapidly replicate in epidermal and dermal cells. This results in the clinical manifestation of perioral blisters, erosions of the lips and mucosa, and eventual hemorrhagic crusting. Sufficient viral inoculation and replication allow the virus to enter sensory and autonomic ganglia, where it travels intraaxonally to the ganglionic nerve bodies. HSV-1 most commonly infects the trigeminal ganglia, where the virus remains latent until reactivation most commonly in the form of herpes labialis [2]. While most children with primary gingivostomatitis will be asymptomatic, some will experience considerable pain and discomfort and are at risk of dehydration. There are no large, well designed studies to clearly determine appropriate therapy for all children [3]. Professionals who treat children in this age group must be able to diagnose and treat common oral manifestations when necessary and should refer the child to a pediatrician for effective treatment if the presence of any systemic alteration is suspected [4]. Herpetic infections commonly affect the dental profession’s anatomical area of responsibility and the diagnosis and management of such infections fall in the purview of oral healthcare providers. To administer competent care to patients with herpetic infections, clinicians must understand the disease, its treatment, the impact the disease or its treatment may have on the patient and the extent to which the presence of a herpetic infection may impact on caregivers in the clinical process [5]. The purpose of this case report was to describe the treatment recommended for a child diagnosed with acute herpetic gingivostomatitis associated with tonsillitis and the ways to suppress pain and to improve oral intake from the perspective of medicine and dentistry.

Case Report

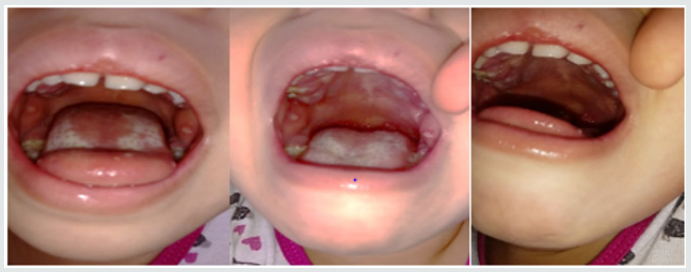
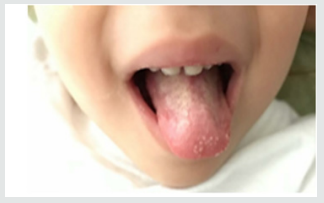
Parents of a 3-year-old and female child sought pediatrician due to inflammation in the throat of their daughter, with fever and irritability for two days, then their child feels pain in the mouth, and the drooling starts with the appearance of diffuse lesions in the oral mucosa, complaining of pain and having difficulty feeding. There was the prescription of antibiotics (amoxicillin and clavulanate potassium for oral suspension), anti-inflammatory and antipyretic. Intraoral cleaning with gauze and saline was recommended and the request for a new consultation, to eliminate the possibility of fungal contamination. The diagnosis of acute and viral primary herpetic gingivostomatitis was established (Figure 1). On intraoral examination, gingiva appeared fiery red in color and multiple vesicles were present on the attached mucosa. Multiple vesicles and ulcers were seen along the lateral border and anterior surface of the tongue. Both sided buccal mucosa revealed multiple vesicles. Her parents also complained about his bad breath during this period due to poor oral hygiene. Submandibular lymphatic glands of the kid were enlarged [6]. The pediatric dentistry was consulted because the child persisted with much pain, unable to sleep or eat (Figure 2). There was then the option of laser applications, with faster healing of ulcers and greater pain relief. There was substantial improvement in food, oral hygiene and sleep. The patient will perform control examinations, with simultaneous evaluation by pediatrician and pediatric dentistry.

Figure 1: Child oral examination two days under antibiotic prescription.

lupinepublishers-openaccess-journal-pediatric-dentistry

Figure 2: Aspect of the child’s tongue on the fourth day of drug treatment.

lupinepublishers-openaccess-journal-pediatric-dentistry

Monday, 7 December 2020

Lupine Publishers | Do Highly Aggressive Bacteria Cause Dental Caries in Some Children?

 Lupine Publishers | Journal of Pediatric Dentistry


Short Communication

Perhaps the question that many pediatric dentists may have is whether a group of bacteria play an important role in the development of dental caries in children. The results of the new research that was carried out at Umea University in Sweden, can answer this question. Researchers at Umea University discovered a new issue in relation to cariogenic different types of Streptococcus Mutans bacteria. They also investigated the adhesion performance of bacteria on children teeth with common caries and increased risk of dental caries. The results of the study, published in the EBio Medicine Journal, could lead to the development of a better way to identify high-risk patients and treat their caries. Dental caries is one of the diseases of the lifestyle, often due to poor oral and dental health and nutritional habits, which results in decreasing the level of acidic pH in the mouth [1-3]. The more likely we will see the development of dental caries if the teeth are exposed to a low salivary pH in a long period of time [4]. Low PH levels have a harmful effect on enamel; increases the growth of acid-producing bacteria, such as Streptococcus Mutans [5-8]. In this five-year study, the saliva of a large number of children was analyzed, and dental health care of these children was supervised. The researchers proved that high-risk children have more invasive types of cariogenic bacteria, and the adherence of these bacteria makes them more aggressive and more susceptible to survival. However, the results of this study showed that in some high-risk children at high risk of rot, there are certain types of highly invasive bacteria, S Mutans, which can cause caries irrespective of lifestyle. These invasive strains have unique sticky proteins called SpaP and Cnm, which increase the ability of the bacteria to survive in the antibacterial saliva of the mouth. One out of five Swedish children has such a dangerous strain and is at high risk for dental caries. These children do not respond to traditional caries prevention or treatment, and their lifestyle variables cannot predict the risk of caries [8]. Chronic dental caries and loose teeth are also risk factors for systemic diseases, such as cardiovascular disease [9,10]. Overall, 70% of tooth loss is due to tooth decay [11,12]. This article explains how up to half of the highrisk children are threatened by highly invasive types of S. Mutans.

These species can also increase the risk of cardiovascular disease and other systemic diseases in the future. Highly aggressive types also differ in terms of adhesion performance. Through biochemical studies, researchers discovered the association between the binding of SpaP and Cnm proteins and their adherence to saliva and DMBT1 protein in saliva [8]. They also showed that higher binding ability has led to an increase in dental caries over a five-year study period. In the end, to conclude this article, Dr. Stromberg believes other high-risk children have a genetic defect in their salivary receptors for bacteria, and the damaged genes may include the same genes that are involved in autoimmune diseases. But it is still important to emphasize that caries is affected by oral and dental health habits in many low to moderate risk people [8]. On the other hand, from new information on the identified types of bacteria, and their manner to start tooth decay, it can be used to improve dental care. Furthermore, the presence of these bacteria can be applied as biological markers for the early detection of high-risk patients. Moreover, their adhesion performance also can be considered as new targets for treatments [8].

Read More Lupine Publishers Pediatric Dentistry Journal Articles:
https://lupine-publishers-pediatric-dentistry.blogspot.com/

Friday, 4 December 2020

Lupine Publishers | Do Highly Aggressive Bacteria Cause Dental Caries in Some Children?

 Lupine Publishers | Journal of Pediatric Dentistry


Short Communication

Perhaps the question that many pediatric dentists may have is whether a group of bacteria play an important role in the development of dental caries in children. The results of the new research that was carried out at Umea University in Sweden, can answer this question. Researchers at Umea University discovered a new issue in relation to cariogenic different types of Streptococcus Mutans bacteria. They also investigated the adhesion performance of bacteria on children teeth with common caries and increased risk of dental caries. The results of the study, published in the EBio Medicine Journal, could lead to the development of a better way to identify high-risk patients and treat their caries. Dental caries is one of the diseases of the lifestyle, often due to poor oral and dental health and nutritional habits, which results in decreasing the level of acidic pH in the mouth [1-3]. The more likely we will see the development of dental caries if the teeth are exposed to a low salivary pH in a long period of time [4]. Low PH levels have a harmful effect on enamel; increases the growth of acid-producing bacteria, such as Streptococcus Mutans [5-8]. In this five-year study, the saliva of a large number of children was analyzed, and dental health care of these children was supervised. The researchers proved that high-risk children have more invasive types of cariogenic bacteria, and the adherence of these bacteria makes them more aggressive and more susceptible to survival. However, the results of this study showed that in some high-risk children at high risk of rot, there are certain types of highly invasive bacteria, S Mutans, which can cause caries irrespective of lifestyle. These invasive strains have unique sticky proteins called SpaP and Cnm, which increase the ability of the bacteria to survive in the antibacterial saliva of the mouth. One out of five Swedish children has such a dangerous strain and is at high risk for dental caries. These children do not respond to traditional caries prevention or treatment, and their lifestyle variables cannot predict the risk of caries [8]. Chronic dental caries and loose teeth are also risk factors for systemic diseases, such as cardiovascular disease [9,10]. Overall, 70% of tooth loss is due to tooth decay [11,12]. This article explains how up to half of the highrisk children are threatened by highly invasive types of S. Mutans.

These species can also increase the risk of cardiovascular disease and other systemic diseases in the future. Highly aggressive types also differ in terms of adhesion performance. Through biochemical studies, researchers discovered the association between the binding of SpaP and Cnm proteins and their adherence to saliva and DMBT1 protein in saliva [8]. They also showed that higher binding ability has led to an increase in dental caries over a five-year study period. In the end, to conclude this article, Dr. Stromberg believes other high-risk children have a genetic defect in their salivary receptors for bacteria, and the damaged genes may include the same genes that are involved in autoimmune diseases. But it is still important to emphasize that caries is affected by oral and dental health habits in many low to moderate risk people [8]. On the other hand, from new information on the identified types of bacteria, and their manner to start tooth decay, it can be used to improve dental care. Furthermore, the presence of these bacteria can be applied as biological markers for the early detection of high-risk patients. Moreover, their adhesion performance also can be considered as new targets for treatments [8].

Read More Lupine Publishers Pediatric Dentistry Journal Articles:
https://lupine-publishers-pediatric-dentistry.blogspot.com/

Friday, 27 November 2020

Lupine Publishers | Isolation and Characterization of Candida Species from Dental Caries in Deciduous Teeth

 Lupine Publishers | Journal of Pediatric Dentistry


Abstract

The present study showed the presence of Candida tropicalis as a mayor fungus isolated of dental caries in deciduous teeth.

Keywords: Dental Caries, C Tropicalis

Introduction

Candida species is the most frequent fungus found in the oral cavity [1]. This microorganism provokes a pathology known as candidiasis in many forms [2], however, this yeast can be found in dental decay lesions, gingival and periodontal disease [3]. Candida albicans is the most frequent species of microorganism in all these lesions [4], however, other Candida species as Candida tropicalis, C glabrata, C. Krusei, C. guillermondii are less present in oral cavity [5]. Dental caries, is the most frequent lesions over world and its etiology is eminently microbial, being the Streptococcus mutans who produce the teeth demineralization and destruction [6]. The main of this study is to isolate and characterize the Candida species from dental caries in deciduous teeth.

Materials and Methods

Fifty children, female and male, from pediatric dentistry of Universidad Andina del Cusco, between 4 and 6 years old with dental caries are selected. Before remove and rehabilitate the dental caries, with a dental spoon excavator it was collected a caries sample and stored in 0.9% NaCl [7]. After that, the samples were sonicated and 100 ul aliquot was placed in CHROM Agar Candida medium (CHRO Magar, Paris, France) and were incubated for 48 hours at 37°C [7]. It followed the CHRO Magar Candida manual instructions to determine the presence of Candida species.

Results

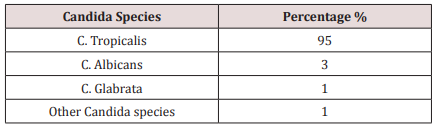
The Candida species most present in the dental caries in deciduous teeth were the C. tropicalis. Other species of Candida are found in less percentages (Table 1).

Table 1.

lupinepublishers-openaccess-journal-pediatric-dentistry

Discussion

Candida species is the most fungus found in oral cavity being the C Albicans the most pathological yeast of the Candida species [4]. This microorganism was found in many oral lesions as candidiasis, dental caries, gingival and periodontal disease [2,3]. Other Candida non albicans are founded in less frequency. However, C. tropicalis and C. glabrata has been described as emerging pathogens in recent years [8]. In the present study, C. tropicalis was presented in the most cases of dental caries in deciduous teeth, being this data corroborated with other studies who the main pathogen is the C. tropicalis. Most studies, in fact, found that the C. albicans as the mayor pathogen isolated from dental caries [6,9,10]. This difference of data can be explained by the geographical location of patients where Candida species can be found in amounts depending on the geographical area. In this study, other Candida species, can be found in less amounts. Despite limitations, the data obtained in the present study demonstrated the high rate of C. Tropicalis in dental caries in deciduous teeth, however, has not been determined which factor is involved in the pathogenesis of dental caries produced by C. tropicalis. It is also important study the oral microbiome in dental caries to dilucidated the role of Candida species, mainly C. tropicalis, in the development of dental caries in deciduous teeth.

Conclusion

Candida tropicalis is the most fungi founded in dental caries lesion in deciduous teeth in child between 4 and 6 years old.

Read More Lupine Publishers Pediatric Dentistry Journal Articles:
https://lupine-publishers-pediatric-dentistry.blogspot.com/

Saturday, 7 November 2020

Lupine Publishers | Management of Perinatal and Infant Oral Health

 Lupine Publishers | Journal of Pediatric Dentistry


Abstract

Mothers in the perinatal stage and infants should be identified and evaluated for the risk of dental caries. Early childhood caries can lead to detrimental consequences in the primary dentition. This entails that oral health care advice regarding oral hygiene, diet, fluoride and dental management be provided to minimize the risk factors and optimize the protective factors to improve the longterm oral health outcomes for both the mother and her infant.

Keywords: Perinatal Oral Health; Infant Oral Health; Early Childhood Caries

Introduction

The perinatal period is vital for the holistic well-being of pregnant women. It is defined as a time span which commences when the 20th to 28th week of gestation is completed and ends at 1 to 4 weeks subsequent to birth of a child [1]. Early childhood caries (ECC) and severe form of ECC (s-ECC) start as soon as teeth start to erupt, develop on every surface of a primary tooth, have a rapid progression with a long-term detrimental impact on the primary dentition [2]. The long term sequelae of ECC include a greater risk of new carious lesions in both the primary and permanent dentitions, [3,4] high cost of treatment, [5] hospital stay and emergency room visits [6,7] loss of school time, [8] diminished cognitive ability [9] and a poor oral health-related quality of life [10]. Hence the oral health of both the mother and the future child are instrumental in preventing and arresting the disease process to manage early childhood caries during this phase [11].

Epidemiology

This chronic, infectious disease affects the general population however it is 32 times more likely to occur in infants from low socioeconomic status, with high sugar diet and whose mothers have a low education level [12-14] It affects 1-17% children in developed and 70% children in under-developed countries [15]. Epidemiologic evidence shows that the highest prevalence of ECC is reported from Africa and South-East Asia [16]. The prevalence of ECC among Indian children between 8–48 months is 44% [17]. A study from Sri Lanka reports an incidence of 23% ECC among 1-2-year old’s [18]. North American prevalence of ECC ranges from 11-72% and over 28 % children have caries by the time they reach kindergarten [19,20]. Pakistan has a variation in prevalence of ECC ranging 27.9% - 51% [21,22].

Anticipatory Guidance According to Caries Risk

New mothers and infants are seen by the medical health care professionals earlier and more often than dentists. It is therefore important that they understand the dynamic multifactorial etiology and risk factors for ECC prevention counselling in pregnant women/caregivers and encouraging a dental home visit at age 1 [23]. In some instances, pregnant women may defer dental care, experience unwillingness of dentists to provide oral care [24-27] or may be unaware of the implications of poor oral health for their pregnancy [28,29]. Hence early identification of mothers with poor oral health/high caries risk and timely delivery of educational information and prevention for themselves and their unborn child can help reduce the incidence of ECC, prevent the need for dental rehabilitation and improve their oral health [30-32]. Caries-risk assessment for infants allows the determination of relative risk for dental disease to prevent disease by identifying and minimizing risk factors (plaque accumulation, diet, lack of topical/systemic fluoride, high frequency of sugar containing medicines) and optimizing protective factors (oral hygiene practices, fluoride and fissure sealants) when the primary dentition starts to erupt [33]. The current trend shows more emphasis on prevention and arrest of the disease processes to manage ECC. This is attributed to the costly and high-risk restorative treatment for ECC since it often entails the use of sedation and/or general anesthesia and a high recurrence rate [34,35]. The chronic disease management approach encompasses engagement of parents to facilitate preventive measures and temporary restorations of the lesion to defer advanced restorative care [36]. An active surveillance methodology entails monitoring caries progression in children and setting up prevention programs for managing incipient carious lesions [37]. An Interim therapeutic restorations (ITR) is a form of temporary tooth restoration in young children until compliance improves and conventional cavity preparation and restoration is possible [38].

Oral Health Care Advice to Pregnant or Lactating Mothers

Physicians, dentists, and nurses impart educational advice for mothers during the perinatal period. The preventive advice should include timely brushing with fluoridated toothpastes and use of sugar free gums. The dietary advice should address the quality and quantity of nutritional food along with food cravings that may raise the caries risk. Dental procedures which are considered safe during all trimesters of pregnancy include oral assessment, prophylaxis, local anaesthetic, regular treatment and radiographs with shielding (optimal in second trimester). If, however there is discomfort the elective treatment may be deferred. Breast feeding of infants should be tailored with food over a year or longer but should not be ad libitum. It provides nutritional, developmental and psychological health advantages with a significant decrease in the risk for acute and chronic diseases. It may also transfer maternal medication to infants under 6 months hence use cautiously. It provides awareness of health consequences of tobacco use and exposure to secondhand smoke in children [39-43].

Oral Health Care Advice for Infants

An infant should be taken for an initial evaluation to a dental home by the age of one by the pediatricians and the general practitioners. This attains the medical and dental history of both the child and parents, allows oral assessment with a demonstration on age appropriate gum and tooth cleaning, brushing the teeth twice a day with an optimum level of fluoridated toothpaste (smear or rice sized for children under 3), dietary advice (avoid sugar by bottle, sippy cup, sugar between meals, 4-6 ounces of 100% fruit juice per day for 4-6 year old children, systemically administered fluoride (if the drinking water is unfluoridated) and professional fluoride application if caries risk is high, injury prevention advice for facial trauma (objects, cords, pacifiers, car seats, electric cords), advice on teething with excessive salivation areas of intermittent discomfort (oral analgesics, chilled teething rings, over the counter teething gels), management of atypical frenum attachments (frenectomy or frenuloplasty to facilitate breast feeding) and counselling regarding non-nutritive habits such as digit or pacifier sucking, abnormal tongue thrust or bruxism (wean before skeletal dysplasia or malocclusion) [33,44,45].

Conclusion

It is very important to design and implement caries assessment in order to identify the caries risk for infants and expectant mothers/lactating mothers. This will allow effective education on oral health via motivational interviewing techniques to help improve oral behaviour and timely implementation of caries preventive measures to help change the trajectory of oral health of a mother and her infant.

Read More Lupine Publishers Pediatric Dentistry Journal Articles:
https://lupine-publishers-pediatric-dentistry.blogspot.com/
Friday, 30 October 2020

Lupine Publishers | Early Interventions to Promote Pediatric Oral Health

 Lupine Publishers | Journal of Pediatric Dentistry


Introduction

It is well established that dental caries is the most prevalent and preventable chronic disease among children [1]. Preschool years are a critical period of development; poor oral health can create lifelong consequences for one’s overall health outcomes. If oral health needs are not addressed earlier, it may negatively impact a child’s ability to eat, sleep, learn or socialize, further damaging the child’s psychological and social dimensions of well-being [1,2]. Another negative outcome is the need for dental surgery as it accounts for 31% of all surgeries among children under the age of 6 [3]. Caries in childhood is a predictor for adult oral health; this may affect other health conditions such as diabetes or cardiovascular disease over time [2]. Caries is a multifactorial chronic disease influenced by biological, lifestyle, and behavior factors [4]. Risk factors for early childhood caries include: bacteria transmission from mother to infant [5]; the social determinants of health [2]; parental knowledge [6], attitudes and behaviors towards oral health (e.g., diet, pacifier use, and daily tooth brushing); prolonged bottlefeeding practices [7], and cultural beliefs around primary or “milk teeth” [8,9]. Oral health is connected to socioeconomic status; those with higher income are more likely to access a dentist and have dental insurance coverage [10]. It is important to identify effective interventions targeting preschool children in order to collaborate with the Family Health Division, other Regional departments, and community partners to meet the emerging oral health needs of our community.

Future Directions

The recommendations made decades ago to promote early childhood oral health by establishing a dental home before the first birthday, and providing education and preventive interventions, are crucial components of effective care [11]. Now, as then, dental professionals play a pivotal role by assessing and monitoring the individualized risk of each pediatric patient and applying the latest evidence-based approaches to disease prevention and treatment [12]. Effective care requires a constant review the literature, ongoing assessment of the rapidly evolving understanding of the oral microbiome and its effect on caries progression and implementing management protocols as early as possible. Beyond the clinic, however, it is equally important for dental teams to provide parents/caregivers with the knowledge and skills to make appropriate dietary and lifestyle choices for their children, while ensuring proper oral hygiene and regular dental visits. It is only through these combined efforts that oral disease can be prevented.

Key Takeaways

a) Establishing a dental home before a child’s first birthday ensures a safe place for comprehensive care and allows clinicians to develop recommendations specific to that patient’s individualized risk.

b) Assessing caries risk and implementing preventive strategies are critical elements of pediatric care, particularly for preschoolers and children with special

c) health care needs.

d) Parents and caregivers must be given the means to mitigate the child’s caries risk through effective self-care and healthy lifestyle choices, and by working with dental teams to verify whether the risk management regimen has been effective.

e) It is only through the combined efforts of dental professionals and parents/caregivers that oral disease can be prevented.

Read More Lupine Publishers Pediatric Dentistry Journal Articles:
https://lupine-publishers-pediatric-dentistry.blogspot.com/
Friday, 23 October 2020

Lupine Publishers | Lasers & Pedodontics

 Lupine Publishers | Journal of Pediatric Dentistry


Introduction

The medical terms such as magical and lightening quick are used to represent lasers [1]. Theodore H. Maiman in 1960 coined the term laser, which was initially termed as maser which stands for “microwave amplification by stimulated emission of radiation”. However, the term LASER is an acronym for light amplification by stimulated emission of radiation [2,3]. Three types of lasers used for surgical therapy in the oral cavity are neodymium lasers - YAG (Nd: YAG), of argon (Ar) and carbon dioxide (CO2) [3]. Lasers have largely replaced scalpels and other instruments in the field of medicine because of its advantages [4-6]. Different laser wavelengths have different absorption coefficients wherein laser energy can be absorbed or transmitted based on the structure of the target tissue. The presence of water, which is an essential component of all biologic tissues, is important for the use of lasers [2,6]. For hard tissues, Er lasers are used whereas any laser can be used for soft tissue components [2,6,7].

Applications of Lasers in Pediatric Dentistry

For caries removal

Erbium group of lasers are preferred for deep enamel, dentin, and caries removal, whereas the Nd: YAG laser is designated for superficial pigmented caries removal. The other advantages being the non-requirement of anesthesia and the use of conventional drills, which cause micro-fracture of tooth during preparation [1,2]. During cavity preparation, after the removal of enamel, the settings are adjusted to reduce the energy levels as dentin is less mineralized and has higher water content than enamel [2].

Removal of restorations (including amalgam)

Lasers should never be directed towards amalgam and should be pointed towards the surrounding enamel to create a small trough, and hand instruments are used to elevate the restoration out and later the cavity preparation is completed. Also, other restorations like composite and glass ionomer can be removed/replaced [1,2].

Preventive treatment

At the early stages after tooth eruption, enamel grooves are the site of early caries. This can be treated using lasers by cleaning, sterilizing and restoring the same. Also, many studies have reported that etched enamel by erbium has properties like the acid-etched enamel [2].

Treatment of peri coronal problems in erupting teeth

Lasers are used in non-contact mode to remove the pericoronal tissue covering the newly erupted tooth, which might help in relieving any discomfort, swelling, or infection in the tissue overlying the emerging tooth [2,9].

Gingival re-contouring and orthodontic purposes

Excess gingival growth by the use drugs or by poor oral hygiene, and during other surgical procedures including orthodontics requires removal of tissue in some cases. This can be accomplished by the use of lasers which can be done without the need for a local anesthesia. Use of topical anesthetic can be supplemented for the treatment procedures [8].

Treatment of ankyloglossia

Tongue is stabilized with a hemostat and the frenum is revised, while avoiding any damage to the glands on the floor of the mouth [8].

Treatment of aphthous ulcers and herpetic lesions

Use of low power settings with the laser energy directed at the target tissue in the non-contact mode, for a duration of 15-30 second intervals for three to four times, helps in pain relief. The use of laser in the initial stages in herpes labialis may prevent its further progression and provide a palliative effect for the area and prevent its progression [2,8].

Pulp therapy

The ability of laser to close the dentinal tubules and provide a sedative effect on pulpitis has somewhat encouraged the use of laser in indirect pulp capping [8]. Also, the use of lasers to sterilize the canals and also create a hemostatic environment in adjunct to the conventional procedures has created a stir for the use of lasers.

Other surgical procedures

Other surgical procedures like apicectomies and amputation of impacted teeth underneath the bone also can be performed with the use of lasers. The erbium lasers are ideal for these surgeries and a variety of tips, settings and water sprays can be used. Softtissue ablation does not require water spray whereas removal of bone needs to be done with water [2,9].

Advantages of laser therapy

a) Decreasing inflammation and pain.

b) Reduced healing period [3,4,9].

c) Good & faster healing properties.

d) Reduced chances of infection.

e) Reduced bleeding.

f) Instant hemostatic achievement.

g) Good margins.

h) Patients apprehensive for blade.

Contraindication of Laser Therapy

a) Patients with pacemakers, however it can be used with precautions in some case [9].

b) Patients who are sensible to light.

c) In epileptic patients.

d) In patients with antecedent of arrhythmia or chest pain.

e) Avoided on tumorous tissues or benign tumors with malignant potential.

Conclusion

Natural light is and has been considered as the curator [10]. Lasers have gained tremendously over the years; its advantages far outweigh its disadvantages. However, there still exists some limitations as well as some contraindications, which stop its usage with the cost factor being one of it. Nevertheless, it would be the future instrument of choice for most of the procedures included in all the fields with surgery, periodontics, endodontics and orthodontics being one of them.

Read More Lupine Publishers Pediatric Dentistry Journal Articles:
https://lupine-publishers-pediatric-dentistry.blogspot.com/
Read More Lupine Publishers Articles:
https://lupinepublishers.blogspot.com/