Showing posts with label Open Access Journal of Pediatric Dentistry. Show all posts

Wednesday, 20 September 2023

Lupine Publishers | Treatment of Infected Primary Teeth using Modified Antibiotic Paste

 Lupine Publishers | Journal of Interventions in Pediatric Dentistry


Abstract

Objectives: Treatment of pulpectomized primary molars with chronic infection using a mixture of three antibiotics: Metronidazole, Ciprofloxacin, and Doxycycline mixed with Macrogol or Propylene Glycol (modified 3MIX-MP) as an intracanal medicament before the complete cleaning and shaping and obturation.

Study design: A 7 years old child with infected primary molar came to our clinic for treatment. A detailed medical history and drug allergy were taken. Ciprofloxacin (500mg), Metronidazole (500mg) and Doxycycline (100mg) tablets divided in the proportion of 1:3:3 (one part of Ciprofloxacin, three parts of Metronidazole, and three parts of Doxycycline) and mixed with propylene glycol to form an ointment. Biomechanical preparation was done. The modified 3MIX-MP paste placed in the pulp chamber then temporary filling. The patient was recalled after 2 weeks. The tooth was obturated and restored then a stainless-steel crown placed. Then reevaluated at 3rd, 6th, and 12th months.

Results: Excellent clinical and radiographic success when compared to conventional pulpectomy and non-instrumentational lesion sterilization tissue repair therapy.

Conclusion: Treatment of Primary molar with modified 3MIX-MP, followed by instrumentation and obturation provided excellent clinical and radiographic success when compared to non-instrumentational lesion sterilization tissue repair therapy.

Keywords: Pulp infection; Pulpectomy; Modified antibiotic paste; Primary molars; Chronic, infected pulp; Modified 3 MIX-MP; Pulpectomy; Triple antibiotic paste; Primary teeth

Introduction

The first topical antibiotic introduced to endodontics was Grossman’s polyantibiotic paste in 1951, later many topical antibiotics have been introduced with varying combinations, few of those include Septomixine forte; PBSC (Combination of Penicillin, Bacitracin, Streptomycin and Caprylate sodium), and Clindamycin. However, none of these combinations has proven to be 100% successful in eliminating all the bacterial strains from the root canal system [1-5].

Materials and Methods

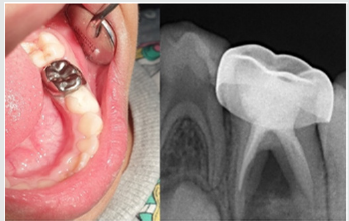
A child aged 7 years old with chronic infection related to the lower left primary molar came to our clinic for treatment of the infected molar (Figure 1). Treatment was explained to the parents and written informed consent was taken from parents before start of the study. A detailed medical history and previous illness with a history of drug allergy were taken from the parents, then the mentioned primary molar was diagnosed clinically, the molar was badly decayed with signs of chronic infection such as: gingival swelling and tenderness to percussion. A radiographic examination was done and a per radicular radiolucency was found, with no excessive root resorption. Commercially available chemotherapeutic agents such as Ciprofloxacin (500mg) (Omacip, NPI Pharma, Oman), Metronidazole (500mg) (Anazol, JPI, Saudi Arabia), and Doxycycline (100mg) (Tabocine, TPMC, Tabuk) tablets were obtained [6,7], then these tablets were crushed into fine powder using sterile porcelain mortar and pestle. These powdered drugs were transferred into three separate sterile glass containers, capped tightly and stored in the refrigerator until its use. Just before use, each powdered drug was divided in the proportion of 1:3:3 (one part of Ciprofloxacin, three parts of Metronidazole, and three parts of Doxycycline) and were mixed with propylene glycol and polyethylene glycol to form an ointment. Reddy GA et al. Trairatvorakul and Detsomboonrat, Jaya et al., Cruz et al. also followed the similar protocol of preparation of 3MIX antibiotic paste [8-11].

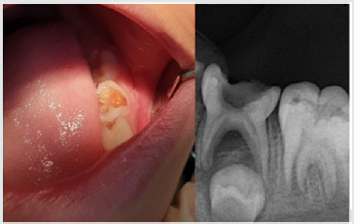
Figure 1: Preoperative illustration.
Lupinepublishers-openaccess-pediatric-dentistry-journal

Figure 2: Postoperative illustration.
Lupinepublishers-openaccess-pediatric-dentistry-journal

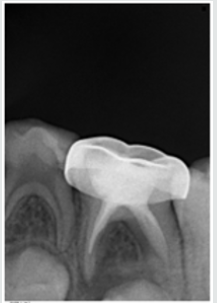
Preoperative clinical and radiographical signs and symptoms were recorded. The tooth was anesthetized using 2% Xylocaine with 1:80,000 adrenalin and isolated with rubber dam. Access opening was performed using round bur, Biomechanical preparation was done using k files from size 10–25. The root canals were chemically cleaned with 1% sodium hypochlorite solution and dried with paper points. The 3MIX-MP paste placed in the pulp chamber and pressed with dampened cotton pellet and temporized with Cavit. The patient was recalled after 2 weeks for evaluation. The tooth was obturated with reinforced zinc oxide eugenol (IRM, Dentsply) using lentulo spirals. Then restored with glass ionomer restorative material (Riva self-cure, SDI) and reinforced by placing stainless steel crowns (Figure 2). Further, the treated tooth was reevaluated both clinically and radiographically at 3rd, 6th, and 12th months intervals postoperatively (Figure 3). At the time of revisits, the tooth was examined clinically for any signs of failure that includes a report of spontaneous pain, presence of swelling, sinus tract and mobility. Radiographic evaluation was done to check the radiolucency and signs of resorption. The tooth was asymptomatic without pain, swelling, sinus tract and mobility also there was no increase in furcation radiolucency or development of root resorption which is abnormal for the age of the child.

Figure 3: 12 months Follow up.
Lupinepublishers-openaccess-pediatric-dentistry-journal

Results

Excellent clinical and radiographic success when compared to conventional pulpectomy and non-instrumentational lesion sterilization tissue repair therapy.

Discussion

This study was approved by “Research Ethics Committee, Taibah University, College of Dentistry, TU CD-REC”. The concept of Non-Instrumentation Endodontic Therapy introduced by Niigata university school of dentistry; Japan has gained reputation as it proved to attain 100% sterility in the root canal system [12- 15]. They recommended a technique similar to pulpotomy where debriding only the pulp chamber of chronically infected primary teeth and placing medicament (ciprofloxacin, metronidazole, and minocycline) near the root orifice without preparing the radicular portion. Cruz et al. suggested vehicles such as macrogol and propylene glycol (3MIX–MP) and demonstrated that these vehicles will carry the medicament deep into the dentinal tubules, thus aid in effective eradication of bacteria [11]. Metronidazole (Nitroimidazole compound) due to its wide spectrum of antibacterial action against anaerobes (Ingham et al. 1975) gained importance as the 1st choice drug for triple antibiotic paste preparation [16,17]. Metronidazole binds to the DNA and disrupts its helical structure and thus leads to rapid cell death. However, metronidazole even at higher concentrations could not eradicate all the bacteria thus indicating the necessity of some additional drugs to sterilize these lesions [15]. The two other antibacterial drugs, i.e. ciprofloxacin, and minocycline, in addition to metronidazole (3MIX) were added in an effort to eliminate all bacteria [8,10,15,18]. The 2nd choice of drug ciprofloxacin is a synthetic fluoroquinolone with rapid bactericidal action. It inhibits the enzyme DNA gyrase of bacteria. It exhibits very potent activity against Gram-negative bacteria but very limited activity against Gram-positive bacteria. Most of the anaerobic bacteria are resistant to ciprofloxacin. Hence, it is often combined with metronidazole in treating mixed infections. The 3rd choice of drug was minocycline. It is a semisynthetic derivative of tetracycline, primarily bacteriostatic, inhibiting protein synthesis by binding to 30S ribosomes in susceptible organisms and exhibits broad spectrum of activity against Gram-positive and Gramnegative microorganisms [3].

In our present study we replaced Minocycline with Doxycycline due to the difficulty in obtaining Minocycline, and before using the Doxycycline as a replacement we have done further searches for previous studies to ensure that both medications have the same effect and this replacement will not affect the efficacy of the mentioned mix. The already done studies concerning the difference between both Doxycycline and Minocycline revealed that still no statistically significant differences had been demonstrated in clinical trials when comparing Minocycline with Doxycycline, and investigators had concluded that both are equally effective. And they differ in their adverse event profile [19]. Considerably fewer adverse effects have been reported for Doxycycline than Minocycline; the adverse effects for Minocycline are 5 times more common than for Doxycycline [19]. We have followed the same protocol of Reddy GA et al. of extirpation of both necrotic coronal as well as all accessible radicular pulp tissue and then complete obturation, which is reported successful clinically over 16th month follow-up [9]. Although the previous studies have demonstrated that the LSTR (Lesion Sterilization Tissue Repair) technique as one of the successful techniques for management of chronically infected primary teeth, the controversies aroused about the duration of therapeutic activity of the medicament and leaving the infected material in the radicular region. So that the present study planned where in treated tooth were revisited after 2 weeks for medicament removal and obturation.

Conclusion

All the primary teeth with chronic infection which were treated using modified 3MIX-MP, followed by the instrumentation and obturation provided excellent clinical and radiographic success when compared to conventional pulpectomy and noninstrumentational lesion sterilization tissue repair therapy.

Read More About Lupine Publishers Journal of Pediatric Dentistry Click on the Below Link:

https://lupine-publishers-pediatric-dentistry.blogspot.com/


Wednesday, 26 July 2023

Lupine Publishers | Varied clinical and Oral Presentation of Beckwith – Wiedemann Syndrome - Report of a Case from Saudi Arabia

 Lupine Publishers | Journal of Pediatric Dentistry


Abstract

Beckwith – Wiedemann syndrome is congenital, genetic and epigenetic pathologies with low prevalence and diverse clinical presentations. It is characterized by triad of omphalocele, macroglossia and gigantism. This syndrome has been widely studied with a current emphasis on improvement of prenatal diagnostic techniques and a multidisciplinary approach towards treatment. We report a case of BWS from Saudi Arabia, with unique presentations and misleading history which delayed diagnosis, due to cultural and religion constraints.

Keywords:Congenital; Epigenetic; Genetic; Prenatal

Introduction

Genetic and epigenetic changes or a human genomic imprinting disorder is characterized by phenotypic variability which might shows its occurrence either as sporadic or inherited. The pathology presents wide range of effect on psychological and social wellbeing of patients and families. One such congenital, multigenic, multisystem human genomic imprinting disorder with complex molecular etiology and variable complex phenotype is Beckwith – Wiedemann Syndrome (BWS). Beckwith-Wiedemann Syndrome is most common overgrowth syndrome described by Beckwith in 1963 and Wiedemann in 1964 with similar findings. It is rare congenital deformity with low prevalence but at same time have high prevalence within genetic abnormalities of overgrowth [1]. The presentation of triad features of omphalocele (exomphalos), macroglossia and gigantism was described earlier as EMG syndrome which now is referred as Beckwith – Widemann Syndrome. The incidence of BWS reported is approximately 1:13700 births and the major cause is thought till date is genetic and epigenetic defects within the chromosome 11p15.5 regions [2].

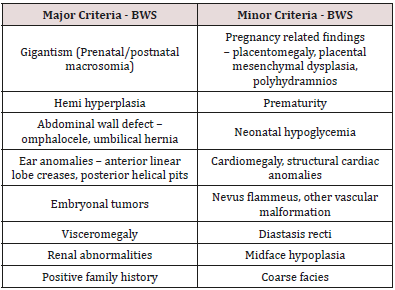
BWS presents wide array of clinical manifestations such as congenital abdominal wall defects as hernia (exomphalos), gigantism, macroglossia, nevus flammeus, ear pits/hearing loss, midface hypoplasia, cardiac anomalies, hemihypertrophy, genitourinary anomalies and musculoskeletal abnormalities. To standardize the diagnostic criteria various attempts have been made to classify the major and minor criteria. Elliot et al described the diagnosis of BWS with the presence of either three major features (abdominal wall defect, macroglossia, gigantism) or two major and three minor features (ear pits, nevus flammeus, hemi hyperplasia, nephromegaly, neonatal hypoglycemia) [3]. In spite of diverse clinical presentations of BWS, most of the cases do not show characteristic features at birth but develop later in life. Also, children with BWS have significantly increased risk of cancer during early childhood which need strict follow up and monitoring. Here, we present a case of BWS with unique dental and medical presentation and its differential diagnosis with literature review.

Case Report

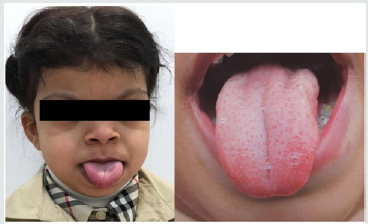
A 5-year-old female patient, accompanied by her mother, presented to the dental unit with complaint of decay tooth in upper front region of mouth. Extra oral examination revealed dysmorphic features, coarse facies and developmental problems (Figure 1). Intra oral examination of hard tissue showed high arched palate, decayed teeth in relation to 51, 52, 55, 61, 62, 74, 75, 84,85. Oral soft tissue examination revealed macroglossia, enlargement of fungiform papillae and mild loss of filiform papillae (Figure 2). Speech and feeding difficulty were noticed due to macroglossia. History revealed she is the youngest 7th child born out of consanguineous marriage in 30th week by cesarian section. She has a chronic history of constipation for 9 months of age. She passes hard stool once in every 8 to 10 days, by spending long time in washroom. It is associated with decrease in appetite and abdominal pain. She was given Movicol (half the adult dose) twice a day for constipation without any medical prescription. She was also tried with lactulose, glycerin suppository and mineral oil. Under medical supervision fleet enema and contrast enema were performed to relieve constipation and to rule out Hirschsprung disease.

Figure 1: Photograph showing dysmorphic features and hypertelorism.

Lupinepublishers-openaccess-pediatric-dentistry-journal

Figure 2: Macroglossia with enlarged fungiform papillae and loss of filiform papillae.

Lupinepublishers-openaccess-pediatric-dentistry-journal

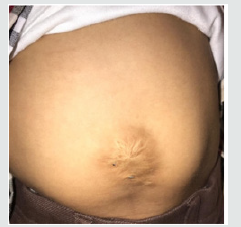
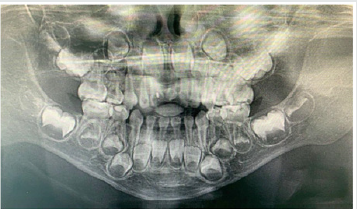
Other medical findings noticed omphalocele, ear pits, large child at 90th centiles, large rounded eyes with hypertelorism, abdominal soft lax, enlargement of kidney, distention of left renal pelvis with significantly distended urinary bladder, abnormal anatomy of the colon located in left abdomen and partial colonic non – rotation with no evidence of obstruction (Figure 3). Based on the clinical and past medical history a diagnosis of Beckwith – Wiedemann Syndrome (BWS) was made. Series of laboratory investigation were reviewed which presented negative urine examination, alpha – fetoprotein, karyotype, microarray and methylation analysis for BMS. Patient was advised for gene analysis and targeting testing for parents. The gene analysis of CDKN1C gene showed heterozygous alteration consistent with BWS but targeting gene tests were refused by parents. Panoramic radiograph was advised considering the patient chief complaint, which revealed multiple developing permanent tooth buds, protrusion of anterior teeth, open bite and increase in mandibular dimension (Figure 4). Under preventive measures the patient was treated for the decayed teeth and is under follow up from past 6 months.

Figure 3: Photograph showing abdominal wall defect with surgical scar.

Lupinepublishers-openaccess-pediatric-dentistry-journal

Figure 4: Panaromic radiograph showing multiple developing permanent tooth buds, open bite and increased mandibular dimension.

Lupinepublishers-openaccess-pediatric-dentistry-journal

Discussion

Diagnostic criteria for BWS is still a matter of research due to its varied clinical presentations and overlapping features with other various conditions. The presence of major and minor findings is generally helpful in establishing the clinical diagnosis (Table 1). The oral findings as mentioned in the literature and observed in our case has been tabulated in Table 2 [4,5]. The incidence of BWS is difficult to assess in Saudi Arabia, as most of the cases goes undiagnosed and unnoticed. Also attributed to its diverse clinical presentation and difficulty in diagnosing. In the present case, features of macroglossia, macrosomia, omphalocele, abdominal wall defect (treated immediately after birth and surgical scar observed clinically), Renal involvement, ear crease, high arched palate, open bite and increased mandibular dimension, leads to the diagnosis of BWS. Various molecular mechanisms and alterations have been involved in BWS such as abnormal methylation of H19DMR, loss of imprinting of IGF2, chromosomal rearrangements, loss of imprinting of LIT1, uniparental disomy of 11p15 and CDKN1C mutations [2]. The full gene analysis of CDKN1C gene profile were suggestive of BWS in our case and the alteration is thought to be located in the allele inherited from the mother. Parental testing was advised which was refused by the parents. There are various endocrine and overgrowth syndromes that was considered in the differential diagnosis. These included Simpson-Golabi-Behmel syndrome (mutation in X-linked gene, GPC3), Perlman syndrome (Increased risk of neonatal mortality), Costello syndrome (missense mutation in HRAS), Sotos syndrome (Mutation in NSD1) and Mucopolysaccharidosis type IV (lysosomal storage disorder) [6]. Oral findings like macroglossia of BWS needs differentiation from other lesions like lymphangioma, idiopathic muscular hypertrophy, hemangioma, rabdomyomas, amyloidosis, cretinism and acromegaly.

Table 1: Presenting major and minor features of BWS.

lupinepublishers-openaccess-pediatric-dentistry-journal

Table 2: Oral findings of BWS.

lupinepublishers-openaccess-pediatric-dentistry-journal

The overall risk of BWS for tumor development/malignancies is estimated to range from 4 – 21%. The tumors reported with BWS are mainly embryonal tumors such as Wilms tumor, hepatoblastoma, rabdomyosarcoma, adrenocortical carcinoma and neuroblastoma [7]. The prenatal diagnosis with current technology is increasing representing an important tool to determine some features of BWS before birth. In our case, parents were highly orthodox and refuse to share the detailed prenatal and ultrasonic reports. Few misguided information’s were given by mother which was later clarified with the reports from the subsequent medical hospitals. Patient’s parents were advised for periodic follow up with genetic counselling and the possibility of surgical interventions in the medical units, but they refused to follow and changed the hospitals every time. Hence, an effort was put forward to retrieve the information’s related to the patient while giving her the primary treatment for which she reported to our dental unit. This suggest the need of awareness required in the country like Saudi Arabia, where most of the cases goes unreported/unnoticed or parent’ consent not given or the cultural and religion barriers that prevent reporting such cases. Though the patient was treated with dental fillings, the follow up of the patients is been restricted by the family members.

Conclusion

Beckwith – Wiedemann Syndrome patients usually grow and do well despite being at increased risk of childhood cancer. Hence, strict follow up, awareness of parents and cancer screening is mandatory. Families, physicians and dentists should determine screening schedule including abdominal ultrasound in every three months, blood test to measure alpha-fetoprotein in every six weeks, dental check-up in every six months and other symptomatic treatment schedule as and when required.


Read More About Lupine Publishers Journal of Pediatric Dentistry Click on the Below Link:

https://lupine-publishers-pediatric-dentistry.blogspot.com/


Thursday, 11 February 2021

Lupine Publishers | Anterior Open Bite Using Simões Network in Growing Patient: A Case Report

 Lupine Publishers | Journal of Pediatric Dentistry


Abstract

The anterior open bite is characterized by the negative vertical overhang occurring in the anterior region. It consists of a discrepancy in the vertical direction and is one of the malocclusions with greater aesthetic-functional impairment, besides dental and skeletal alterations. It has a high prevalence in the deciduous and mixed dentition and its etiology is multifactorial, highlighting the deleterious oral habits as the most prevalent. The objective of this study was to present the clinical case of a growing female patient presenting an anterior open bite associated with thumb sucking, by means of treatment with the functional orthopedic device Simões Network (SN3). During the first 12 months follow-up, we observed facial and intraoral oral changes and forward, the improvement of functional and craniofacial relationships, observed through complementary tests.

Keywords: Open Bite; dentition, mixed; orthopedics

Introduction

The balance of soft tissue growth and facial changes are important for the craniofacial development. Mineralized bone is formed through a process known as ossification by the membrane activity providing the function of remodeling and displacement. Breath, chewing, phonation and swallowing functions are prior to the regular growth development [1]. Thumb or pacifier sucking, and tongue thrusting may cause a disorder knowing as an anterior open bite. The severity of the malocclusion will be according to the magnitude, frequency and time of the habit [2]. Prolonged breastfeeding will be recommended to avoid nonnutritive sucking habits, as the sucking of fingers, pacifiers and bottle feeding [3,4]. Anterior open bite (AOB) is defined as the lack of incisal contact between anterior teeth in centric relation. AOB creates aesthetics problems, speech disorders and tongue thrusting habit [5]. This malocclusion requires early treatment due to all the etiological factors mentioned before. The stability will be achieved in a long term; thus, the pediatric dentist must be alert and minimize the problem as soon as possible in attempt to decrease the time of the treatment and to maintain the stability 5. The auto correction index is low when the correct habits are achieved [6,7]. The prevalence in the population ranges from 1,5% to 11%. Some authors also describe that 17% to 36% of those seeking orthodontic treatments feature AOB [8-11]. This malocclusion may also occurs due to a skeletal component classified open bite into dental and skeletal, associated with excessive molar height, divergent upper and lower occlusal planes, steep mandibular plane angle, increased gonial angle, short mandibular ramus, downward rotation of posterior part of the maxilla or palatal plane tipped up anteriorly, increased lower anterior facial height and decreased upper anterior facial height. According to severity, modalities of treatment are required: growth modulation; orthodontic mechanotherapy and the combination with orthognathic surgery [12-14]. Orthopedics devices is a therapy to readapt the muscular system which is very efficient in growing patients resuming the facial balance [15]. This article presents a clinical case of growing female patient, with anterior open bite treated with the functional orthopedic device Simões Network (SN3) [16].

Case Report

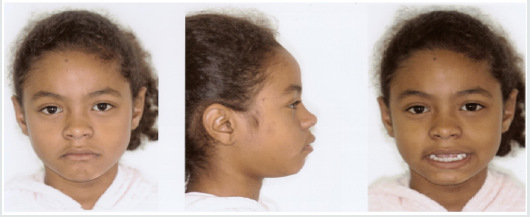
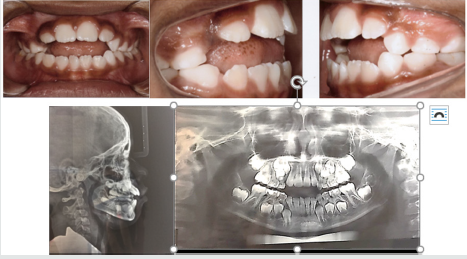
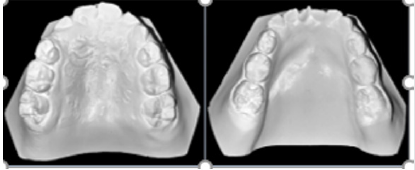
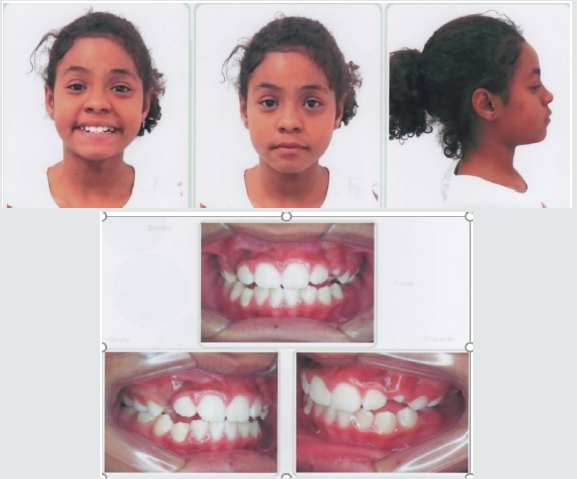
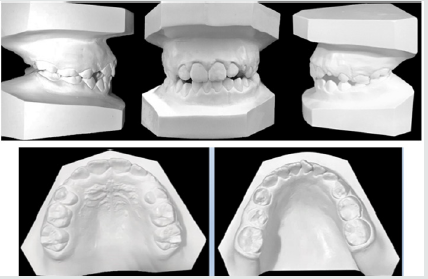
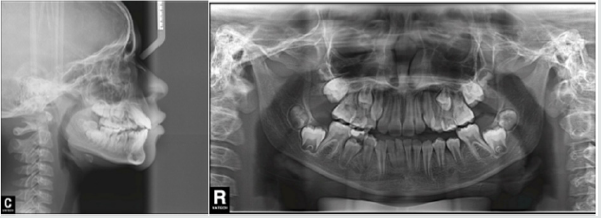
A female patient, 8 years and 4 months of age, melanoderma, came for treatment at the Postgraduate Course in Orthodontics of Brazil University (São Paulo, SP, Brazil). A facial analysis detected convex facial profile, lack of lip closure, and a decrease in nasolabial angle (Figure 1). The patient exhibited thumb sucking habit, mixed breathing, atypical swallowing and speech. shows angle class II malocclusion, 6 millimeters of an anterior open bite, mild crowding and a supernumerary Figures 2&3 tooth in the anterior lower jaw with mandibular midline deviation to the right. Cephalometric Rx shows proclined upper incisors due to the thumb sucking the objetives

Figure 1: Convex facial profile, a decrease in nasolabial angle and the upper lip covering the incisor.

Lupinepublishers-openaccess-pediatric-dentistry-journal

Figure 2: Anterior open bite, mild crowding and a supernumerary tooth in the anterior lower jaw and proclined upper incisors.

Lupinepublishers-openaccess-pediatric-dentistry-journal

Figure 3: Angle class II malocclusion, supernumerary tooth in the anterior lower jaw and an 6mm open bite.

Lupinepublishers-openaccess-pediatric-dentistry-journal

for the first phase of the treatment were to eliminate the thumb sucking, the open bite, dental deviations, provide arch expansion and the extraction of the supernumerary tooth.

Treatment Progress

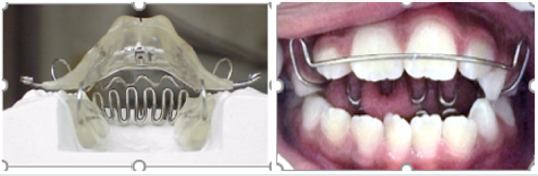
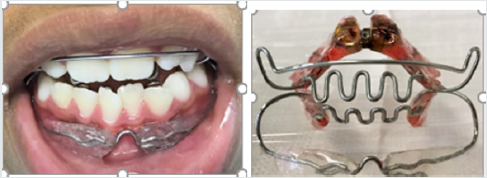
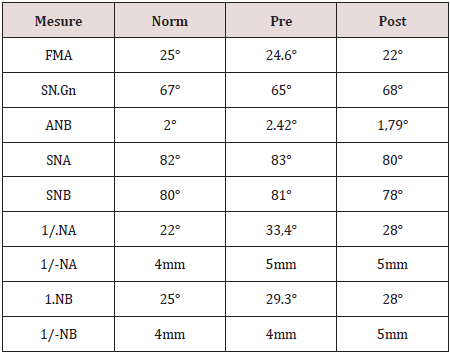
A removable appliance known by Simões Network (SN3) composed with a stainless steel bimaxillary grid (“lower winglets model”) that simulates the incisors occlusion and provides the correct tongue position [15] (Figure 4). The screw was expanded with one-quarter turn biweekly. After 3 months of the treatment beginning o, we added a lip bumper to improve lip seal (Figure 5). We recommended the use for 10 or 12 hours a day. The supernumerary extraction was performed 7 months of the treatment beginning. Figure 6 shows the final of the first stage. Figure 7 shows Angle class I malocclusion and Figure 8 shows the Cephalometric and panoramic Rx after 23 months with the orthopedic appliance. Cephalometric superimposition (Figure 9) and analysis (Table 1) indicated dentoalveolar open bite pretreatment and the correction posttreatment.

Figure 4: SN3 appliance, bimaxillary anchorage with “lower winglets model”.

Lupinepublishers-openaccess-pediatric-dentistry-journal

Figure 5: A lip bumper was added to improve lip seal.

Lupinepublishers-openaccess-pediatric-dentistry-journal

Figure 6: The correction of open bite and the improvement of the alignment.

Lupinepublishers-openaccess-pediatric-dentistry-journal

Figure 7: The arch expansion and molar Class I.

Lupinepublishers-openaccess-pediatric-dentistry-journal

Figure 8: Cephalometric and panoramic Rx after 23 months of treatment.

Lupinepublishers-openaccess-pediatric-dentistry-journal

Figure 9: Cephalometric superimposition revealed maxillary incisor retrusion and mandibular incisor in normal bite.

Lupinepublishers-openaccess-pediatric-dentistry-journal

Table 1: Summary of cephalometric measures.

Lupinepublishers-openaccess-pediatric-dentistry-journal

Discussion and Conclusion

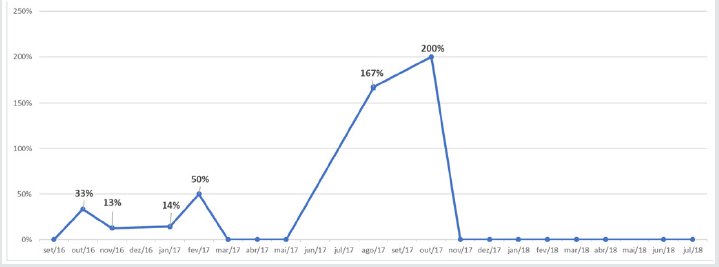
According to the authors, AOB is a challenge daily faced because and it can result speech and swallows’ problems, tongue posture and imbalance between jaw postures [17-19]. Bonna 2016 alerts that the orthodontics or orthopedic devices are fundamental but without family support the habit suppression will not be achieved [20]. The objective for the first phase of treatment were to eliminate thumb sucking, open bite and arch expansion with orthopedic appliance Simões Network SN3 and after a lip bumper was included to improve seal lip. These goals were achieved during the first stage. Graphic 1 shows best fit reduction open bite from May to November 2017. Even pubertal increments offer best time for orthopedic treatment helping determine the predictability, growth direction, patient management and total treatment time, we did not wait to treat because the disadvantages of the open bite [21]. This reported case was successfully treated with SN3 remained stable after the AOB correction. For the second phase with fixed orthodontic treatment will be necessary [22-29].

Graphic 1: Closure open bite variation during time.

Lupinepublishers-openaccess-pediatric-dentistry-journal


Friday, 29 January 2021

Lupine Publishers | The Effects of Breastfeeding on the Process of Tooth and Jaw’s Development

 Lupine Publishers | Journal of Otolaryngology

Abstract

From the nutritional point of view, it has been proven that breast milk has many benefits for the baby, and it is advisable for all mothers to give their baby milk, and if possible do not replace that with the bottle. In other words, we can say that the sucking mechanism used during bottle-feeding is markedly different from that used during breast-feeding. The Federation of Orthodontists of France announced in a report that breastfeeding not only prevents allergies and gastrointestinal infections and overweight, it also promotes the regular growth of the baby’s face. Some of the researches prove this hypothesis.

Keywords: Bottle Feeding; Breast Feeding; Sucking Mechanism; Growth of Baby Face; Allergies; Gastro Intestinal Infections; Overweight

Introduction

After birth, the baby learns how to suck on her mother’s breast. She instinctively brings forward her lower jaw and tongue; then starts sucking with full power so that all the muscles of her tongue, cheeks, lips, and jaw are involved. In all infants, since jaws are not fully developed at birth, sucking breast milk helps the jaw to grow as well as the teeth in the future [1-3]. Breast-feeding has been indicated as one of the main factors which are responsible for the correct growth and formation of dentofacial structures during the infancy [1-3]. Breastfeeding is a useful action for developing and growing teeth and jaws of infants [1-4]. The mechanism used in for the time of bottle-feeding is markedly different from that used during breast-feeding [5-7]. In the course of sucking mother’s milk, more muscles are activated to get milk than to drink milk from the bottles. During this action, the baby inserts more of the nipple into his mouth, consequently, moves the jaw up and down, and sucks the breast with all force to release the milk. To achieve this, the facial and oral muscles of the baby are involved in milking activities. This improves the shape of the jaws, and healthy teeth are expected to be in the correct eruption direction without any deviation and abnormalities [1-4].

The Main Cause of Abnormal Tooth Formation During Infancy

One of the factors leading to abnormal teeth and also leading children to orthodontic or speech therapies [8] is the abnormal orofacial muscular imbalance pattern of the tongue [9-11] known as tongue thrust. This problem is more common among children who are fed through the bottle and is often not seen among those who are breastfed. In other words, the breast-fed baby has more forceful gums and mandibles to extract the milk from the mother’s breast while a baby who is fed with a bottle, does not have to use extra jaws force because by a simple sucking a rapid flow of milk will be obtained. Of course, it should not be taken for granted that all children who use the milk bottle suffer from jaw problems, but it should be remembered that breastfeeding give better evolution to the jaws and teeth than the nourishment from the bottle.

Overview of Some Researches

The early transition from breastfeeding to bottle-feeding may contribute to inadequate mandibular development which can be a dominant and deleterious factor in the development of occolusofacial problems. In this part, we look at some research which may point out this strong hypothesis. Some studies have cited that breastfeeding is a protective factor against malocclusion: Labbok and Hendershot have suggested that increased bottlefeeding duration may contribute to the prevalence of malocclusions [12].

Viggiano et al. and Karjalainen et al. have indicated that breastfeeding can be a positive factor to prevent the development of posterior cross bite in the primary dentition [6,13]. Warren et al. reported that breastfeeding promotes normal palate development and weakens the formation of a deep and high-arched palate [14]. Several studies agree that bottle-feeding may be responsible for the development of sucking habits which may lead to some forms of malocclusion [6,14,15].

Conclusion

Breastfeeding acts on the process of sucking which are influencing the development of facial bones and muscles. Infants who are breastfed have greater facial muscle activities compare to those who are bottle-fed. In other words, breast feeders present an excellent orofacial muscle work out which helps to develop good their bony jaw structures. Moreover, breastfeeding prevents against orthodontic problems and malocclusions (for instance: overbite, posterior crossbite, tongue thrust, oral habits and etc.) that are cited in some researches.

Read More Lupine Publishers Pediatric Dentistry Journal Articles: 
https://lupine-publishers-pediatric-dentistry.blogspot.com/


Friday, 22 January 2021

Lupine Publishers | Treatment of Infected Primary Teeth using Modified Antibiotic Paste

Lupine Publishers | Journal of Pediatric Dentistry


Abstract

Objectives: Treatment of pulpectomized primary molars with chronic infection using a mixture of three antibiotics: Metronidazole, Ciprofloxacin, and Doxycycline mixed with Macrogol or Propylene Glycol (modified 3MIX-MP) as an intracanal medicament before the complete cleaning and shaping and obturation.

Study design: A 7 years old child with infected primary molar came to our clinic for treatment. A detailed medical history and drug allergy were taken. Ciprofloxacin (500mg), Metronidazole (500mg) and Doxycycline (100mg) tablets divided in the proportion of 1:3:3 (one part of Ciprofloxacin, three parts of Metronidazole, and three parts of Doxycycline) and mixed with propylene glycol to form an ointment. Biomechanical preparation was done. The modified 3MIX-MP paste placed in the pulp chamber then temporary filling. The patient was recalled after 2 weeks. The tooth was obturated and restored then a stainless-steel crown placed. Then reevaluated at 3rd, 6th, and 12th months.

Results: Excellent clinical and radiographic success when compared to conventional pulpectomy and non-instrumentational lesion sterilization tissue repair therapy.

Conclusion: Treatment of Primary molar with modified 3MIX-MP, followed by instrumentation and obturation provided excellent clinical and radiographic success when compared to non-instrumentational lesion sterilization tissue repair therapy.

Keywords: Pulp infection; Pulpectomy; Modified antibiotic paste; Primary molars; Chronic, infected pulp; Modified 3 MIX-MP; Pulpectomy; Triple antibiotic paste; Primary teeth

Introduction

The first topical antibiotic introduced to endodontics was Grossman’s polyantibiotic paste in 1951, later many topical antibiotics have been introduced with varying combinations, few of those include Septomixine forte; PBSC (Combination of Penicillin, Bacitracin, Streptomycin and Caprylate sodium), and Clindamycin. However, none of these combinations has proven to be 100% successful in eliminating all the bacterial strains from the root canal system [1-5].

Materials and Methods

A child aged 7 years old with chronic infection related to the lower left primary molar came to our clinic for treatment of the infected molar (Figure 1). Treatment was explained to the parents and written informed consent was taken from parents before start of the study. A detailed medical history and previous illness with a history of drug allergy were taken from the parents, then the mentioned primary molar was diagnosed clinically, the molar was badly decayed with signs of chronic infection such as: gingival swelling and tenderness to percussion. A radiographic examination was done and a per radicular radiolucency was found, with no excessive root resorption. Commercially available chemotherapeutic agents such as Ciprofloxacin (500mg) (Omacip, NPI Pharma, Oman), Metronidazole (500mg) (Anazol, JPI, Saudi Arabia), and Doxycycline (100mg) (Tabocine, TPMC, Tabuk) tablets were obtained [6,7], then these tablets were crushed into fine powder using sterile porcelain mortar and pestle. These powdered drugs were transferred into three separate sterile glass containers, capped tightly and stored in the refrigerator until its use. Just before use, each powdered drug was divided in the proportion of 1:3:3 (one part of Ciprofloxacin, three parts of Metronidazole, and three parts of Doxycycline) and were mixed with propylene glycol and polyethylene glycol to form an ointment. Reddy GA et al. Trairatvorakul and Detsomboonrat, Jaya et al., Cruz et al. also followed the similar protocol of preparation of 3MIX antibiotic paste [8-11].

Figure 1: Preoperative illustration.

Lupinepublishers-openaccess-pediatric-dentistry-journal

Figure 2: Postoperative illustration.

Lupinepublishers-openaccess-pediatric-dentistry-journal

Preoperative clinical and radiographical signs and symptoms were recorded. The tooth was anesthetized using 2% Xylocaine with 1:80,000 adrenalin and isolated with rubber dam. Access opening was performed using round bur, Biomechanical preparation was done using k files from size 10–25. The root canals were chemically cleaned with 1% sodium hypochlorite solution and dried with paper points. The 3MIX-MP paste placed in the pulp chamber and pressed with dampened cotton pellet and temporized with Cavit. The patient was recalled after 2 weeks for evaluation. The tooth was obturated with reinforced zinc oxide eugenol (IRM, Dentsply) using lentulo spirals. Then restored with glass ionomer restorative material (Riva self-cure, SDI) and reinforced by placing stainless steel crowns (Figure 2). Further, the treated tooth was reevaluated both clinically and radiographically at 3rd, 6th, and 12th months intervals postoperatively (Figure 3). At the time of revisits, the tooth was examined clinically for any signs of failure that includes a report of spontaneous pain, presence of swelling, sinus tract and mobility. Radiographic evaluation was done to check the radiolucency and signs of resorption. The tooth was asymptomatic without pain, swelling, sinus tract and mobility also there was no increase in furcation radiolucency or development of root resorption which is abnormal for the age of the child.

Figure 3: 12 months Follow up.

Lupinepublishers-openaccess-pediatric-dentistry-journal

Results

Excellent clinical and radiographic success when compared to conventional pulpectomy and non-instrumentational lesion sterilization tissue repair therapy.

Discussion

This study was approved by “Research Ethics Committee, Taibah University, College of Dentistry, TU CD-REC”. The concept of Non-Instrumentation Endodontic Therapy introduced by Niigata university school of dentistry; Japan has gained reputation as it proved to attain 100% sterility in the root canal system [12- 15]. They recommended a technique similar to pulpotomy where debriding only the pulp chamber of chronically infected primary teeth and placing medicament (ciprofloxacin, metronidazole, and minocycline) near the root orifice without preparing the radicular portion. Cruz et al. suggested vehicles such as macrogol and propylene glycol (3MIX–MP) and demonstrated that these vehicles will carry the medicament deep into the dentinal tubules, thus aid in effective eradication of bacteria [11]. Metronidazole (Nitroimidazole compound) due to its wide spectrum of antibacterial action against anaerobes (Ingham et al. 1975) gained importance as the 1st choice drug for triple antibiotic paste preparation [16,17]. Metronidazole binds to the DNA and disrupts its helical structure and thus leads to rapid cell death. However, metronidazole even at higher concentrations could not eradicate all the bacteria thus indicating the necessity of some additional drugs to sterilize these lesions [15]. The two other antibacterial drugs, i.e. ciprofloxacin, and minocycline, in addition to metronidazole (3MIX) were added in an effort to eliminate all bacteria [8,10,15,18]. The 2nd choice of drug ciprofloxacin is a synthetic fluoroquinolone with rapid bactericidal action. It inhibits the enzyme DNA gyrase of bacteria. It exhibits very potent activity against Gram-negative bacteria but very limited activity against Gram-positive bacteria. Most of the anaerobic bacteria are resistant to ciprofloxacin. Hence, it is often combined with metronidazole in treating mixed infections. The 3rd choice of drug was minocycline. It is a semisynthetic derivative of tetracycline, primarily bacteriostatic, inhibiting protein synthesis by binding to 30S ribosomes in susceptible organisms and exhibits broad spectrum of activity against Gram-positive and Gramnegative microorganisms [3].

In our present study we replaced Minocycline with Doxycycline due to the difficulty in obtaining Minocycline, and before using the Doxycycline as a replacement we have done further searches for previous studies to ensure that both medications have the same effect and this replacement will not affect the efficacy of the mentioned mix. The already done studies concerning the difference between both Doxycycline and Minocycline revealed that still no statistically significant differences had been demonstrated in clinical trials when comparing Minocycline with Doxycycline, and investigators had concluded that both are equally effective. And they differ in their adverse event profile [19]. Considerably fewer adverse effects have been reported for Doxycycline than Minocycline; the adverse effects for Minocycline are 5 times more common than for Doxycycline [19]. We have followed the same protocol of Reddy GA et al. of extirpation of both necrotic coronal as well as all accessible radicular pulp tissue and then complete obturation, which is reported successful clinically over 16th month follow-up [9]. Although the previous studies have demonstrated that the LSTR (Lesion Sterilization Tissue Repair) technique as one of the successful techniques for management of chronically infected primary teeth, the controversies aroused about the duration of therapeutic activity of the medicament and leaving the infected material in the radicular region. So that the present study planned where in treated tooth were revisited after 2 weeks for medicament removal and obturation.

Conclusion

All the primary teeth with chronic infection which were treated using modified 3MIX-MP, followed by the instrumentation and obturation provided excellent clinical and radiographic success when compared to conventional pulpectomy and noninstrumentational lesion sterilization tissue repair therapy.

Read More Lupine Publishers Pediatric Dentistry Journal Articles: 
https://lupine-publishers-pediatric-dentistry.blogspot.com/

Friday, 15 January 2021

Lupine Publishers | Varied clinical and Oral Presentation of Beckwith – Wiedemann Syndrome - Report of a Case from Saudi Arabia

 Lupine Publishers | Journal of Pediatric Dentistry


Abstract

Beckwith – Wiedemann syndrome is congenital, genetic and epigenetic pathologies with low prevalence and diverse clinical presentations. It is characterized by triad of omphalocele, macroglossia and gigantism. This syndrome has been widely studied with a current emphasis on improvement of prenatal diagnostic techniques and a multidisciplinary approach towards treatment. We report a case of BWS from Saudi Arabia, with unique presentations and misleading history which delayed diagnosis, due to cultural and religion constraints.

Keywords:Congenital; Epigenetic; Genetic; Prenatal

Introduction

Genetic and epigenetic changes or a human genomic imprinting disorder is characterized by phenotypic variability which might shows its occurrence either as sporadic or inherited. The pathology presents wide range of effect on psychological and social wellbeing of patients and families. One such congenital, multigenic, multisystem human genomic imprinting disorder with complex molecular etiology and variable complex phenotype is Beckwith – Wiedemann Syndrome (BWS). Beckwith-Wiedemann Syndrome is most common overgrowth syndrome described by Beckwith in 1963 and Wiedemann in 1964 with similar findings. It is rare congenital deformity with low prevalence but at same time have high prevalence within genetic abnormalities of overgrowth [1]. The presentation of triad features of omphalocele (exomphalos), macroglossia and gigantism was described earlier as EMG syndrome which now is referred as Beckwith – Widemann Syndrome. The incidence of BWS reported is approximately 1:13700 births and the major cause is thought till date is genetic and epigenetic defects within the chromosome 11p15.5 regions [2].

BWS presents wide array of clinical manifestations such as congenital abdominal wall defects as hernia (exomphalos), gigantism, macroglossia, nevus flammeus, ear pits/hearing loss, midface hypoplasia, cardiac anomalies, hemihypertrophy, genitourinary anomalies and musculoskeletal abnormalities. To standardize the diagnostic criteria various attempts have been made to classify the major and minor criteria. Elliot et al described the diagnosis of BWS with the presence of either three major features (abdominal wall defect, macroglossia, gigantism) or two major and three minor features (ear pits, nevus flammeus, hemi hyperplasia, nephromegaly, neonatal hypoglycemia) [3]. In spite of diverse clinical presentations of BWS, most of the cases do not show characteristic features at birth but develop later in life. Also, children with BWS have significantly increased risk of cancer during early childhood which need strict follow up and monitoring. Here, we present a case of BWS with unique dental and medical presentation and its differential diagnosis with literature review.

Case Report

A 5-year-old female patient, accompanied by her mother, presented to the dental unit with complaint of decay tooth in upper front region of mouth. Extra oral examination revealed dysmorphic features, coarse facies and developmental problems (Figure 1). Intra oral examination of hard tissue showed high arched palate, decayed teeth in relation to 51, 52, 55, 61, 62, 74, 75, 84,85. Oral soft tissue examination revealed macroglossia, enlargement of fungiform papillae and mild loss of filiform papillae (Figure 2). Speech and feeding difficulty were noticed due to macroglossia. History revealed she is the youngest 7th child born out of consanguineous marriage in 30th week by cesarian section. She has a chronic history of constipation for 9 months of age. She passes hard stool once in every 8 to 10 days, by spending long time in washroom. It is associated with decrease in appetite and abdominal pain. She was given Movicol (half the adult dose) twice a day for constipation without any medical prescription. She was also tried with lactulose, glycerin suppository and mineral oil. Under medical supervision fleet enema and contrast enema were performed to relieve constipation and to rule out Hirschsprung disease.

Figure 1: Photograph showing dysmorphic features and hypertelorism.

Lupinepublishers-openaccess-pediatric-dentistry-journal

Figure 2: Macroglossia with enlarged fungiform papillae and loss of filiform papillae.

Lupinepublishers-openaccess-pediatric-dentistry-journal

Other medical findings noticed omphalocele, ear pits, large child at 90th centiles, large rounded eyes with hypertelorism, abdominal soft lax, enlargement of kidney, distention of left renal pelvis with significantly distended urinary bladder, abnormal anatomy of the colon located in left abdomen and partial colonic non – rotation with no evidence of obstruction (Figure 3). Based on the clinical and past medical history a diagnosis of Beckwith – Wiedemann Syndrome (BWS) was made. Series of laboratory investigation were reviewed which presented negative urine examination, alpha – fetoprotein, karyotype, microarray and methylation analysis for BMS. Patient was advised for gene analysis and targeting testing for parents. The gene analysis of CDKN1C gene showed heterozygous alteration consistent with BWS but targeting gene tests were refused by parents. Panoramic radiograph was advised considering the patient chief complaint, which revealed multiple developing permanent tooth buds, protrusion of anterior teeth, open bite and increase in mandibular dimension (Figure 4). Under preventive measures the patient was treated for the decayed teeth and is under follow up from past 6 months.

Figure 3: Photograph showing abdominal wall defect with surgical scar.

Lupinepublishers-openaccess-pediatric-dentistry-journal

Figure 4: Panaromic radiograph showing multiple developing permanent tooth buds, open bite and increased mandibular dimension.

Lupinepublishers-openaccess-pediatric-dentistry-journal

Discussion

Diagnostic criteria for BWS is still a matter of research due to its varied clinical presentations and overlapping features with other various conditions. The presence of major and minor findings is generally helpful in establishing the clinical diagnosis (Table 1). The oral findings as mentioned in the literature and observed in our case has been tabulated in Table 2 [4,5]. The incidence of BWS is difficult to assess in Saudi Arabia, as most of the cases goes undiagnosed and unnoticed. Also attributed to its diverse clinical presentation and difficulty in diagnosing. In the present case, features of macroglossia, macrosomia, omphalocele, abdominal wall defect (treated immediately after birth and surgical scar observed clinically), Renal involvement, ear crease, high arched palate, open bite and increased mandibular dimension, leads to the diagnosis of BWS. Various molecular mechanisms and alterations have been involved in BWS such as abnormal methylation of H19DMR, loss of imprinting of IGF2, chromosomal rearrangements, loss of imprinting of LIT1, uniparental disomy of 11p15 and CDKN1C mutations [2]. The full gene analysis of CDKN1C gene profile were suggestive of BWS in our case and the alteration is thought to be located in the allele inherited from the mother. Parental testing was advised which was refused by the parents. There are various endocrine and overgrowth syndromes that was considered in the differential diagnosis. These included Simpson-Golabi-Behmel syndrome (mutation in X-linked gene, GPC3), Perlman syndrome (Increased risk of neonatal mortality), Costello syndrome (missense mutation in HRAS), Sotos syndrome (Mutation in NSD1) and Mucopolysaccharidosis type IV (lysosomal storage disorder) [6]. Oral findings like macroglossia of BWS needs differentiation from other lesions like lymphangioma, idiopathic muscular hypertrophy, hemangioma, rabdomyomas, amyloidosis, cretinism and acromegaly.

Table 1: Presenting major and minor features of BWS.

lupinepublishers-openaccess-pediatric-dentistry-journal

Table 2: Oral findings of BWS.

lupinepublishers-openaccess-pediatric-dentistry-journal

The overall risk of BWS for tumor development/malignancies is estimated to range from 4 – 21%. The tumors reported with BWS are mainly embryonal tumors such as Wilms tumor, hepatoblastoma, rabdomyosarcoma, adrenocortical carcinoma and neuroblastoma [7]. The prenatal diagnosis with current technology is increasing representing an important tool to determine some features of BWS before birth. In our case, parents were highly orthodox and refuse to share the detailed prenatal and ultrasonic reports. Few misguided information’s were given by mother which was later clarified with the reports from the subsequent medical hospitals. Patient’s parents were advised for periodic follow up with genetic counselling and the possibility of surgical interventions in the medical units, but they refused to follow and changed the hospitals every time. Hence, an effort was put forward to retrieve the information’s related to the patient while giving her the primary treatment for which she reported to our dental unit. This suggest the need of awareness required in the country like Saudi Arabia, where most of the cases goes unreported/unnoticed or parent’ consent not given or the cultural and religion barriers that prevent reporting such cases. Though the patient was treated with dental fillings, the follow up of the patients is been restricted by the family members.

Conclusion

Beckwith – Wiedemann Syndrome patients usually grow and do well despite being at increased risk of childhood cancer. Hence, strict follow up, awareness of parents and cancer screening is mandatory. Families, physicians and dentists should determine screening schedule including abdominal ultrasound in every three months, blood test to measure alpha-fetoprotein in every six weeks, dental check-up in every six months and other symptomatic treatment schedule as and when required.

Read More Lupine Publishers Pediatric Dentistry Journal Articles:
https://lupine-publishers-pediatric-dentistry.blogspot.com/

Friday, 8 January 2021

Lupine Publishers | Pediatric Dentistry Condition- A Mini Review

 Lupine Publishers | Journal of Pediatric Dentistry


Abstract

Tooth decay is the most common chronic childhood disease and the World Health Organization has identified it as a worldwide problem with 60-90% prevalence among school-age children. Dental caries is a topical contagious infectious disease that affects people of all ages and in any area of the world. Oral hygiene is a part of public health and oral and dental diseases affect different aspects of quality of life. DMFT is one of the indicators that the World Health Organization has introduced to determine the severity and prevalence of caries. One of the goals of the World Health Organization is to keep the DMFT index of students at less than 2. Different factors are effective in occurrence of dental and interdental caries that we discuss about them in this mini review.

Keywords: Decay Missing Filled Index, Dental Caries, Oral Hygiene, Tooth Decay

Abbreviations: WHO: World Health Organization; DMFT: decay-missing-filled index; BSS: Basic Screening Survey

Introduction

Tooth decay is the most common chronic childhood disease and the World Health Organization [WHO] has identified it as a worldwide problem with 60-90% prevalence among school-age children [1]. According to statistics in European countries, 6.1% of children aged 6-12 have at least one decayed or missed tooth, and due to the prevalence of tooth decay in all social classes, this disease can impose heavy costs on society [2]. Also, according to the statistics in Iran, decay-missing-filled index [DMFT] was 0.2% among 6 to 9-year-old children and 0.9% to 1.5% among 12-yearold children. Also, DMFT was 1.7% in 3 to 6-year old children and 3.3 to 4.8% in 9-year old children [3]. Four important factors: host, germs of the oral environment, food and time, has a role in tooth decay, without each of which, tooth decay will not occur [4]. Therefore, oral hygiene is very important in preventing it. Prevalence of dental caries in 6 to 12-year old children is one of the most important health problems. This can directly and indirectly impair the health of children and teenagers, and this problem is common among low-income groups and groups that do not comply with oral hygiene standards, such as not using toothbrushes and floss, dental caries is much more severe and acute [5].

Dental Caries

Dental caries is a topical contagious infectious disease that affects people of all ages and in any area of the world. Oral hygiene is a part of public health and oral and dental diseases affect different aspects of quality of life [6,7]. DMFT is one of the indicators that the World Health Organization has introduced to determine the severity and prevalence of caries. Nowadays, general dental health programs are usually only concerned with determining the prevalence of dental caries. Therefore, to measure the prevalence of dental caries and to determine oral health status in the society, especially in teenagers, appropriate indicators have been introduced by reputable authorities such as the Association of State and Territorial Dental Directors [2011]. This indicator is called Basic Screening Survey. The main purpose of using this indicator is to provide a framework for obtaining cheap and easy oral health information. On the basis of this indicator, people are classified into two parts, and it is ultimately determined whether or not they have caries [8,9].

Dental caries in Iranian students

One of the goals of the World Health Organization is to keep the DMFT index of students at less than 2. There are many studies on the calculation of DMFT in Iran, including Hamisi et al. which studied 323 students in Qazvin and showed that the prevalence of non-caries was 14.3% and their DMFT was 12.1%. [10]. Also, in a study on 12-year-old children in Tehran and Isfahan, DMFT was 11.2, which was the highest rate of caries [11]. In another study, the rate of DMFT in children in Isfahan was reported 3.41, and the conclusion of this study was that it showed a high proportion of DMFT in decay [12]. A study in Sirjan [a city in Kerman province] showed that the prevalence of non-caries state in 12-year-old students was 34.1%, which means that about 60% of 12-yearold students in this city due to various reasons, particularly not using toothbrush and floss, had dental and interdental decay [13]. Also, in the U.S Department of Health and Human Services in New Hampshire, a large evaluation of oral health status among public school students was done using the BSS index and it showed that approximately 2.3% of students had dental caries [14].

Are There Any Differences Between Girls or Boys in Caries Status?

The results of some studies show that there is no significant relationship between the prevalence of caries in male and female students. Among these studies, we can mention Nabipour et al., Who did not report a significant difference in caries status between male and female students [15]. However, in some studies, such as the study by Boroumand et al., Caries in 3-6-year-old boys was less than that of girls [16]. However, in some studies, such as the study by Boroumand et al., Caries in 3-6-year-old boys was less than that of girls [16]. Also, Loyola-Pontigo et al. and Rosado-Casanova et al. reported a higher incidence of caries in girls than boys [17,18].

Some Other Effective Factors of Children’s Caries Status

Another factor affecting dental and interdental caries is the level of parents’ education. In a study by Campus et.al, there was a significant relationship between parents’ education and lower incidence of caries in children [19]. Ismail and Sohn also stated in their study that children whose parents had a college education had significantly lower dental caries than children whose parents had lower educational level [20]. Also, the differences in socioeconomic status of families can lead to a different status of caries in children, as Primosch in a study in this regard observed a changing status of caries in families with different structures and concluded that this difference may be the result of the different socio-economic status of families, which may affect children’s dietary habits as well as hygiene [21].

Acknowledgement

The authors thank Farzanegan Hazrat Zeinab High School of Rey city and student research center of Basirat especially Dr. Salmani for their supports.

Read More Lupine Publishers Pediatric Dentistry Journal Articles:
https://lupine-publishers-pediatric-dentistry.blogspot.com/

Thursday, 7 January 2021

Lupine Publishers | Mouth Guards: Guardians of the Dontium

  Lupine Publishers | Journal of Pediatric Dentistry


Abstract

Children and teens are more prone to injuries while playing, with most of the impact taken by the face especially the jaws and the teeth. The most significant factor in preventing sports-related or recreational  orofacial injuries is wearing basic protective devices such as properly fitting helmets, face masks, or mouth guards. A mouth guard, custom-fitted by your dentist and worn every time you play or train, will protect against dental injury. Mouth guards are available in 3 different variants which are stock, self-adapting, custom-made mouth guards. The benefits far exceed the expenditure when considering the fees and discomfort associated with a traumatic dental injury

Keywords: Mouth Guard; Orofacial Structures; Teeth; Custom; Sports; Injuries

Introduction

Physical activity forms a very important part of life. There have been constant reports of sedentary lifestyle being associated with disease processes and over the time a lot of importance has been emphasized on physical activities be it the gym or the sports. Children and teens are more prone to injuries while playing, with most of the impact taken by the face especially the jaws and the teeth. Hence, it becomes very important to wear protective gear as these injuries might not only cause temporary impairment but also cause hindrance to the growth and development of the facial structures and also may lead to an unaesthetic appearance of the child at the later stage. The injuries occurring in sports can range from a simple ball-hit to a serious impairment of the head, face or the mouth. It is very important to wear protective gear when you are actively participating in any recreational outdoor events and also in some instances in the indoor activities with the risk of injuries. The most significant factor in preventing sports-related or recreational orofacial injuries is wearing basic protective devices such as properly fitting helmets, face masks, or mouth guards. The use of the mouth guard forms the basic minimal requirement for protecting your mouth, which should form an essential piece of the athletic equipment that the athlete should use as the standard gear equipment from a very early age.

A mouth guard, custom-fitted by your dentist and worn every time you play or train, will protect against dental injury. Well-fitted mouth guards prevent violent contact between the maxillary and mandibular dentition, which can result in soft tissue lacerations, tooth avulsions, tooth or bone fractures, endodontic injuries, and concussions [1]. This being said it has been found that injury to teeth are 60 times more likely when the athlete is not wearing the mouth guard than when he/she is wearing it. Statistically, sporting activities contribute to nearly one-third of all dental injuries [2-4]. Mouth guards help buffer an impact or blow that otherwise could cause broken teeth, jaw injuries or cuts to the lip, tongue or face. Mouth guards also may reduce the rate and severity of concussions Consequently, the dentist plays an important role in informing patients, athletes and their parents, and coaches of the importance of prevention, diagnosis, and treatment of orofacial injuries in sports and recreational activities [1].

A mouth guard should be able to fulfill the following basic requirements:

a) Encompass all maxillary teeth extending up to the distal surfaces of the second molars in class I and class II patients [4-7].

b) Encompass all mandibular teeth extending up to the distal surfaces of the second molar on class III patients [4-7].

c) Mouth guard may be abridged to cover until the distal surfaces of the first molars, in case it is known to trigger the gag reflex of the patient [4].

d) The labial flange should range to within 2mm of the sulcus [5].

e) The palatal flange should range around 2mm above the gingival margin [5].

f) The margins of the labial flange should be rounded.

g) The margins of the palatal edge should be tapered [5].

h) Be easy to clean [8,9].

i) Not impede with breathing or speech activity [4].

j) Be fabricated from a material approved by the U.S. Food and Drug Administration that can reduce the impact force to teeth, surrounding soft tissues, and bone [4,9].

k) Be comfortable and retentive and fit properly [9].

Mouth guards are available in different variants

A. Stock

B. Self-adapting

C. Custom-made

A. Stock

These are readily available over the counter in different sizes, made from polyurethane, a copolymer of vinyl acetate, or ethylene. As they are produced in bulk and are of standard sizes, they remain inexpensive, however they offer a low level of protection with little retention and is not so easily accepted by the athlete. The need to hold the mouth guard in place by clenching his or her teeth together is another disadvantage.

B. Self-Adapting

Also known as the “boil-and-bite” type mouth guard. It is readily available over the counter and made from ethylene-vinyl acetate (EVA). Herein, it is heated in hot water and then placed in the mouth to be adapted to the teeth by biting down. It is relatively inexpensive and can be replaced frequently in athletes with a mixed dentition or by individuals who are experiencing rapid growth. It has the property of re-adaptability. However, it is often bulky and does not retain its shape over time.

C. Custom-Made

The custom-made mouth guard is fabricated in a dental laboratory on a cast taken from an impression made by a dentist. The custom-made mouth guard offers the best fit and the most protection of any of the protective devices [4,5,9]. It is usually made of a thermoplastic material that is heated and adapted to the cast under pressure or with a vacuum form machine. Due to the laborious work involved in the fabrication of this type of appliance, it is expensive but retentive. The American College of Prosthodontists (ACP) recommends the use of custom mouth guards for all contact sports and for any recreational activities that may hypothetically end in orofacial injuries. Accurate maxillary and mandibular alginate impressions in centric occlusion registration recorded by a qualified dentist at approximately 5-mm opening anteriorly shall be used for fabrication of the custom trays as recommended by the ACP.4,5 The standard thickness is 4-mm, however 5- or 6-mm thickness is recommended as it will be able to protect the athlete better in case of extreme sports [4].

Mouth guards can be either single-layered or multi-layered. Currently, the most commonly used materials in the construction of custom mouth guards are EVA copolymer, soft acrylic resin, polyvinyl chloride, polyvinyl acetate-polyethylene (pEVA), and elastomers [1,8,9]. Many different designs of multi-layered materials are available. The most frequently used is a double layer made of similar materials. Dual laminated mouth guards possess an outer hard shell of styrolbutadiene co-polymerisate, and a soft inner layer of ethylene copolymer and vinyl acetate. This design of a more rigid outer material with an inner softer material will reduce the impact force transferred to the teeth due to the shock-absorbing capability of the softer layer [4,5]. The critical areas in terms of energy absorption and transmitted forces are the incisal edges of the anterior teeth and the attached (marginal) gingiva. Therefore, an optimal thickness of the device is achieved by the application of vacuum forming pressure-lamination technique of two layers of a thermoplastic sheet (EVA copolymer) and if necessary, by placing two layers of protective air-cells against the critical areas. An acrylic-resin-based elastomer may be processed over the thermoplastic sheet to improve protection for the athlete [4]. Custom-made mouth guards have proved to be the most effective means of prevention of injuries to the orofacial structures [1,4,5]. They are superior in quality, comfort, retention, and prevention of injuries when compared to stock or self-adapting devices. Although custom-made mouth guards are the most expensive type of protective oral device, they are the most highly recommended.

Conclusion

The benefits far exceed the expenditure when considering the fees and discomfort associated with a traumatic dental injury. Further, it becomes the duty of the dentist to create awareness among the athletes and make it a habit for them to wear mouth guard as a part of their equipment for sports.

Read More Lupine Publishers Pediatric Dentistry Journal Articles:
https://lupine-publishers-pediatric-dentistry.blogspot.com/

Saturday, 19 December 2020

Lupine Publishers | Comparison of the Efficacy of Plaque Removal of Listerine Smart Rinse Kids and Vi– One Junior Fluoridated Mouthwash in Children Aged 6 To 10 Years

 Lupine Publishers | Journal of Pediatric Dentistry


Abstract

Objectives: In this study, a comparative study was done on the effects of Vi-One and Listerine fluoridated mouthwashes on the reduction of dental plaque in pediatric patients between 7-11 years of age in dental clinics of Sepideh and apple in Shiraz, Iran. Listerine Smart Rinse Kids is a product of the United States and Vi-One Junior mouth wash is the domestic production of the country at Rozhin Corporation. This research was conducted by Mohammad Karimi and Hassan Dehghan in 2018-2019.

Material and Methods: In this study, 100 individuals were selected and divided into two groups of 50. During the study, no other method of controlling the plaque was used. In this method, the first group first used Vi-One mouthwash for 10 days and after two weeks of rest and minimizing dental plaque, they used Listerine for 10 days. While the second group used Listerine first, then they applied Vi- One in the same way. The results of this review were then evaluated.

Results: The mean of plaque index in total mouth and in the posterior teeth area with the use of Listerine Smart Rinse Kids was lower than that of Vi-One Junior mouth rinse. In another words, Listerine had a better effect on plaque removal than the Vi-One mouthwash in the posterior mandibular region.

Conclusion: The results show that although Listerine mouthwash had a better effect on dental plaque removal, none of the two mouthwashes had a significant difference in effects on maxillary and mandibular jaws.

Keywords: Dental Plaque; Vi- One, Listerine, Fluoridated Mouthwash; Periodontal Diseases; Plaque Index

Introduction

Currently, dental caries and gingivitis are common oral and dental diseases in this country. One element that can prevent tooth decay is Fluoride. In the oral health program of the country, fluoride mouth wash 2% was used to prevent dental caries in elementary school students all over the country [1]. In the other hand, dental plaque is an important factor in the formation of dental caries and periodontal diseases. Leo and his colleagues have identified dental plaque as the main cause of gingivitis [2]. With the use of mouthwashes, one can control the dental plaque, chemically [3,4]. In fact, mechanical plaque removal is one of the most common and effective methods for preventing caries and inflammation of the gum [5]. Fluoride mouthwash usage is contraindicated in children younger than six years of age due to the risk of swallowing and causing systemic toxicity and fluorosis [6-8]. Symptoms of acute oral fluoride toxicity in children include severe nausea, vomiting, hyper salivation, abdominal pain, and diarrhea [9]. In severe or fatal cases, these symptoms can be followed by convulsions, cardiac arrhythmias, and coma [10- 12]. Laboratory and animal data have shown that prevention the accumulation of plaque and consequently, reduction in dental plaque can be achieved when fluorides is applied topically which inhibits the bacterial multiplication [13]. The fluoride from mouth rinse is retained in dental plaque and saliva to help prevent dental caries [14]. In one review, the average caries reduction in nonfluoridated communities attributable to fluoride mouth rinse was 31% [15]. Another study in Sweden reported that the use of fluoride mouthwash along with brushing has a significant effect in decreasing of dental caries [16]. Listerine Smart Rinse Kids has been used for the purpose of this study. This product is an alcoholfree mouthwash. The ingredients include Sodium fluoride 0.02% (0.01% w/v fluoride ion), Water, Sorbitol, flavor, phosphoric acid, Sucralose, Cetylpyridinium chloride, disodium phosphate, sodium saccharin, menthol, blue 1 and green 3 [17]. One study reported that use of this mouthwash can strengthen teeth 99% better than brushing alone [18]. Another source indicated that it gives 12- hour cavity protection [19]. Vi-one Junior Mouthwash is specially designed for children. This mouth rinse contains Sodium fluoride 0.05%, Cetylpyridinium chloride 0.05% and Disodium phosphate agents. The respective flavors contain sugar-free and harmless sweetener. This brand also is an alcohol-free product [20]. The purpose of this study was to compare the efficacy of two types of mouthwashes, one the domestic mouthwash (Vi-One Junior) and the other, the brand name Listerine Smart Rinse kids fluoridated mouthwash in the removal of the dental plaque.

Material and Methods

This study was a cross-over clinical trial. The eligibilities for entering in our study were as follow:

a) Children having at least 20 teeth with no large restorative area.

b) No history of periodontal Diseases.

c) Not having any Prosthodontic or Orthodontic appliances.

The condition for withdrawal from the study, if there was any sign of reactions to any of these mouth rinses. There was no obligation to have any food regimen.

The study population consisted of 100 patients who were in a 50-member group. Before taking oral mouthwash, plaque index was minimized, and all subjects underwent tooth scaling at the beginning and, if necessary, teeth polishing were done before taking mouthwash. Oral hygiene was assessed via a plaque index. First, in both groups, the Silness-Löe plaque index was recorded. It is an Index for evaluating the thickness of the plaque in the gingival region, which measures the thickness of plaque on all surfaces (M, B, D, and L) [21].

Coding for the plaque index was carried out according to the criteria [22]:

a) Code 0: No plaque

b) Code 1: A film of plaque is adhering to the free gingival margin and adjacent area of the tooth. The plaque may be seen in situ only after application of disclosing solution or by using the probe on the tooth surface.

c) Code 2: Moderate accumulation of soft deposits can be seen with the naked eye within the gingival pocket, the tooth, or gingival margin.

d) Code 3: Abundance of soft matter can be seen within the gingival pocket and/or on the tooth, and gingival margin.

In this index, each tooth is divided into four surface area but in our purposes in the present study, we modified the surfaces area from 4 to 6; thus, we have three surfaces in the buccal area (Mesiobuccal, Midbuccal, and Distobuccal) and three surfaces in the lingual area (Mesiolingual, Midlingual and Distolingual). The first group used Vi-One & Listerine mouthwash (kids mouthwash), for 10 days in the following way. Needless to say, this process was supervised by parents at home. The kids have to gargle 5 cc ’s of Vi-One mouthwash 2 times per day for 30 seconds, and during this period of time, no other plaque control methods and tooth brushing should be used. At the end of the period of 10 days, the plaque index was recorded again. Then, the subjects were given a week to rest and stop using the mouthwash while they had permission to start brushing like before. Again, the plaque index was minimized for patients with polishing the teeth, and they used Listerine mouthwash for 10 days. In the same way, 5 cc ‘s of the mouthwash twice daily was used for 30 seconds, and at the end of the one-week period, the plaque was recorded. For the second group, in the first 10 days, mouthwash. Listerine was prescribed and in the second 10 days, the Vi-One mouthwash was applied. All procedures were performed according to the above pattern.

Results

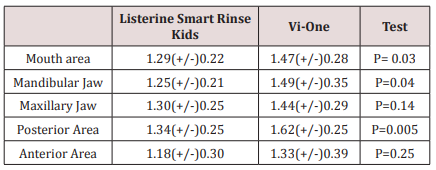
Paired T-test was used for statistical analysis of the findings. The findings showed when Listerine Smart Rinse Kids was used; the mean of plaque index in all area of the mouth (especially in the mandibular jaw and the posterior region) was significantly less than the time Vi-One was applied. However, there was no significant efficacy difference between the use of both types of mouthwash in the upper jaw and the anterior region.

There was no significant difference between the mean plaque index in Vi-One mouthwash between upper and lower jaw, and there was no significant difference between the maxillary and lower jaw in the case of Listerine Smart Rinse Kids either. The presence of this indicator in both types of mouthwash in the anterior region was significantly less than the posterior region. The mean and standard deviation of the plaque index in both groups, as well as in different regions of the mouth, are listed in Table 1.

Table 1: The amount of dental plaque in terms of area and type of Mouthwash.

lupinepublishers-openaccess-journal-pediatric-dentistry

Discussion

In general, the anti-plaque properties of mouthwashes are completed through bactericidal and bacteriostatic effects, separation of microorganisms from dental surfaces, loosening of joints to these surfaces or lowering of the surface tension of the tooth [2,21,23]. Some mouthwashes can be useful for preventing tooth decay or periodontitis [6,24]. Furthermore, mouthwashes are recommended for children and adolescents with orthodontic appliances or adults who need deep cleansing (such as curettage) [6]. These types of mouthwashes were generally used before and after surgery (especially Chlorhexidine) and have a very positive effect on the treatment of gum and ulcerative inflammation [6]. Use of this type of mouthwash should not last longer than 2 to 3 weeks due to some side effects such as staining the teeth and soft tissue staining, increased calculus deposition, unpleasant taste, burning sensation, and mucosal irritation [6]. It’s time to use this mouthwash after brushing and before bedtime, and it’s best not to eat anything after half an hour after use. Fluoride-containing mouthwashes are another type of mouth rinse that has a fairly large use. These mouthwashes have a significant effect on teeth strengthening. Fluoride in the mouthwash cause bonding with enamel and dentin, and with bonding with calcium and phosphorus, they form Fluorapatite, which is more resistant to caries than Hydroxyapatite. Fluorides also accelerate the mineralization, repair the decayed teeth surfaces, and help to increase the reverse processing of damaged tooth surface area [25,26]. Fluoride also reduces the effect of oral bacteria on teeth. It is done by interfering with the function and formation of the microorganisms. The best fluoride mouthwash protects the teeth against the acids which are produced by dental plaques. “Neglecting the oral hygiene of children leads to the accumulation of plaque and as a consequent the formation of dental calculus which will have a devastating effect on the both child’s gums and teeth” [27].

In one study, the statics showed an alcohol-free mouthwash containing a combination of 0.075% CPC and 0.05% Na F produces statistically significant reductions in dental plaque and gingivitis after three and six months compared to baseline [28]. In another research, Jessica E. Koopman, et al argued that the oral microbial community displayed remarkable resilience towards the disturbances it was presented with. The effects of the fluoride mouthwash on the microbial composition were trivial [29]. On the other side, in another study, the research showed that all four fluoride mouth rinses were effective in decreasing the plaque levels of S. Mutans [30]. In this study, we investigated the effect of two mouthwashes of Listerine Smart Rinse Kids and Vi-One in which Vi-One mouthwash in the posterior region was less efficient than the Listerine mouthwash, and the interesting point that most kids mentioned the taste of Listerine was more acceptable. Given that the contents of sodium fluoride were equal in both mouthwashes, due to the fact that Listerine mouthwash was more acceptable than the mouthwash, it could be related to the other materials present in this product which can be a part of the manufacturer’s secrets. This difference in taste can be a factor in the effect of improving Listerine’s efficacy in the posterior regions.

Conclusion

Listerine Smart Rinse Kids had a better effect on plaque removal than the Vi-One mouthwash in the posterior mandibular region. Both types of mouthwash had a better effect on the anterior region than the posterior region, but none of the two mouth rinses had a different effect on the maxillary and lower jaw. Although many popular types of mouthwash may help to control dental plaque and gingivitis, they should only be used as an adjunct to other oral hygiene measures such as brushing and flossing. Fluoride mouthwashes should be encouraged in children above the age of 6 with a high risk of caries.

Read More Lupine Publishers Pediatric Dentistry Journal Articles:
https://lupine-publishers-pediatric-dentistry.blogspot.com/