Showing posts with label Journal of Dentistry. Show all posts

Wednesday, 2 August 2023

Lupine Publishers | Signs of Tooth Eruption in Infants

 Lupine Publishers | Journal of Dentistry and Oral Health Care


Abstract

Teething is one of the challenges of medical science in Infancy period. Many studies show that teeth eruptions might have a lot of symptoms, including bad mood, skin rashes on the cheeks and around the mouth, increasing saliva secretion, swollen gums, Sucking a finger and etc. These signs and symptoms are mild in some infants, and in others may be severe; it is difficult for parents to tolerate these conditions. The peak of the severity of teething-related symptoms is when the dental buds have grown sufficiently in the gum and try to exit from the swollen gingiva.

Keywords: Teething; Saliva Secretion; Bad Mood; Skin Rash; Swollen Gum; Dental Buds

Introduction

As important as it is, tooth eruption is a matter of difficulty for both parents and children. Note that maintaining the health of teeth and gums in the child is the basis of the health of his teeth and gums for whole life. Teeth eruption is one of the most important stages of the growth, and through this stage, the baby will be able to have chewable foods. Commonly, there is a timetable for each primary tooth to erupt in the mouth. Signs of infant’s teeth eruption include disturbances in sleep and night-time wakening, mouth-watering, redness of cheeks, chewing fingers and objects, swollen gums, child malaise, bad temper, and the appearance of tooth buds [1-3]. In this article, we refer to any of these cases.

Schedule the Growth of Different Teeth in the Baby

Generally, new teeth grow in pairs. First, we see the eruption of the two lower primary central incisors teeth, and about a month later, the two upper primary central incisors teeth would erupt. Of course, in some cases, the four lower primary anterior teeth might erupt at first, and then we see the eruption of the upper primary anterior teeth or vice versa. In general, the eruptions of the primary teeth are scheduled to be as follows: [4]

a) At 6 months of age: lower primary central incisors teeth

b) At 8 months of age: upper primary central incisors teeth

c) At 10 months of age: upper and lower primary lateral teeth

d) At 14 months of age: first primary molars teeth

e) At 18 months of age: primary canines’ teeth

f) At age 2: second primary molars.

Signs and Symptoms

Given that the primary teeth are much smaller when they come out of the gum, and the process of tooth eruption is different in children, the symptoms that can usually be expected are:

a) Distracted Dreams: In some children, teething might be a painful process that can awake the baby at night. Therefore, if the baby suddenly wakes up at night, it may be due to her teeth. At this time, the best thing that mothers can do is taking her to the cradle and calm down.

b) Excessive Mouthwatering: Increasing saliva secretion can be one of the symptoms of the eruption of a new tooth. This is, of course, one of the natural stages of the baby’s teeth growth, so too much water in the mouth is not always a sign of baby’s teething. There is no way to detect the association between excessive saliva secretion and the eruption of new teeth. In a baby who is teething, his chin is often wet. Excessive saliva can cause injury and irritation of the baby’s face, so mothers should dry the baby’s face and mouth with a soft, delicate cloth. To protect the skin of the baby’s face, they can consult with their physician.

c) Swollen Gums: In some cases, before germinating of the tooth, the growth site in the gingiva of the infant becomes red, swollen and bruised. Sometimes, the rise of a tooth below the gum causes a bulge so that if parents can persuade her child to open the mouth enough, they can see the whitish shadow of the tooth under the swollen gingiva.

d) Chewing Things: Children like to take everything in their mouths, but if the baby too much does that, she may be teething. The pressure that unerupted teeth from below have on the gums, make the pain to be relieved by applying pressure from the opposite direction. Hence, most infants who are teething are willing to bite on different objects. Mothers should try to give them a teether rings to make them a little quiet. Of course, chewing on different things can also be the innate response of the baby to the strange sense of the mouth.

e) Sucking a Finger: In addition to biting on things during teething, it may be accompanied by sucking a finger. The baby can suck and bites for a few hours during the day. By doing this, he also tries to eliminate the pruritus of the gums. The joy of this action helps the baby to eliminate the pain and pressure of the teeth. Therefore, a mother may find that her baby calms down by chewing his fingers. She should try to keep her baby’s hands clean so no microorganisms can enter the baby’s mouth.

f) Change in Eating Habits: Wounds and gum’s swelling can make sucking painful for the baby. If the baby is hungry but runs away from feeding by mother’s breast or bottle, he may be teething. In this case, babies who eat solid foods tend to breastfeed or feed on the bottle, because the spoon annoys their inflamed gums. Some other babies also do quite the opposite of doing this, that is, they eat more because the bilateral pressure gives them a good feeling. On the other side, babies who still feed on the breast or bottle may eagerly start feeding at the beginning but quickly refrain from eating, because the sucking action puts very uncomfortable pressure on the gums and ear canals.

g) Baby’s Temper Tantrum: Primary tooth eruption (the outward movement of the tooth in the bone and gum) is usually done in a manner so that this action takes place more often overnight compared to the daytime, consequently, the baby will be more restless at night. The pain of teething can cause her sensitivity and irritability, and make him constantly cry.

h) Acne:In some children, teeth eruption may be accompanied with symptoms such as acne. Of course, this symptom is not definitive like fever, and it may have other causes. Skin hypersensitivities are more likely in children due to delicateness and vulnerability of their skin, and occasionally these acnes are signs of gastrointestinal symptoms.

i) Pulling the Ears: Holding, gripping or even pulling the ears, although sometimes indicative of ear infections, it can also be a sign of tooth eruption; in this situation, the pain that occurs in the jaw could be a transferred pain to the ears.

j) Cough: In some cases, when children are teething, they start coughing at that period of time.

Two Misconceptions about Signs of Teething

Many still believe that a child can have a fever during teething 5]] (even healthcare providers!), but on the contrary, some believe the temperatures above 102 degrees Fahrenheit are not related to teething [6]. If fever exists in this period, it is a mere accident and must be caused by other factors [7] . However, if we compare the temperature of the baby’s body who is teething with a child who does not, his body temperature may be slightly high, but this increase is not important enough to be called fever. Hence, why do many babies with teeth eruption have a fever? What is the explanation for that? Another misconception is that teething causing diarrhea [8,9]. Severe diarrhea or constipation is not associated with teeth eruption, and these two events should normally not be accompanied with each other. Although fever and diarrhea are not so much related to the teething, interestingly these signs are seen in some children with the onset of teeth eruption. The concurrency of diarrhea, fever and tooth eruption has two main causes: first, around the age of 4-6 months, when the teeth are emerging, the child’s immune system gradually become independent of the mother reduces the body’s resistance, and therefore this causes symptoms such as fever and diarrhea. Secondly, at this time, children take everything in their mouths to relieve the itching of the gums and discomfort that they develop during teething, but these objects may be contaminated to microbes [10], hence, there is the expectation of diarrhea in infants. Consequently, the emerging of teeth itself does not cause severe diarrhea. On the other hand, at this time, the safety of the immune system from the mother to the infant will diminish, [11] and the child’s body must build the safety components. Therefore, the reduction of maternal immunity which is transferred from the mother to the child can be a reason for fever or infection, [11] which is only a concurrency with teething; and the tooth eruption alone, do not cause this symptom.

Final Words

To summarize the article, the eruption of the teeth is a natural occurrence that occurs without acute and severe problems. It is a physiological phenomenon that will be associated with the other physiological phenomena such as increased saliva in the child, gums swelling, biting on any objects, disturbance in night sleepless, changes in eating habits, and so on.,. The tooth eruption does not pose a problem for the child. Some people mistakenly think that when the baby wants to have a new tooth, he is prone to having a fever, severe diarrhea or even constipation. The growth of teeth will never be accompanied by high fever. The teeth eruptions are different in newborns, but in general, most of them have first teeth at six months of age. Noteworthy that some of the symptoms of teething are similar to those of some diseases, which should be contacted with a pediatric pediatrician in the event of worsening of the symptoms.


Read More About Lupine Publishers Journal of Dentistry and Oral Health Care Please Click on the Below Link: https://lupine-dentistry-oral-health-care.blogspot.com/


Wednesday, 7 June 2023

Lupine Publishers | Maurice Roy’s Protest

 Lupine Publishers | Journal of Modern Approaches in Dentistry and Oral Health Care


Opinion

Maurice Roy was born on 24 December 1866. At 14, he entered a dental surgery as an apprentice technician. In 1884, he enrolled at the Dental School of Paris where he was awarded his diploma in 1886. He became a tenured teacher in 1900. He passed his baccalaureate. He then started medical studies. In order to meet his own needs, he worked as a dentist. He was exempted from military service because of his myopia; he was able to devote himself to writing his thesis he sustained in 1894. When the Dreyfus Affair broke out, at the cries of Zola in J’Accuse! published in 1898, he signed the petition for the rehabilitation of the captain. Having contributed towards the creation of FDI World Dental Federation in 1901, he became a member of its executive body in 1904, then its vice-president in 1911. He was re-elected to the post in 1936. In 1902 he founded the French Dentists Cooperative Society (Cooperative Society of Dentists of France), which supplied equipments to the practitioners of the country. In 1914 he created the relief committee for the wounded to the jaws and the face (Relief Committee of the wounded of the jaws and the face). He dedicated himself: he established surgical and prosthetic rehabilitation protocols that were used by other centers. In 1915 he created the Fraternal aid for French and Belgian war victims dentists (Fraternal help to French dentists and Belgian victims of war). In 1923 he took the lead of The Odontology magazine. Roy made it a key player in dentistry of that time. Every themes were subjectively studied. In 1928 he left the public welfare [1-3].

On 28 July 1933, Roy made the executive body pass a motion during FDI World Dental Congress in Edinburgh after Georges Villain, his president and friend, gave a thundering speech to denounce Nazi crimes and to help Jewish German dentists, that stated that: “The executive body of FDI, that duly gathered in session in Edinburgh on 28 July 1933 only to consider the protection of rights obtained by dentists from all over the world thanks to the diplomas granted by the competent authorities of their respective countries [4], declared that no matter of race, of religion or of politics under no circumstances must limit the liberty and the practising of our duly qualified colleagues. Likewise, no restriction which would lead them to breaches of their moral and professional obligations must be imposed on them.” Having made everything to help their colleagues although unsuccessfully the committee passed this motion unanimously excluding Germany who chose to withdraw from FDI. During the 1936 congress of Vienna, Roy received the Miller Prize for his work: the highest distinction that was awarded by the 33-member countries of the executive body including Germany. He received the Legion of Honor this same year. As they were shouted down during the 1938 congress, the Germans were absent from the 1939 congress of Zürich [5]. While the country was occupied, Roy hid aviators and Resistance fighters in his house. While he was the head teacher of the Dental School of Paris, he prohibited the wearing of the yellow star there, this could have caused him an arrestation from the Pétainist font. During a congress in Paris, he left the inaugural session just as the Germans appeared. That provoked a tremendous outcry. While the demands of the Germans were getting insistent, he stopped practicing his dental surgery in 1942, but kept his positions at the Dental School of Paris, at The Odontology magazine and at the Cooperative until his death [6,7]. His convictions caused him insulting articles in the Occupation newspapers: I’m everywhere. Because he was suspected by the Gestapo, he received only routine visits. Maurice Roy died on 5 January 1947 (Figures 1-6).

Figure 1: Maurice Roy (Roy Family, 2011).

Lupinepublishers-openaccess-dentistry-oralhealth

Figure 2: Georges Villain (1881-1938), ©BIUM, 2008

Lupinepublishers-openaccess-dentistry-oralhealth

Figure 3: Dental School of Paris - 57, rue Rochechouart (public domain).

Lupinepublishers-openaccess-dentistry-oralhealth

Figure 4: Congress of the Fédération Dentaire Internationale in Zurich, in 1939 (Ennis, 1967). Maurice Roy is in the 1st rank, 2nd on the right. There is no German dentist in this meeting.

Lupinepublishers-openaccess-dentistry-oralhealth

Figure 5: Reichszahnärzteführer Dr. Ernst Stück (1893 – 1974) (public domain).

Lupinepublishers-openaccess-dentistry-oralhealth

Figure 6: VIIth congress of the German dentists directed by Ernst Stück in 1935, in Berlin (public domain).

Lupinepublishers-openaccess-dentistry-oralhealth


Monday, 24 April 2023

Lupine Publishers| Atypical Manifestation of a Tooth Crack

Lupine Publishers| Journal of  Dentistry and Oral Health Care

Abstract

A patient presented with severe pain in the area of teeth #2 and #31. Prior to seeking dental care, the pain had been so severe together with other clinical manifestations that the patient sought medical attention for a heart attack. After elimination of the occurrence of a m.i., the pain was thought to be dental in origin and dental care was sought. No carious lesions or endodontic problems were found upon radiographic examination. However, careful oral examination revealed the presence of a crack transcending tooth #31. Following tooth extraction and immediate implant placement, no further pain was experienced by the patient.

Introduction

Splits or fractures are the third most common cause of tooth loss in industrialized countries, primarily affecting maxillary molars and premolars, and mandibular molars [1]. However, most clinicians would agree that tooth cracks are difficult to diagnose [2- 4]. Although pain on biting is often considered the most reliable diagnosis for a tooth with a visible crack [5], the most common symptom of a cracked tooth is pain to cold [3]. Further, pain and other symptoms associated with tooth cracks can manifest in different ways, often in areas remote from the actual crack [1]. Interestingly, it has been reported that pain associated with tooth cracks are less likely in teeth with stained cracks or exposed roots, or in non-Hispanic whites [4]. This paper discusses the atypical pain caused by a root fracture in a molar tooth and which manifested in unexpected and misleading ways.

Patient Consultation

A 50 y.o. male patient in good general health presented with pain in the area of teeth #2 and #31. The patient was a dentist and reported that he had experienced severe pain on the left side of his face, with pain extending down his left arm together with heart palpitations and elevated blood pressure. Suspecting a M.I., the patient sought medical care but a visit to the Emergency Room together with blood tests indicated that the patient was not experiencing a heart attack. The pain was ascribed to dental issues on the right side of the face. However, the patient reported no pain on biting or sensitivity to cold.

Clinical Examination

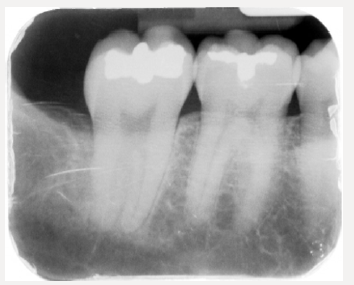
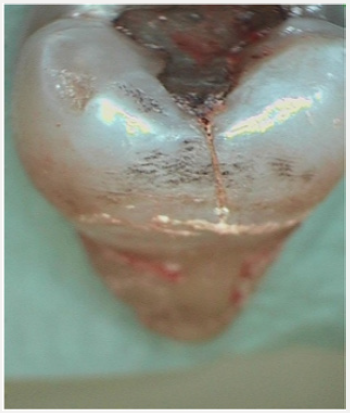
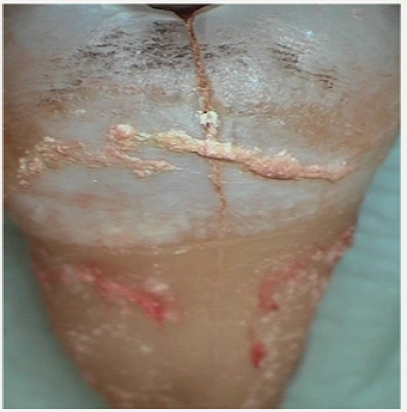
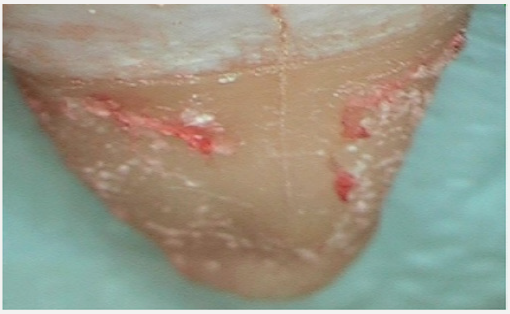
Radiographic examination of the patient, (Figure 1) indicated no carious lesions, sepsis or other issues with his dentition. However, careful intra-oral examination of the teeth indicated the presence of a crack on the distal surface of Tooth #31, (Figure 2). The crack appeared to have initiated from an apparently defective amalgam restoration, (Figure 3), and descended vertically to the apex of the tooth, (Figure 4). This conclusion appears to be justified because the literature indicates that a major predisposing factor to tooth fracture are mesio-occluso-distal restorations with mandibular first molar teeth being particularly affected [6]. Interestingly, the presence of calculus was noted in the buccal enamel and there are indications that this deposit caused widening of the enamel crack. No defects or lesions were noted in any other maxillary or mandibular teeth.

Figure 1: Radiograph of patient’s teeth.

Lupinepublishers-openaccess-dentistry-oralhealth

Figure 2: Intra-oral photograph of affected tooth.

Lupinepublishers-openaccess-dentistry-oralhealth

Figure 3: Intra-oral photograph of the affected tooth.

Lupinepublishers-openaccess-dentistry-oralhealth

Figure 4: Crack on the distal aspect of tooth #2.

Lupinepublishers-openaccess-dentistry-oralhealth

Treatment Regimen

In consultation with the patient, it was decided that the affected tooth could not be salvaged, and it was extracted under local anesthesia. Because the extraction site was infection-free, the periodontal condition was satisfactory, and the bone was solid and well-vascularized, an immediate implant was placed, (Figure 5).

Figure 5: Immediate implant placed following extraction.

Lupinepublishers-openaccess-dentistry-oralhealth

Prognosis

After extraction of tooth #31 and resolution of local anesthesia, the pain was immediately eliminated. Satisfactory healing and osseo-integration are projected for the affected area.

Conclusion

Cracks in teeth weaken them and pain from cracked teeth can be felt in areas remoted from the affected tooth. What was unusual in the present case is the pain was experienced on the other side of the mouth from the affected tooth and intensified to the point that the patient suspected a myocardial infarction. Although tooth crack-induced pain often can be experienced in areas remote from the affected tooth, the existence of pain, so severe that it mimicked a heart attack, and occurring on the other side of the mouth was unusual. This particular case reinforces the need for clinicians to carefully examine all facets of the dentition of patients presenting with oral pain. Cracks in enamel do occur and, as in the present case, may originate from a defective restoration. However, crack progression to the tooth apex and sudden, sharp onset of pain is unusual. Even more unexpected is that the pain was experienced on the opposite jaw to the affected tooth.

Read More About Lupine Publishers Journal of Dentistry and Oral Health Care Please Click on Below Link
https://lupine-dentistry-oral-health-care.blogspot.com/

Wednesday, 19 April 2023

Lupine Publishers| The Age Old Misnomer: Oral Pyogenic Granuloma–A Case Report

 Lupine Publishers| Journal of Dentistry and Oral Health Care


Abstract

An essential diagnostic challenge often faced by oral physicians is diagnosing soft tissue enlargements of the oral cavity. The fundamental reason being there are a diverse group of pathologic processes that can produce such lesions. Any intra-oral enlargement seen may represent a variation of normal anatomic structures, developmental anomalies, inflammation, cysts or even a neoplasm. Confined to these are the group of reactive hyperplasias of the oral cavity, which develop in response to a chronic, recurring tissue injury that stimulates an exuberant or excessive tissue repair response. Pyogenic granuloma comes under as one of the most common entities responsible for causing soft tissue enlargements.

Keywords: Pyogenic Granuloma; Oral Cavity; Inflammatory Hyperplasia; Misnomer

Introduction

Pyogenic granuloma is one of the inflammatory hyperplasia seen in the oral cavity [1]. It is not associated with pus as its name suggests and histologically it resembles an angiomatous lesion rather than a granulomatous lesion [2]. Thus, the term is a misnomer and in reality arises in response to various stimuli such as low-grade local irritation, traumatic injury or hormonal factors [1,2]. Typically, it presents as an exuberant, red painless mass that easily bleeds, ulcerates and grows rapidly and is frequently seen on the gingiva [3]. Surgical excision with linear closure allows histologic examination of the tissue. It also has the lowest rate of recurrence and is therefore the treatment of choice [4]. Hereby, we present a case of a 21-year-old male patient who presented with a growth on the gingiva and bleeding in upper front teeth region.

Case Report

A 21-year-old male patient reported with a growth behind the teeth in the upper front tooth region. The growth had first appeared two months back and had been slow growing to attain the present size. The patient gave a history of mild intermittent pain which aggravated on chewing food and was concerned about the compromised esthetics. His medical, dental and family histories were non-contributory. He was an avid pan and gutkha chewers since three years. On examination an exophytic growth on the palatal aspect of upper right canine between the right canine and first premolar was seen. The growth was irregular in shape, about one cm in size, smooth and lobulated (Figure 1A). It was pedunculated, soft in consistency and there was bleeding on provocation (Figure 1B). Based on the clinical examination we came to a provisional diagnosis of pyogenic granuloma. An excisional biopsy was carried out under local anesthesia (Figure 1C) and the report confirmed the same (Figure 1D). The patient was recalled after one, three and six months and it showed no recurrence of the growth.

Discussion

In 1844, Hullihen [5] described the first case of pyogenic granuloma in English literature. In 1897, pyogenic granuloma in man was described as “botryomycosis hominis.” Hartzell [6] in 1904 is credited with giving the current term of “pyogenic granuloma” or “granuloma pyogenicum.” It was also called a Crocker and Hartzell’s disease [6]. Angelopoulos histologically described it as “hemangiomatous granuloma” due to the presence of numerous blood vessels and the inflammatory nature of the lesion [7]. Cawson et al. [8] in dermatologic literature have described it as “granuloma telangiectacticum” due to the presence of numerous blood vessels seen in histological sections. They described two forms of pyogenic granulomas, the lobular capillary hemangioma (LCH) and the non-lobular capillary hemangioma (non-LCH) [2]. The exact etiopathogenesis remains unknown, although contributory factors include trauma, inflammation and infectious agents. Female sex hormones may also play a role as the condition occurs at increased frequency in pregnant women and in those who use oral contraceptive pills. It is believed that trauma and female sex hormones enhance expression of angiogenic factors such as basic fibroblast growth factor (bFGF) and vascular endothelial growth factor (VEGF) which will lead to evolution of the pyogenic granuloma. Medications such as isotretinoin, acitretin, cyclosporine, lamivudine, docetaxel, imatinib, and indinavir may also be contributing factors. Infections such as caused by herpes simplex type-I and Epstein-Barr virus have also been incriminated [4]. Oral pyogenic granulomas occur in all age groups, children to older adult, but are more frequently encountered in females in their second decade due to the increased levels of circulating hormones estrogen and progesterone [2]. Pyogenic granuloma of the oral cavity appears as an elevated, smooth or exophytic, sessile or pedunculated growth covered with red hemorrhagic and compressible erythematous papules, which appear lobulated and warty showing ulcerations and covered by yellow fibrinous membrane [9]. The color varies from red, reddish purple to pink depending on the vascularity of the growth. The gingiva, especially the marginal gingivais affected more than the alveolar part [10,11]. Besides the gingiva it is also noticed on the lips, tongue or buccal mucosa, affecting the maxilla more than the mandible, the anterior region than the posterior with the buccal surfaces being affected more than the lingual surfaces. The size varies from a few millimeters to several centimeters and it is usually slow growing, asymptomatic, painless growth, but at times it grows rapidly [9,10].

Differential diagnosis of pyogenic granuloma includes peripheral giant cell granuloma, peripheral ossifying fibroma, fibroma, peripheral odontogenic fibroma, hemangioma, conventional granulation tissue, hyperplastic gingival inflammation, Kaposi’s sarcoma, bacillary angiomatosis, angiosarcoma, and non Hodgkin’s lymphoma [12]. Radiographic findings are usually absent. However, Angelopoulos [7] concluded that in some cases long standing gingival pyogenic granulomas caused localized alveolar bone resorption [12]. Histologically, the lesion appears as a lobular proliferation of capillaries with each lobule containing a central feeder vessel surrounded by aggregates of capillaries [4]. The lobules are separated by a fibro-myxoid stroma. In those lesions that are undergoing regression, there may be extensive fibrosis [4,13]. For gingival lesions, excising the lesion down to the periosteum and scaling adjacent teeth to remove any calculus and plaque that may be a source of continuing irritation is recommended. Although surgical excision is the considered the treatment of choice, management of pyogenic granuloma depends on the severity of symptoms [3,14]. If the lesion is small, painless and free of bleeding, clinical observation and follow up are advised. Other treatment modalities include laser surgery, electrodessication. Injection of absolute ethanol, sodium tetradecylsulfate (sclerotherapy) and corticosteroids have also been tried with successful results in cases with recurrent lesions [15]. The prognosis is usually excellent, and the lesion usually does not recur unless inadequately removed. The recurrence rate is higher for pyogenic granulomas removed during pregnancy. Other possible reasons for recurrence include; incomplete excision, failure to remove etiologic factors, or due to re-injury to the area, making follow up necessary [14,16].

Conclusion

Despite the fact that pyogenic granuloma is a non-neoplastic growth in the oral cavity; a proper diagnosis, timely prevention and appropriate management are of utmost importance, careful diagnosis is essential to differentiate this lesion from other vascular lesions. Surgical excision of the growth, along with curettage should be done to prevent recurrences of this common lesion. And though the term pyogenic granuloma is still the used terminology of choice, it is a well-known fact that it is not associated with pus and histologically it resembles an angiomatous lesion rather than granulomatous lesion. Thus, it indicates that despite the term “pyogenic granuloma” being a misnomer, sometimes the good old quote - “Change is the only constant” gets a reality check as clearly time wants this terminology to stay in the literature books despite it lacking any accuracy at all.

Read More About Lupine Publishers Journal of Dentistry and Oral Health Care Please Click on Below Link
https://lupine-dentistry-oral-health-care.blogspot.com/

Monday, 20 February 2023

Lupine Publishers| How to Prepare Children with Autism to Visit a Dentist?

 Lupine Publishers| Journal of Dentistry and Oral Health Care


Opinion

One of the most common problems that parents with children with autism have is to take them to a doctor’s or dentist’s office. Even if the office environment is friendly and the dentist or doctor or their assistants are kind to the child, children who have autism do not like others to come close to them, touch them, and when they are alone, someone is in contact with their bodies. When children’s physical environment is invaded, they react to this behavior and do not cooperate with the other person, and sometimes they even become aggressive. It should be said that in many cases, these children are torn apart. There are many problems when a child visits a dentist’s office. For example, special smells, a tray of dental instruments, and devices and tools may pose a threat to the peaceful world of these children. For a child with autism spectrum disorder, a dental office is full of insecurity and, consequently, is an unpleasant place [1,2].

Preparation by Parents

Here are some simple solutions that parents can do to help their children with autism when they plan to go to the dentist’s office. Make a medical bag ready for your child; it is best to let him choose this bag by himself. Meanwhile, give him times to get acquainted with the tools inside the bag so that to find out what they are. After spending some time, show him what these tools are used for, and first try them on your own, siblings or someone else. The next step is to run the show with your child, pretending to be a doctor and treat him with these tools. Now ask your child to change his place with you, and let him try this tool on you, his sister or brother or someone else. You can also use a puppet or a stuffed doll or even your own pet to display these tools. Explain to your child what each device is used for, and let him access the toys toolbox and play with them freely. When friends, neighbors, and relatives come to your home, let them play with this gadget with your child, and then tell them to change their role with your child. Remember, if your child can find a playmate to practice with these tools, he will be great of help. If possible, give him a medical phone or more realistic tools to practice with them; however, in this case, you need to make sure your child is monitored and is safe. Give him a prize after each real meeting or show-up meeting with a dentist, or returning from the medical laboratory. Finally, play with your doctor’s true name when your child feels comfortable in the “Physician and Patient” game. In addition, along with this medicine toolbox, you can read books about meeting with the dentist too [3].

How to Take an Autistic Child to a Dental Office?

It can be difficult for every child to visit a dentist, but for a child with autism, referral to the dentist is very scary. Here are some tips for parents that will make this condition easier for their autistic children [4-6].

Before the Appointment

a. First Method: Try to get an appointment from dental centers that have been established for people with disabilities. These centers experience the treatment of disabled children and usually know what to do to make your child feel relaxed and happy during treatment. If your child needs something special at a specific time, please inform the center before visiting. You can also tell them about your child’s interests so that the dental center’s staff can talk to him about his interests while he is being treated [7].

b. Second Method: Consider the appointment for a day when your child is not busy. In order to minimize the stress on your child, it is advisable to rest well before going to the dentist. So, consider a day to visit that your child has not done much. This will reduce her stress and cry. In order to provide him with the ideal condition, it is advisable for the dentist to have free time before and after the visit so that he can cope with the situation well [8].

c. Third Method: Try to tell stories about the dentists for your child. Dentists are usually a frightening person for autistic children. So, if they know what happens when they are treated, their fear will be reduced.

d. Fourth Method: Talk to him about the fears your child may face. The mouth is a sensitive part of the body, and for some autistic children, this part has a special sensitivity. As a result, your child may have many concerns. Therefore, confirm his emotions and trust him; for example, you can tell him”It’s quite common for you to be afraid, so many people are afraid of a dentist. But I know this doctor. He always tries to be very careful and do his work the best. I know you do not want to go to dentistry, but the dental practitioner takes care of your teeth to make sure that they are healthy. We have to go there, but you may not love him. “

e. Fifth Method: Plan for a stimulus activity. For example: watching a movie, visiting his favorite park and even buying a small toy are things that can make your child happy. Before you go to the dentist, choose this activity and be sure it will be very helpful. Try telling your child about this encouraging activity, because he has hope for reaching that. For example: If your child has a lot of interest in the ribbons, tell him: “After dentistry, we go shopping and you can buy two ribbons.” As a result, when your child is in fear, he will think about his ribbons during the treatment. If you think that your child will be tired after dentistry, try to consider small activities. Do not use food as encouragement, because after the treatment, he cannot eat for a while.

f. Sixth Method: Give him food before leaving. Your child can not eat anything for a while after dental procedures. A hungry child is a child who easily cries and gets tired. Make sure your child has eaten her food, and then brush her teeth without any hurry [10-12].

When Visiting the Dentist

a. Method 1: Inform your child that you are ready to go to the dentist. Your child should brush his teeth before leaving the house. Let him bring something like a toy or any other device to the dentist office which makes him more comfortable. Do not hurry him because it can cause stress in your child. Try telling him the plan a few hours before you are leaving. This way, if needed, he can finish doing his work without any anxiety.

b. Method 2: Be extremely patient and kind. If your child is stressful, he will behave strangely because he actually fights emotionally. Be gentle and consider that it will not be easy for your child too. Try to do things in your car that your child is interested in. Play his favorite music, talk with him about your interests; or if he is interested in singing, try to sing a song together. You should know that your child needs to be assured about the condition; may ask you questions repeatedly, so give him a peaceful answer.

c. Method 3: Talk with the dental center staffs, and ask for help for the comfort and relaxation of your child. Perhaps they are able to create a situation in which your child can have a more pleasant visit to the dentist.

d. Method 4: Thinking of not being beside him, may cause this image that you are leaving him which may develop more fear and stress. Make assure your child that you would be in the waiting room if he will need you. If your child is getting disturbed by being away from you, ask the dentist to let you stay in the room with him.

e. Method 5: Encourage and admire her after the meeting. Tell her she has done this job very well, and keep on the encouraging activity you have been considering. This will make him feel better about doing anything. If your child has had bad conditions during the treatment (crying, screaming, etc.), you should tell him: “It’s not the courage to not be afraid, the courage is to face it, and you did it very well. Although the dentistry is scary and difficult, you did it “. Tell him you are proud of him [13].

Characteristics of Children with Autism

These children have certain behavioral characteristics, some of which include:

Impairment of speaking or not speaking at all, and repeating words and sentences spoken by people around him

i. Susceptible to restlessness and discomfort due to problems in the sensory process, anxiety, fears, and difficulty of communicating

ii. Exaggerated reactions to smells, voices, special tastes and other sensory incitements

iii. Excessive use of body movements to calm himself up, such as shaking hands and waving hands

iv. Failure to respond when calling his name so that the child seems to be deaf

v. Express the discomfort of breaking up routines and habits, and reacting to changes

vi. Restlessness and agility, the need to play and touch objects, and anything around

vii. Avoiding eye and physical contact

viii. Problems in social skills

ix. Obsessive-compulsive and adherence to them

x. Lack of effective self-perception of his feelings and others

xi. The difficulty in understanding security and risk aversion.

xii. Performing repetitive games for consecutive hours

Also, these children prefer to play alone and have little fancy imagination. Some may also have symptoms of hyperactivity and early angry [14].

Oral Condition in Children with Autism

Children with autism often have no differences with normal children in the structures of the teeth, but as these children tend to eat soft and sweet foods, they sometimes have muscle weakness around their mouth. As a result, the reduction in the efficiency of the chewing is observed, and even sometimes they tend to keep the mouthfuls long in their mouth, which increases the rate of caries in these children. Also, due to the inability to brush correctly, and the lack of proper cooperation with parents, caries, and gingivitis are more common in these children [15].

Read More About Lupine Publishers Journal of Dentistry and Oral Health Care Please Click on Below Link
https://lupine-dentistry-oral-health-care.blogspot.com/

Saturday, 4 February 2023

Lupine Publishers | Open Tray Impression Technique Using the Direct Pick-Up Coping: A Case Report

 Lupine Publishers | Journal of Dentistry and Oral Health Care


Abstract

Dental implants have become a quite successful method for restoration of fully and partially edentulous patients. Impression procedure becomes exacting in implantology as compared to fixed partial denture because of lack of periodontal ligament fibers in implants. Traditionally, there are two different implant impression techniques for transferring the impression copings from the implant to the impression. The transfer technique uses tapered copings and a closed tray to make an impression. Conversely, the pick-up impression uses square copings and an open tray (a tray with an opening), allowing the coronal ends of the impression coping screw to be exposed. This article describes the Pick-up implant impression procedure that is inexpensive, clean, and easy to perform with materials commonly found in a restorative dental practice and deals with its advantages and limitations.

Keywords: Implant Impression; Implant Direct Impression; Open Tray - Pick Up Impression Coping

Introduction

The success of implant-supported restorations relies on how well the hard and soft tissue information is transferred to the laboratory [1,2]. The critical aspect is to record the threedimensional orientation of the implant as it is present intraorally, other than reproducing fine surface detail for successful implant prosthodontic treatment [3-5]. The development of impression techniques to accurately record implant position has become more complicated and challenging. Several impression techniques have been suggested to obtain a master cast that will ensure the passive fit of prosthesis on implants [6]. In implant dentistry, the two traditional ways of making an impression are the closed tray and the open tray technique. Both impression techniques have their advantages and disadvantages [7]. A recent systematic review revealed that the open tray impression technique is more accurate than the closed tray impression technique [8,9]. It has been shown that the pickup type impression coping is the more accurate type of impression as errors occur on removal and replacement of the transfer type impression copings, especially in the occlusion-gingival direction [10,11]. Characteristics of the Pickup type impression coping are that they are removed from the mouth together with the set impression. They require access to the retaining screw to allow release of the screw prior to removal of the impression coping-impression assembly, the analogues are attached to the impression copings while they are embedded in the impression tray. A custom tray with access to the impression coping screws is required [12].

Clinical Case

Open Tray Impression Procedure

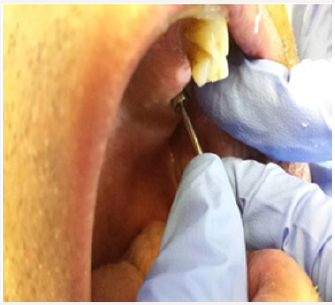
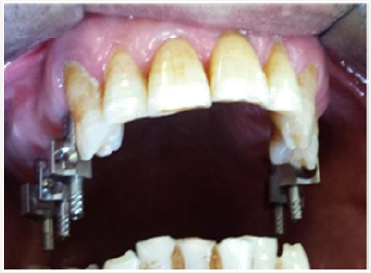
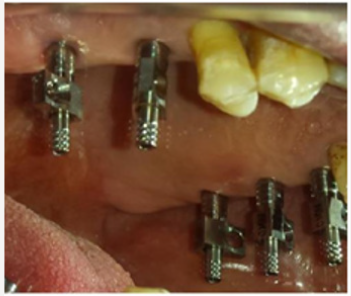
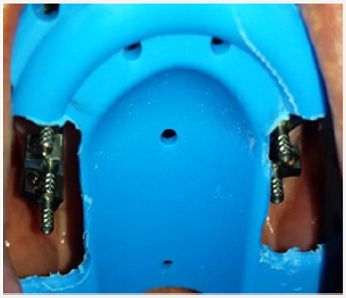
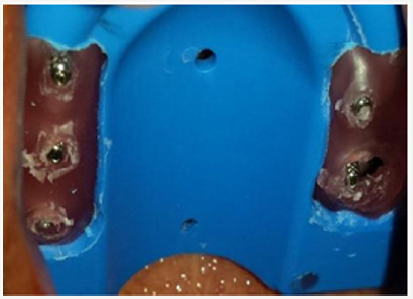
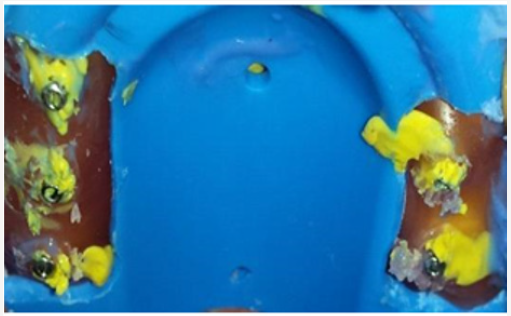
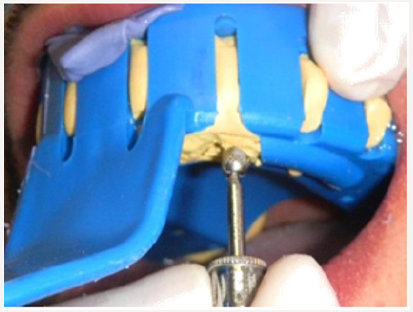
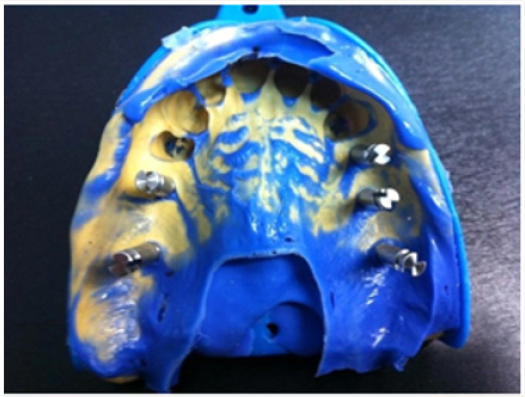
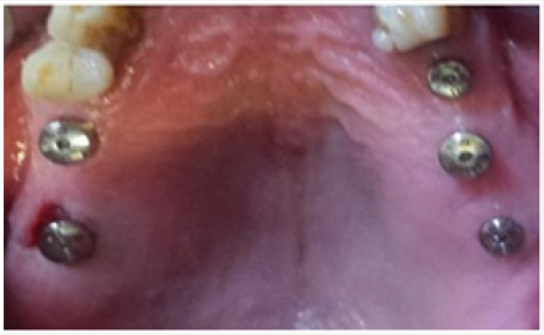
A patient consulted the Department of Fixed Prosthodontics at the Dental Clinic of Monastir to replace his bilateral terminal maxillary edentulism by implant-supported fixed prostheses . The patient had a sufficient and rectilinear mouth opening. We decided to make him five maxillary implants. To record the spatial position of the implants, we have chosen “Open tray Impression technique “using the direct pick-up copings . In the first time, the healing screws were removed (Figure 1). Then, the square impression copings were placed into the implants (Figures 2 & 3). The guide screws were tightened using the screwdriver. Retroalveolar X-rays were taken along the long axis of the implant to ensure that the impression copings were seated completely into the hex of the implants (Figure 1). The tray was perforated in the regions where implants were placed to provide access for the pick-up copings (Figure 4). The impression tray was coated with manufacturer recommended impression adhesive 5 minutes before each impression was made. Tray adhesive was applied thinly and evenly over the inner surface of each tray and extended approximately 3mm onto the outer surface of the tray along periphery. The adhesive was allowed to dry for 15 minutes before impression (Figure 4). The tray was removed from the mouth and two sections of boxing wax (Dentsply Intl) were adapted over the open-ings in the tray and sealed to the tray using a hot instrument (Figures 5 & 6).

Figure 1: Removing of healing screws.

Lupinepublishers-openaccess-dentistry-oralhealth

Figure 2: Impression copings were connected to each implant after removing of healing screws.

Lupinepublishers-openaccess-dentistry-oralhealth

Figure 3: Impression copings were connected to each implant after removing of healing screws.

Lupinepublishers-openaccess-dentistry-oralhealth

Figure 4: Intra oral view of pick up impression copings through the impression tray.

Lupinepublishers-openaccess-dentistry-oralhealth

Figure 5: two sections of boxing wax (Dentsply Intl) were adapted over the open-ings in the tray.

Lupinepublishers-openaccess-dentistry-oralhealth

Figure 6: two sections of boxing wax (Dentsply Intl) were adapted over the open-ings in the tray.

Lupinepublishers-openaccess-dentistry-oralhealth

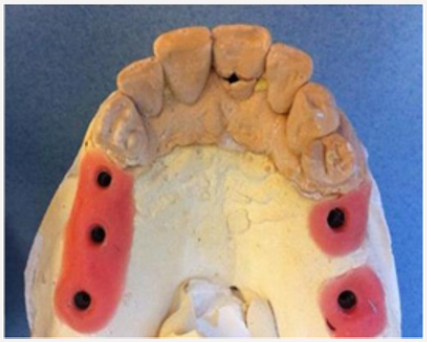
Other open-tray impression protocols recommend wiping off the excess impression material that extrudes through the hole in the tray with a gloved finger or injecting impression plaster through the hole(s) in the tray to fill the remaining void. This may be messy to accomplish. Additionally, the powder on some gloves may inhibit the polymerization of vinyl polysiloxane (VPS) impression materials Wax placed over the hole in the tray prevents contact of the impression material with the gloves [13]. The heavy consistency polyvinylsiloxane impression material was loaded inside the impression tray and light consistency polyvinylsiloxane impression material was meticulously syringed around the impression copings to ensure complete coverage of the copings (Figure 7). The screwdriver was used to loosen the guide screw within the impression post (Figure 8). The impression was taken out from the patient’s mouth. The corresponding analog was selected and the impression post was placed into the implant analog and the guide screw was tightened by using the screwdriver (Figure 9). The healing abutments were replaced immediately to prevent soft tissue collapse over the implant (Figure 10). Before screwing in, implant analog should be placed in line with the grooves of impression coping to achieve accurate passively fitting prosthesis. The impression was now ready to be used to create a model (Figure11).

Figure 7: Open tray Impression.

Lupinepublishers-openaccess-dentistry-oralhealth

Figure 8: The copings screws are unscrewed to be removed along with the impression.

Lupinepublishers-openaccess-dentistry-oralhealth

Figure 9: Impression with coping analog assembly.

Lupinepublishers-openaccess-dentistry-oralhealth

Figure 10: The healing abutments were replaced immediately.

Lupinepublishers-openaccess-dentistry-oralhealth

Figure 11: Occlusal view of hard and soft tissue cast recovered from impression.

Lupinepublishers-openaccess-dentistry-oralhealth

Discussion

In direct technique, the impression coping lies within the impression. Advantages of direct technique are minimization of dimensional changes in impression upon removal from patient’s mouth, no need to screw in coping again as it comes along with the impression and useful in patients with angulated implants [14]. When impressions are required for multi implant restorations the precision of the impression is even more critical. This is because frameworks will be constructed from the master cast and mis-fit in the frameworks can lead to stress applied to the implants on screwing down the framework [12]. For situations in which there were three or fewer implants, most studies showed no difference between the pick-up and transfer techniques, whereas for situations in which there were 4 or more implants, more studies showed more accurate impressions with the pick-up technique (open tray) than the transfer technique (closed tray) [6]. Fourteen studies compared the accuracy of pick-up and transfer impression techniques [15,16]. Of the 14 studies, five showed more accurate impressions with the non-splinted pick-up technique [17], two with the transfer technique, and three showed no difference between them [8,18].

Closed tray (transfer, indirect) technique using tapered impression copings is an easy and simple technique ideal for single implant impressions and multiple parallel implants in patients with limited mouth opening [14]. When there is limited mouth opening they can be used as there may not be sufficient space for access to the screws retaining pick up type impression copings with the impression in place and in patients with an exaggerated gag reflex, when the impression has to be removed as quickly as possible [12]. The clinical situations which indicate the use of the closed tray technique are when the patient has limited inter arch space, tendency to gag, or if it is too difficult to access an implant in the posterior region of the mouth [10].

Polyether and VPS were the recommended materials for the implant impressions. Results indicated that the 2-step VPS impression was significantly less accurate than the 1-step putty and light-body VPS combination impression, the mediumbody VPS monophase impression, and the medium-body polyether monophase impression [5].

Conclusion

Several impression techniques have been advocated for implant impressions to obtain a definitive cast. Different impression techniques have some advantages and some limitations, but selection of technique depends upon operator choice and various clinical situations. Open tray (pick-up, direct) technique using square impression copings is more accurate method usually preferred in multiple implants with different angulations.

Read More About Lupine Publishers Journal of Dentistry and Oral Health Care Please Click on Below Link
https://lupine-dentistry-oral-health-care.blogspot.com/

Wednesday, 13 July 2022

Lupine Publishers| Medical Advancements: A Boon with Risks?

 Lupine Publishers| Journal of Dentistry and Oral Health


Medical Advancements: A Boon with Risks?

Diabetes was, is and will be a major cause of concern in the healthcare sector. The control of diabetes has been a mission since a long time all over the world. The use of the glucometer has made life easier for the common man. However the lack of knowledge regarding the disposal of the glucose strips and needles has also become a matter of concern. A multi-nation study reflected that about 46.9% to 67.6% of diabetics disposed the sharps into the household bins and that less than 10% used, specific containers [1]. In similar studies, improper disposal of sharps was found to be as high as 80-90% [2,3]. A study from Pakistan showed that more than 90% patients discarded them into the household bin [4]. According to the Indian Council of Medical Research, India Diabetes study circulated in 2011, revealed that about 62.4 million people in India were diabetics [5]. This makes India, the home to a huge diabetic inhabitant.

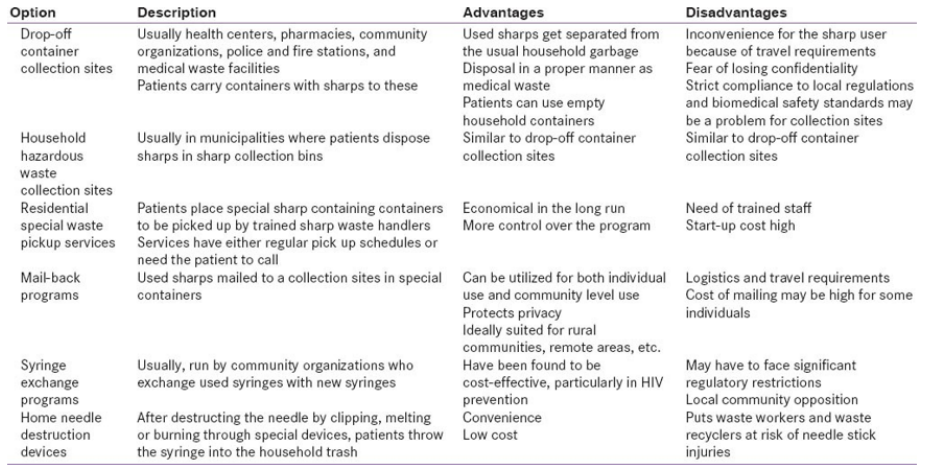
Table 1: General Guidelines for Sharps Disposal.

Lupinepublishers-openaccess-dentistry-oral-healthcare

Thereby, the seriousness of the situation not only limits to diagnosing and treating the diabetic population, but it also further includes the knowledge about the proper diabetic self-care with the diet and self-monitoring of blood glucose levels forming the important part of the same. With this being said, the disposal of the waste generated from such self-monitoring techniques becomes a part of it. Thus, if neglected, it can cause substantial damage to the health of the population as well as it may reflect a marked loss to the economy, further increasing its burden. Table 1 below shows the various sharp waste disposal techniques followed [6]. According to the Environmental Protection Agency, syringes (needles) and lancets are medical wastes called “sharps.” Sharps can be hazardous to those handling garbage, if the sharps are thrown in the regular waste. ”Sharps boxes” are recommended for home use. Various pharmacies sell sharps boxes at a reasonable price tag and also will allow you to return the boxes when they are full [7,8].

Hence, always use a sharps box for sharps disposal. Your physician may help to learn about your local disposal options and procedures. Never to re-cap your syringes before you dispose of them. In case you do not have a regular sharps box, use a hard (puncture-proof) non-clear container for disposing used clipped or un-clipped syringes and lancets. If you choose to clip the syringes, use a device that traps the clipped points in a puncture-proof compartment. Properly dispose of your syringes and lancets when traveling or bring your used sharps home for disposal [7,8]. Do not drop your used syringes or lancets into the regular trash. Do not cut off syringe needles with scissors or break off the needles. The needle could break off as you are cutting it and could hurt you or someone else. Do not use clear plastic bottles for syringe disposal as children or drug users may see the syringes and try to open the bottle. Do not put plastic bottles filled with syringes/lancets in recycle bin [7]. Therefore. it becomes very important to educate the individual about proper waste disposal of such sharps that are used at home to prevent any cross infection or any re-use of such materials in any manner.

Read More About Lupine Publishers Journal of Dentistry and Oral Health Please Click on Below Link: https://lupine-dentistry-oral-health-care.blogspot.com/

Friday, 22 February 2019

Journal of Dentistry- Lupine Publishers

Clinical Evaluation Methods of Oral Cavity Hygiene of Patients with Drug-Compensated Diabetes Mellitus Using Removable Partial Acrylic Prosthesis by Shevkunova Natalia Alekseevna in Modern Approaches in Dentistry and Oral Health Care in Lupine Publishers

The influence of hygiene products on the state of the oral cavity and dentures in 63 patients with type 2 diabetes using partial removable acrylic prostheses was studied. The results of the study showed that individual oral hygiene with the use of rinses and the care for removable dentures with the use of cleansing tablets contributed to the increase of the index of effectiveness of oral hygiene RNR (Podshadley, Haley, 1968) and removable dentures (Ambjornsen E.e.a.). The conducted measures reduced inflammatory phenomena in the tissues of the prosthetic bed in diabetic patients, which provided stable clinical results in long-term follow-up [1-8].

https://lupinepublishers.com/dental-and-oral-health-journal/fulltext/clinical-evaluation-methods-of-oral-cavity-hygiene-of-patients-with-drug.ID.000120.php

For more Lupine Publishers Open Access Journals Please visit our website: http://www.lupinepublishers.com/

For more Journal of Dentistry articles Please Click Here: https://lupinepublishers.com/dental-and-oral-health-journal/

Thursday, 24 January 2019

Lupine Publishers journals (MADOHC) - Lupine Publishers

Children’s Mouthwash; Commercial Product or Oral Health Guarantor (MADOHC)- Lupine Publishers

Nowadays, when we enter a pharmacy, we come across a variety of healthcare products that come to the market every day. Types of masks, gels, detergents and etc., which may look identical in name and application but claim to be totally different and each has its own user extent. Some of these products are commercial in nature, and some are not so important in maintaining health, and in fact, one’s health is not dependent on them. Perhaps that’s why each of us never consumed some of these health and beauty products, and we do not even know them at all.

https://lupinepublishers.com/dental-and-oral-health-journal/fulltext/childrens-mouthwash-commercial-product-or-oral-health-guarantor.ID.000164.php

For more Lupine Publishers Open Access Journals Please visit our website: http://www.lupinepublishers.com/

For more  Lupine Publishers journals articles Please Click Here: https://lupinepublishers.com/dental-and-oral-health-journal/

Tuesday, 30 October 2018

Hepatitis B Surface Antigen (Obsag) in Pregnant Women Attending Antenatal Clinic at The General Hospital, Amaku, Awka, Anambra State, Nigeria (IPDOAJ) - Lupinepublishers


This study was carried out to determine the prevalence of HBsAg among pregnant women attending antenatal clinic at General Hospital in Agba, Ekwulobia, Anambra State. Two hundred pregnant women who consented voluntarily after thorough explanation of the purpose of the study were recruited for this study. The samples were tested for the presence of antibodies using rapid Dia Spot HBsAg rapid test strip developed by Dia Spot Diagnostics, USA and ClinotechHBsAg (Clinotech diagnostics, Richmond, Canada). Analysis of the result showed that 23(11.5%) of the pregnant women had HBsAg. Statistical analysis, however, showed no significant difference between the prevalence and the age of patients, parity, trimester and type of family. The frequency of HBY carriers did not vary significantly with the Use of condoms and contraceptives. However, there was a significant frequency variation in the distribution of HBsAg between those that have previous history of transfusion, operation, circumcision and those who never had history of operation, transfusion or circumcision Therefore, the need to institute public health measures to reduce disease burden and transmission, including routine screening of all pregnant mothers for HBV infection and early passive-active immunization of babies born to HBsAg-positive mothers are advocated.

http://lupinepublishers.com/pediatric-dentistry-journal/abstracts/IPDOAJ.MS.ID.000129.php

http://lupinepublishers.com/pediatric-dentistry-journal/pdf/IPDOAJ.MS.ID.000129.pdf

Friday, 26 October 2018

Strategies for Reducing Dental Stress in Children (IPDOAJ) - Lupinepublishers


The dental office for children has always been scary and eerie. The reason for this fear is the lack of mental fitness of children towards the dental health environment. Unknown instruments, scary sounds of dental devices, and sometimes seeing others’ fears during dental procedures would affect the child’s mind; and creates fear within them. No research has pointed to the definitive causes of anxiety and stress, but some studies have shown that the bad experience of dental treatments associated with pain is one of the most common in this case

http://www.lupinepublishers.com/pediatric-dentistry-journal/abstracts/IPDOAJ.MS.ID.000126.php

http://www.lupinepublishers.com/pediatric-dentistry-journal/pdf/IPDOAJ.MS.ID.000126.pdf

Thursday, 4 October 2018

Posterior Indirect Adhesive Restorations: for Vital Posterior Teeth: Clinical Report (IPDOAJ) - Lupinepublishers


This article describes a case of compromised posterior vital teeth treated by indirect bonded ceramic restorations. A 24 year old female patient presented to the department of Prosthodontics. He was complaining about sensitivity in the posterior region. A comprehensive examination revealed failing amalgam restoration in the first molar with compromised cusps in the first molar. The treatment plan included indirect bonded ceramic restorations consisting of inlay and on lay on the concerned teeth.

https://www.lupinepublishers.com/pediatric-dentistry-journal/abstracts/IPDOAJ.MS.ID.000123.php

https://www.lupinepublishers.com/pediatric-dentistry-journal/pdf/IPDOAJ.MS.ID.000123.pdf

Wednesday, 3 October 2018

Focal Fibrous Hyperplasia: A Rare Case Report and Literature Review (IPDOAJ) - Lupinepublishers


Intra-oral fibrous type soft tissue overgrowth is common in oral cavity. It can be either benign or neoplastic lesions. Nonneoplastic type of reactive lesion seen in the oral cavity is caused by the chronic irritation. Focal fibrous hyperplasia is one such lesion which is seen in the line of occlusion. Focal fibrous hyperplasia is also known as irritational fibroma or traumatic fibroma. Proper oral hygiene, removal of etiologic factors and conservative excision will prevent the focal fibrous hyperplasia and its recurrence. Proper diagnosis, management and follow up should be done in these cases.

https://www.lupinepublishers.com/pediatric-dentistry-journal/abstracts/IPDOAJ.MS.ID.000120.php

https://www.lupinepublishers.com/pediatric-dentistry-journal/pdf/IPDOAJ.MS.ID.000120.pdf

Monday, 1 October 2018

Importance of Tooth Brushing in Pediatrics-A Short Review (IPDOAJ) - Lupinepublishers


A poor oral hygiene or any oral disease affects the oral health and then ultimately the general health of a person which in return influences the overall appearance of a person. Thus it is very important to take a good care of oral health. Oral hygiene is the practice of keeping the mouth clean and healthy by brushing and flossing to prevent gum diseases and tooth decay. It is done in order to prevent the plaque and food deposit on tooth thus to prevent caries and cavities.

https://www.lupinepublishers.com/ipdoaj/abstracts/IPDOAJ.MS.ID.000118.php

https://www.lupinepublishers.com/ipdoaj/pdf/IPDOAJ.MS.ID.000118.pdf