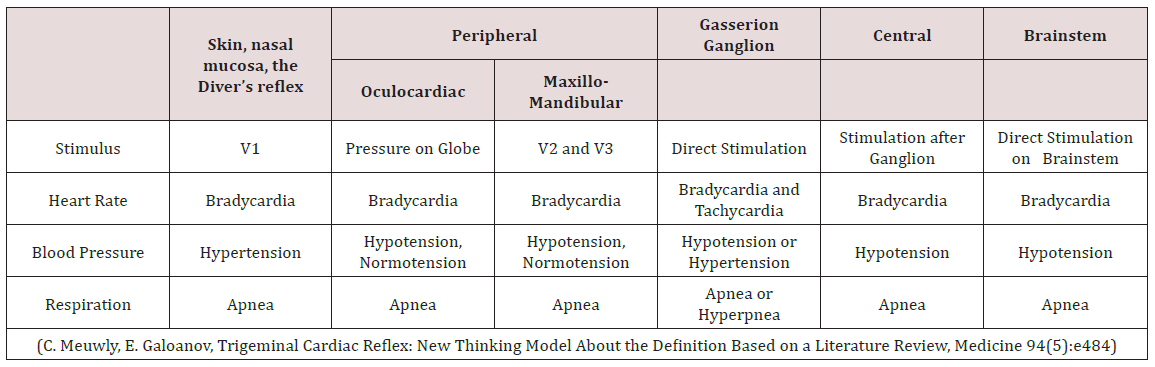
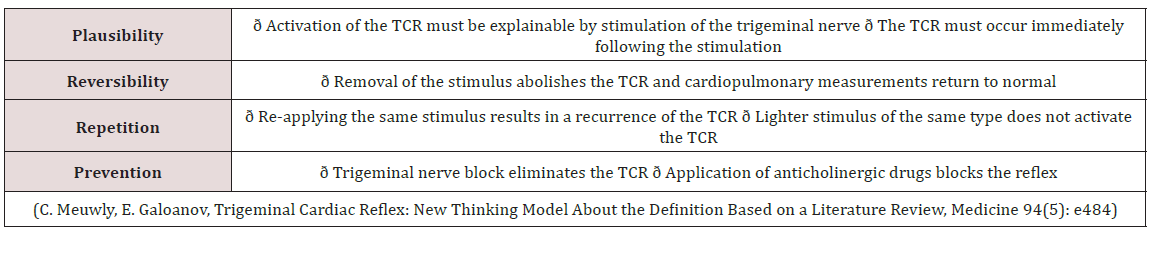
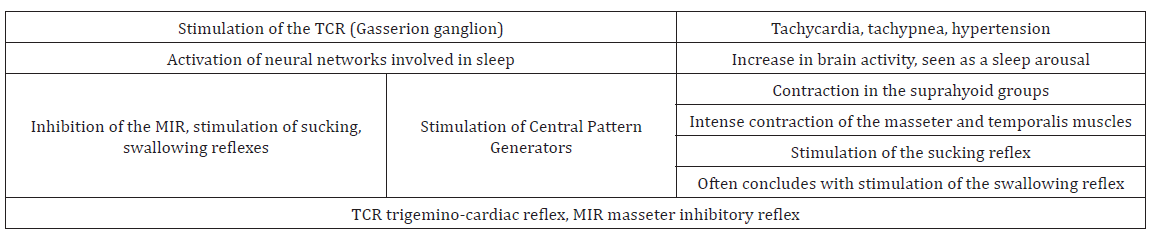
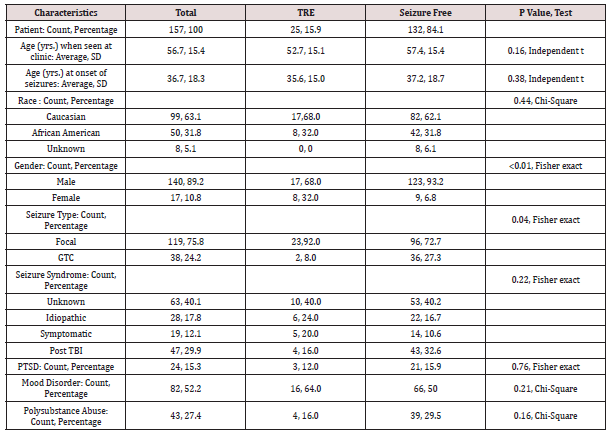
In this study we have analyzed 30 people. 10 patients Wolfram
syndrome and 20 persons control group. The genes WFS1 and CISD2,
analyzed in terms of genetic mutations made. In this study, people who
have genetic mutations were targeted, with nervous disorders Wolfram
syndrome. In fact, of all people with Wolfram syndrome. 10 patients
Wolfram syndrome had a genetic mutation in the genes WFS1 and CISD2
Wolfram syndrome. Any genetic mutations in the target genes control
group did not show.
Keywords: Genetic study; Wolfram syndrome; Mutations The gene WFS1 and CISD2; RT-PCR.
Generalizations of Wolfram Syndrome
Wolfram syndrome is a genetic disorder that affects many body
systems. The specific characteristics of Wolfram syndrome include: high
blood sugar levels due to insulin hormone deficiency (diabetes mellitus)
and progressive vision loss due to degeneration of the nerves that
transports visual information from the eye to the brain (vision
atrophy).
Symptoms and Symptoms of Wolfram Syndrome. People with Wolfram
syndrome often reveal pituitary gland disorders that lead to excessive
urination, hearing loss caused by changes in the inner ear (sensory
nervous system depression), problems with the urinary tract, decreased
testosterone levels in men (hypogonadism), Nervous or psychiatric
disorders [1].
Diabetes mellitus is usually the first symptom of Wolfram syndrome,
which is commonly diagnosed at about 6 years of age. Almost all people
with Wolfram syndrome who have diabetes need alternative insulin
therapy. Sighted atrophy is the second symptom of Wolfram syndrome,
which usually occurs at the age of 11 years. The first symptoms of
visual atrophy are vision loss and peripheral vision. Over time, vision
problems get worse, and people who have vision atrophy usually lose
their sight completely, about eight years after the onset of the first
signs of atrophic vision [2].
Figure 1: A schematic of the cause of Wolfram syndrome and common diseases in it.

The pituitary gland, located at the top of the brain, is thickened in
diabetes and does not function naturally. The disorder also releases a
hormone called vasopressin, which helps control your body's water
balance and urine output. Approximately 70% of people with Wolfram
syndrome have diabetes. Pituitary gland dysfunction can also lead to
hypogonadism in affected men. Testosterone deficiency that occurs with
hypogonadism also affects sexual development and development. About 65
percent of people with Wolfram syndrome have sensory inferiority that
can vary from depression to birth to mild hearing loss during
adolescence, which worsens over time (Figure 1).
About 60% to 90% of people with Wolfram syndrome have urinary tract
problems. Urinary problems include blockage of the canals between the
kidneys and the bladder, large bladder that can not normally be drained
(high capacity bladder), urinary tract distention (bladder sphincter
dissonance), and lack of urinary flow control (urinary incontinence)
[3]. About 60% of people with Wolfram syndrome experience neuromuscular
or psychiatric disorders, most of them with imbalance (Ataxia), which
usually begins early in puberty. Other neurological problems experienced
by people with Wolfram syndrome include irregular breathing due to the
inability of the brain to control respiration (central apnea), loss of
sense of smell, loss of oral reflexes, muscle spasm (myoclonus),
seizure, decrease Feeling in the lower limbs, such as the legs
(peripheral neuropathy) and mental disorder. Mental disorders in people
with Wolfram syndrome include severe depression and aggressive
behaviours [4].
Up to now, 2 types of Wolfram syndrome have been identified, the
first type has symptoms that are mentioned, and the second type has
gastric ulcer or intestinal ulcer with excessive hemorrhage after
injury. Therefore, the tendency to excessive hemorrhage associated with
ulcers usually results in abnormal bleeding in the digestive system. It
is worth noting that Wolfram syndrome, often due to some diseases
related to diabetes and neurological problems, often leads to mortality
in the middle of adulthood [5].
The Cause of Wolfram&s Syndrome
The mutation in the WFS1 gene, which is based on the short arm of
chromosome 4 as 4p16.1, causes more than 90% of Wolfram type 1 syndrome.
This gene provides instructions for the synthesis of a protein called
the Wolfram in, which regulates the amount of calcium in the cells. The
balance of calcium is important for many different cell functions,
including cell-to-cell communication, muscle contraction, and protein
processing. Wolfram in protein is found in many different tissues such
as pancreas, brain, heart, bones, muscles, lungs, liver and kidneys.
Within the cells, wolf amine is present in the cell membrane called
endoplasmic reticulum, which is involved in the production, processing
and transport of proteins. Wolfram in function in the pancreas, where
the protein helps to process protein processing called pransul in to
become an adult insulin hormone. This hormone controls blood glucose.
Figure 2: Schematic view of chromosome number 4 where the WFS1 gene is based on the short arm of this chromosome as 4p16.1

Therefore, WFS1 gene mutations result in the production of a wolf
amine protein whose function is diminished or does not function
properly. As a result, calcium levels in the cells are not regulated and
the endoplasmic reticulum does not work properly [6,7] (Figure 2).
When the endoplasmic reticulum does not exhibit sufficient function
of the vlfremin, the cell suffers from a physiological cell death
(apoptosis). The death of pancreatic cells, especially the cells that
produce insulin (beta cells), causes diabetes in people with Wolfram
syndrome. The gradual destruction of the cell along the visual acuity
ultimately leads to blindness in people with Wolfram syndrome. Deaths of
cells in other body systems may cause symptoms and symptoms of Wolfram
type 1 syndrome.
A specific mutation in the CISD2 gene, which is based on the long arm
of chromosome 4, 4q24, causes Wolfram type 2 syndromes. The CISD2 gene
provides instructions for protein synthesis that is located in the outer
membrane of cell structures called mitochondria. As you know, the
mitochondrial organ is the cell's energy production center. The exact
performance of the CISD2 protein is unknown, but it is believed that
this protein helps the mitochondria to function normally [8] (Figure 3).
The mutation in the CISD2 gene, which causes Wolfram type 2, produces
an abnormal, non-functional, abnormal CISD2 protein, which results in
the mitochondrial organ not functioning correctly and does not generate
the energy required for cells. Therefore, cells that do not receive
enough energy will not have enough energy
to function properly and will eventually die. High-energy cells, such as
neural cells in the brain, the eye, or the digestive tract, are most
susceptible to death due to energy loss. It is not yet clear why people
with Wolfram syndrome type 2 with the CISD2 gene mutation also
experience wound and bleeding problems in addition to the usual Wolfram
disease. It should be noted that some patients with Wolfram syndrome
have no mutations in the WFS1 and CISD2 genes, and the cause of the
syndrome in these patients is unknown. But other genes may also be
involved in Wolfram syndrome that has not yet been identified [9].
Figure 3: Schematic view of chromosome number 4, in which the CISD2 gene is located in the long arm of this chromosome 4q24.

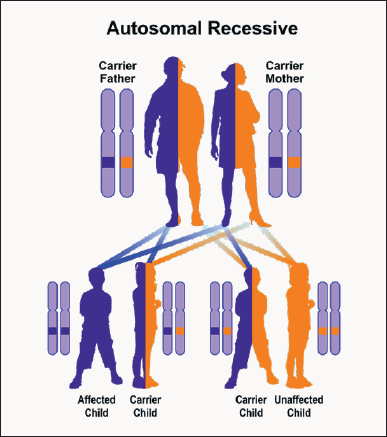
Wolfram syndrome type 1, caused by the mutation of the WFS1 gene,
follows an autosomal recessive hereditary pattern. Therefore, for the
creation of Wolfram type 1 syndrome, two versions of the mutated gene of
WFS1 (one parent and one of the mother) are needed, and the chance of
having a child with Wolfram type 1 in this case is 25% for each
pregnancy. Type 2 Wolfram syndrome, caused by the mutation of the CISD2
gene, also follows an autosomal recessive hereditary pattern. Therefore,
for the creation of Wolfram type 2 syndrome, two versions of the mutant
gene called CISD2 (one parent and one mother) are needed, and the
chance of having a child with Wolfram type 2 in this case can be 25% for
each pregnancy [10] (Figure 4).
Figure 4: A schematic view of the autosomal-inheritance
inheritance pattern that Wolfram Syndrome also follows with this
mutation in the WFS1 and CISD2 genes.
Materials and Methods
In this study, 10 patients with Wolfram Syndrome and 20 persons
control group were studied. Peripheral blood samples from patients and
parents with written permission control were prepared. After separation
of serum, using Real Time-PCR technique of tRNA molecules was collected.
To isolate Neuroglial cells erythrocytes were precipitated from
hydroxyethyl starch (HES) was used. At this stage, HES solution in ratio
of 1 to 5 with the peripheral blood of patients and controls were
mixed. After 60 minutes of incubation at room temperature, the
supernatant was removed and centrifuged for 14 min at 400 Gera. The cell
sediment with PBS (phosphate buffered saline), pipetazh and slowly
soluble carbohydrate ratio of 1 to 2 on ficole (Ficol) was poured in the
480G was centrifuged for 34 minutes. Mono nuclear Neuroglial cells also
are included, has a lower density than ficole and soon which they are
based. The remaining erythrocytes have a molecular weight greater than
fico eland deposited in test tubes. The supernatant, which contained the
mono nuclear cells, was removed, and the 400 Gera was centrifuged for
12 minutes. Finally, the sediment cell, the antibody and Neuroglial
cells was added after 34 minutes incubation at 5°C, the cell mixture was
passed from pillar LSMACS. Then the cells were washed with PBS and
attached to the column LSMACSS pam Stem cell culture medium containing
the transcription genes WFS1 and CISD2, and were kept. To determine the
purity of Neuroglial cells are extracted, flow cytometry was used. For
this purpose, approximately 4-5 x 10³ Neuroglial cells were transfer red
to1.5ml Eppendorf tube and then were centrifuged at 2000 rpm for 7
minutes at time. Remove the supernatant culture medium and there maiming
sediment, 100μl of PBS buffer was added. After adding 5-10μl PE
monoclonal anti body to the cell suspension for 60 min at 4°C, incubated
and readimme diately by flow cytometry. For example, rather than
control anti body Neuroglial cells PE, IgG1 negative control solution
was used.
i. Total mRNA extraction proceeds urein cludes 1ml solution spilled
Qiazolon cells, and slowly and carefully mixed and incubated at room
temperature for 5 minutes. Then 200μl chloroform solution to target mix,
and then transfer the micro tubes was added, and the shaker well was
mixed for 15 seconds. The present mix for 4 minutes at room temperature
and then incubated for 20 min at 4°C on was centrifuged at 13200 rpm
era. Remove the upper phase product was transfer reeducates new micro
tube and to the one times the volume of cold ethanol was added. The
resulting mixture for 24 hours at -20°C was incubated.
ii. Then for 45 min at 4°C on was centrifuged at 12000 rpm era.
Remove the super natant and the white precipitate, 1ml of cold 75%
ethanol was added to separate the sediment from micro tubes were vortex
well. The resulting mixture for 20 min at 4°C on by the time we were
centrifuged 12000 rpm. Ethanol and the sediment was removed and placed
at room temperature until completely dry deposition. The precipitate was
dissolved in 20μl sterile water and at a later stage, the concentration
of extracted mRNA was determined.
To assessment the quality of mi-RNAs, the RT-PCR technique was used.
The cDNA synthesis in reverse transcription reaction (RT) kit (Fermentas
K1622) and 1μl oligoprimers 18 (dT) was performed. Following the PCR
reaction 2μM dNTP, 1μg cDNA, Fermentas PCR buffer 1X, 0 / 75μM MgCl2,
1.25 U / μL Tag DNA at 95°C for 4 min, 95°C for 30s, annealing
temperature 58°C for 30s, and72 °C for30 seconds, 35 cycles were
performed. Then 1.5% agarose gel, the PCR product was dumped in wells
after electrophorus is with ethidium bromide staining and color was
evaluated.
Results
Figure 5: Schematic of the bond formation pattern in the WFS1 gene in the patient group and control group.
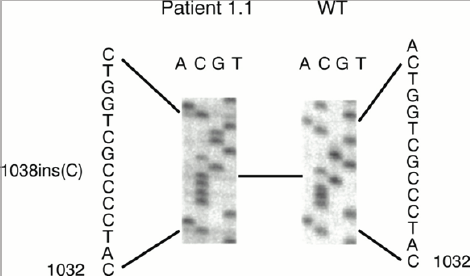
Figure 6: schematic representation of the promoter expression pattern of CISD2 gene in the patients and control group.

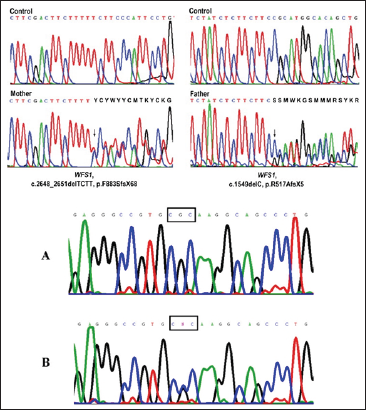
Figure 7: Schematic of mutations in the WFS1 gene in the patient group and control group.
Discussion and Conclusion
According to the results of sequencing the genome of patients with
Wolfram Syndrome, and the genetic mutations WFS1 and CISD2genes found
that about 100% of patients with Wolfram Syndrome, they have these
genetic mutations. Patients with Wolfram Syndrome, unusual and
frightening images in the process of Wolfram Syndrome, experience. Lot
epigenetic factors involved in Wolfram Syndrome. But the most prominent
factor to induce Wolfram Syndrome, mutations is WFS1 and CISD2 genes.
This genes can induce the birth and can also be induced in the
adulthood.
Read More About Lupine Publishers Online Journal of Neurology and Brain Disorders (OJNBD) Please Click on Below Link: https://brain-disorders-lupine-publishers.blogspot.com/