Monday, 23 August 2021

Lupine Publishers| New Advances in Environmental Friendly Materials

 Lupine Publishers| Modern Approaches on Material Science (MAMS)


Mini Review

This last decade has been characterized by the acquisition of new materials based on the biomass, with the objective of replacing the materials obtained from petroleum derivatives, due to the high costs, added to the fact that they are non-renewable inputs and as a measure of the preservation of the environment [1]. In all areas of study has been this responsibility of searching for new and versatile materials. Packaging, medical materials, agro-industry, cosmetics, even energy applications, in all these fields are in constant search to be at the forefront and at the same time reduce all those materials that, during and at the end of their life cycle, cause damage to the environment, either due to the emission of greenhouse gases, or because they lack biodegradable and / or compostable properties [2]. Carbohydrates and lignin are the most abundant compounds in biomass and are used as biomolecules to replace oil derivatives. In this field, starch has many advantages over synthetic materials such as the possibility of obtaining thermoplastic films with important characteristics [3], in addition to being a renewable and low-cost resource. In cases where these materials have been limited by the mechanical properties and a greater permeation, this event has been improved with the incorporation of nanofillers of starch materials of biomass origin to overcome these disadvantages [4,5].

Taking into account the bionanocomposites can be considered as the new emerging group of nanostructured hybrid materials. Bionanocomposites is defined as a mixture of naturally occurring polymer (biopolymer) and inorganic or organic filler materials that have at least one dimension on the nanometer scale. This new class of composites exhibits significant improvements in mechanical, barrier, and thermal properties, and dimensional stability. Furthermore, it also offers benefits like transparency, low density, better surface properties, good flow properties and recyclability [6]. In this sense, Garcia et al. described the nanonocomposite capable to use in agricultural applications [7]. On the other hand, the proposal to use cellulose nanofillers from the bamboo inside polymer matrices is a promising and innovative way around materials for several applications [8].

The use of carbohydrate polymers associated with hydrophobic polymers need to perform chemical functionalized onto polymer matrix and the addition of natural nanocharges, have already been proven to completely change the mechanical properties of the whole material until its response to the hydrophobicity or hydrophilicity of same [9]. In the medicinal field the biopolymer-based hydrogels, such as chitosan or alginate are used to prepare new systems for drug delivery. These macromolecules are obtained from the renewable biomass and have properties as biocompatibility, non-toxicity and availability [6]. Moreover, oil production and transportation generate serious concern because accidental spills compromise the environment. Then, renewable resources emerge as our great ally. In matter of fact, biomass compounds, such as xanthan or guar gum are currently used to increase the reserves, increasing the amount of oil accessible for exploitation. Meanwhile, biomass sorbents (like straw or sawdust) have proved to be effective to absorb oil spills. So, research on biomass materials can be considered as a clever strategy to optimize yields and protect the environment until a definitive solution for oil problem can be found. All this description previously exposed, makes us glimpse the great field that remains to be explored around materials based on the renewable biomass. This is a field that arouses a lot of interest, and that it is the duty of all researches to develop in order to obtain the best materials that comply with current standards. It is important to know these new materials must be with the environment friendly to preservation the planet in which we live.

Read More About Lupine Publishers Modern Approaches on Material Science (MAMS) Please Click on Below Link: https://lupine-publishers-material-science.blogspot.com/


Saturday, 21 August 2021

Lupine Publishers | Selective Androgen Receptor Modulators (SARMs): A Mini-Review

 Lupine Publishers | Journal of Reproductive System ans Sexual Disorders


Abstract

Selective Androgen Receptor Modulators (SARMs) were discovered in the late 1990’s.They may have an application in treatments of various diseases, including muscle wasting, cancer cachexia, breast cancer, osteoporosis, andropause and sarcopenia. In this minireview the development, pharmacodynamics, and the phase 1 and 2 trial results of the SARMs are discussed with a special emphasis on the illicit use of the SARMs.

Introduction

The androgen receptor (AR) is a member of the steroid hormone receptor family that plays important roles in the physiology and pathology of diverse tissues.AR ligands,which include circulating testosterone and locally synthesized dihydrotestosterone bind to activate the AR to elicit their effects.Ubiquitous expression of the AR metabolism and cross reactivity with other receptors limit broad therapeutic utilisation of steroidal androgens.However,the discovery of selective androgen receptor modulators (SARMs) provide an opportunity to promote the benificial effects with greatly unwanted side effects. In the last two decades SARMs have been proposed as treatments of choice for various diseases, including muscle wasting, breast cancer and osteoporosis. In addition, they may have an application in andropause, sarcopenia, cancer cachexia and as selective anabolic steroids in performing body building sports [1-6]. In this mini-review the development, pharmacodynamics and the phase 1 an2 trial results of the SARMs are discussed,with a special emphasis on the illicit use of the SARMs.

Development of SARMs

Synthesized steroidal androgens due to their ability to mimic the actions of their endogenous counterparts have been used ckinically as valuable therapeutic agents to target a variety of male and female disorders resulting from androgen deficiency. The principle clinical indication of androgens is as replacement therapy for hypogonadal men [1,2]. Other documented clinical uses of androgens include delayed puberty in boys, anemias, primary osteoporosis, heriditary angioneurotic edema, endometriosis, estrogen receptor-positive breast cancer and muscular diseases, as Duchenne’s muscular dystrophy [3-6].

Since the discovery of the therapeutic benefits of testosterone in the 1930’s a variety of androgen preparations have been introduced and tested clinically.

Unfortunately, all current available androgen preparations have severe limitations [2,6]. Unmodified testosterone is impractical for oral administration due to its low systematic bioavalability [7]. Testosterone esters (e.g., testosterone propionate and testosterone enanthate) are presently the most widely used testosterone preparations, usually administered by intramuscular injection in oil-vehicles [8,9]. A prolonged duration of action is achieved with these esters. However,they produce highly variable testosterone levels. 17-alpha alkylated testosterones (e.g., methylteststerone and oxandrolone) can be given orally. Nevertheless,they often cause unacceptable hepatotoxicity and are less efficacious; hence they are not recommended for long-term androgen therapy [9-11].

At the end of the 1990’s studies with affinity ligands for the androgen receptor started. The discovery of these nonsteoidal androgens offered an opportunity for the development of a new generation of selective androgen receptor modulators (SARMs) superior to current androgens. Theoretically, SARMs are advantegeous over their steroidal counterparts in that they can obtain better receptor selectivity and allow greater flexibility in structural modification. Thus SARMs can potentially avoid the undesirable side effects caused by cross-reactivity and achieve superior pharmacokinetic properties [12].

Pharmacodynamics of SARMs

Structural modifications of the acryl propionamide analogues bicalutamide and hydroxyflutamide led to the discovery of the first generation SARMs. The compounds S1 and S4 in this series bind AR with high affinity and demonstrate tissue selectivity in the Herzberger assay,that utilizes a castrated rat model [13-20]. Both S1 and S4 prevented castration induced atrophy of the levator ani muscle and acted as weak agonists in the prostate. At a dose of 3mg/kg/day, S4 partially restored the prostate weight to <20% of intact weight, but fully restored the levator ani weight, skeletal muscle strength, bone mineral density, bone strength and lean body mass and suppressed LH(luteinizing hormone) and FSH( follicle stimulating hormone) [20,21].

S4 also prevented ovariectomy-induced bone loss in a female rat model of osteoporosis [22]. The ability of SARMs to promote both muscle strength and bone mechanical strength constitutes a unique advantage over other therapies for osteoporosis, that only increase bone density. S1 and S4 are partial agonists thus in intact male rats [20,21]. S1 and S4 compete with endogenous androgens and act as antogonists in prostate, such SARMs with antagonistic or low intrinsic activity in prostate might be useful in the treatment of benign prostate hyperplasia (BPH) or prostate cancer. The suppressive effects of this class of SARMS on gonadotrofin secretion in rats suggests a potential application for male contraception [21]. The ether linkage and B-ring para-position substitution are critical for agonist activity of the acryl propionamide SARMs [19]. Based on crystal structures, compounds with ether linkage appear to adapt a more compact confirmation than bicalutamide due to formation of an intramolecular H-bond, allowing the B-ring to avoid steric conflict with the side chain of W741 in AR and potentially explaining the agonist activity [23].

The hydantoin derivatives developed by the BMS group have an A-ring structure that is similar to that of bicalutamide. The cyanonitro group of these molecules interact with Q711 and R752 [24- 26]. The benzene ring or the naphtidyl group,together with the hydantoin ring overlaps the steroid plane, while the hydantoin rings forms a H-bond with N705.BMS-564929 binds AR with high affinity and high specificity. BMS-564929 demonstrated anabolic activity in the levator ani muscle and a high degree of tissue selectivity as indicated by a substantially higher ED50 (Effective Dose for 50% of the population receiving the drug) for the prostate. Hydantoin derivatives are potent suppressors of LH. BMS=564929 is orally available in humans with a half-life of 8-14 hours. The prolonged half-life of these ligands in rats may explain the lower dose needed to achieve pharmacological effects. Differences regarding in vivo activities of SARMs, that share similar binding affinity and in vitro activity,may be related to the differences in pharmacokinetics and drug exposure [27].

Hanada et al. [28] Pharmaceutical Co. reported a series of tetrahydroquinolinone derivatives as AR agonists for bone. Although these compounds displayed high AR affinity and strong agonist activity in prostate and levator ani,they demonstrated little selectivity between androgenic and anabolic tissues [27]. Significant in vivo pharmacological activity was only observed at high subcutaneous doses [27,28]. Ligand Pharmaceuticals developed LGD 2226 and LGD 2941, that are bicyclic 6 anilino quinolinone derivatives, showing anabolic activity on the levator ani muscle as well as on bone mass and strength, while having little effect on prostate size in a preclinical rodent model [29-31]. LGD 2226 was also shown to maintain male reproductive behavior in the castrated rodent model [30].

Scientists at Johnson and Johnson replaced the propionamide linker with cyclic elements such as the pyrazoles, benzimidazoles, indoles and cyclic propionanilide mimetics [31]. Merck scientists have developed a number of 4-azosteroidal derivatives and butanamides [32]. All the above mentioned SARMs belong to the so called “first generation SARMs”. The mechanisms that contribute to the tissue specific transcriptional activation and selectivity of biologic effects of the SARMs remain poorly understood.Three general hypotheses have been proposed, although these hypotheses are not mutually exclusive.

a) The coactivator hypothesis assumes that the repertoire of coregulator proteins that associate with the SARM-bound AR differs from that with testosterone-bound AR leading to transcriptional activation of a differentially regulated set of genes.

b) The conformational hypothesis states that functional differences in ligand classes (agonist, antagonists and SARMs) are reflected into conformationally distinct states with distinct thermodynamic partitioning. Ligand binding induces specific conformational changes in the ligand binding domain, which could modulate surface topology and subsequent proteinprotein interactions between the AR and other coregulators involved in genomic transcriptional activation or cytosolic proteins involved in non-genomic signalling. Differences in ligand-specific receptor conformation and protein-protein interactions could result in tissue-specific gene regulation, due to potential changes in interactions with the AR effectors, coregulators or transcriptional factors.

c) The third hypothesis states that the tissue selectivity of SARMs could also be related to differences in their tissue distribution,potential interactions with 5-alpha reductase or CYP19 aromatase or tissue specific expression of coregulators [33]. Testosterone actions in some androgenic tissues are amplified by its conversion to 5-alpha dihydro testosterone [34]. Nonsteroidal SARMS do not serve as a substrate for 5-alpha reductase. Tissue selectivity of SARMs might be related to tissue specific expression of coregulatory proteins. Similarly, some differences of the action of SARM of testosterone could be related to the inability of nonsteroidal SARMs to undergo aromatization.

Preclinical and early clinical trials with SARMs

A large number of candidate SARMs have undergone preclinical proof of concept and toxicology studies and have made it iinto phase 1 and phase2 clinical trials [29,35]. These compounds are being positioned for early efficacy trials for osteoporosis,frailty,cancer cachexia and aging-associated fundamental limitations. The use of SARMS for the treatment of androgen defiency in men has been proposed. However, the relative advantages of SARMs over testosterone for this indication are not readily apparant. Many biological features of testosterone, especially its effects on libido and behavior, bone and plasma lipids require its aromatization to estrogen. Because the currently SARMs are neither aromatized nor 5-alpha reduced, these compuonds would face an uphill regulatory bar for FDA approval, as they would be required to show efficacy and safety in many more domains of androgen action, than has been required of testosterone formulations.

While the FDA regulatory pathway for the approval of drugs for osteoporosis has been well delineated, because of precedence set by previously approved drugs, the pathway for approval of function promoting anabolic therapies has not been clearly established. Efforts are underway to generate a consensus around indications, efficacy outcomes in pivotal trials, and minimal clinically important differences in key effective outcomes These efforts should facilitate efficacy trials of candidate molecules. There are 2 types of administering SARMs: orally or in injectable dosages. Well known SARMs are LGD-4033, Ostarine (MK-2866), S4(Andarine), RAD 140, Cardarine(GW 501516) and SR9009. The last two preparations are usually grouped with SARMs, but are not the same and are used as endurance supplements.SARMs have been prohibited by the World Anti-Doping Agency (WADA) since 2008. SARMs have the potential to be misused for performance enhancement in sport due to their anabolic properties, as well as their ability to stimulate androgen receptors in muscle and bone. THey are currently prohibited atall times-in the category of “other anabolic agents” under section S1,2 of the WADA Prohibited List [36] Full clinical FDA approval for human consumption as prescription drugs has not yet been accomplished for any of the SARMs until now.

Ligandrol (LGD-4033)

Ligandrol is a SARM discovered by Ligand Pharmaceuticals and currently under licensed development by Viking THerapeutics [37]. There has been a lot of research into the efficacy of SARMs, but very little published research to date on LGD-4033. Ligandrol has exhibited desirable in vivo efficacy on skeletal muscle and bone measurements in animal models of disease. There is only one published study on the effects of LGD-4033 in humans, as well as phase B1 clinical trial results. A 2010 phase1 clinical trial was the first study in humans of LGD-4033 and evaluated the safety, tolerability and oharmacokinetic profiles of the molecule in a single escalating dose, double-blind, placebo-controlled study in 48 healthy volunteers [38].

In 2013, Bhasia et al. [36] conducted a rigorous 3-week pacebocontrolled study of 76 healthy men (21-50 years),that looked at the safety and tolerability of LGD-4033. During this study participants were randomized to placebo,0,1.0,3 or 1mg LGD-4033 for 21 days. The study evaluated the safety, tolerability, pharmacokinetics and the effects of ascending doses of LGD-4033 on lean body mass, muscle strength, stair climbing power and sex hormones [39]. The sample size was still small and the study was not based on considerations of effect sizes, as the study’s primary aim was to establish safety and tolerability, rather than efficacy. Similarly, the 3-week study duration was not designed to demonstrate maximal effects on muscle mass and strength. Therefore larger and longer studies are needed to access the efficacy of LGD-4033. Furthermore the study was supported by Ligand Pharmaceuticals, who developed LGD-4033.

Ligandrol showed a dose-dependent suppression of total testosterone from baseline to 21 days, rather than an increase. Ligandrol did not result in fat loss in this study. It promoted muscle growth, but the evidence is very early weak evidence at this stage. There was an increase in lean body mass, that was doserelated. The mechanisms by which androgens increase muscle mass remain incompletely understood. However, the increase in strength measured by stair climbing speed and power also showed improvement, but not enough to be statistically significant. With a larger sample size and or longer study, it is possible that this effect may be demonstrated. LGD-4033 displayed an immediate effect on hormones in the body from the time it was taken. The research showed gains in lean muscle mass within the 21 days of the study. Adverse effects were not noted. LGD-4033 displayed a prolonged elimination half- life of 24-36 hours. Upon discontinuation of LGD- 4033 the hormone levels returned to baseline by day 56 [39]. There is just not enough research to show the efficacy of Ligandrol at this stage,despite it was safe and well tolerated at all doses administered.

Ostarine (MK-2866,Enobosarm)

Merck presented the results of a phase2 clinical trial evaluating Ostarine (MK-2866),an investigational SARM in patients with cancer induced muscle loss,also known as cancer cachexia at the Endocrine Society Annual Meeting in Washington in 2009 [40]. In this study 159 cancer patients with non-small cell lung cancer, colorectal cancer, non-Hodgkins lymphoma, chronic lymphocytic leukemia or breast cancer were randomized. Participants received placebo,1mg or 3mg Ostarine daily for 16 weeks. Average weight loss prior to entry was 8,8 percent and patients were allowed to receive standard chemotherapy during the trial. The drop-out rate during the trial was 33%.

Ostarine treatment led to statistically significant increases in lean body mass (LBM) and improvement in muscle performance measured by stair climbing in patients with cancer cachexia compared to baseline in both the Ostarine 1mg and 3mg cohorts. In the study Ostarine met the primary endpoint of LBM mesured by DEXA(dual energy x-ray absorptiometry) scan, by demonstrating significant increases in LBM compared to baseline in both the Ostarine 1mg and 3mg treatment was o,1kg(p=0,874 compared to baseline, 1,5kg(p=0,001) and 1,3 kg(p=0,0045) at the end of the 16 week trial.

The study also met the secondary endpoint of muscle function as measured by a 12 step stair climbing test measuring speed and calculating power with each Ostarine treatment arm demonstrating a statistically significant average decrease in time to completion and average percentage increase in power exerted.The change from baseline in stair climb power in the placebo,1mg,and 3mg treatment groups was 0,23 Watts (p=0,66,compared to baseline)8,4Watts (p=0,002) and 10,1 Watts (p=0,001),respectively. A critical appraisal results in the same critics,as depicted for the Ligandrol results. Ostarine is also known as Enobosarm and S-22 SARM by various licensing contracts in the body building world.

Ostarine had already shown significant improvement in the ability of healthy,elderly men and women to climb stairs in a phase2A study in 2007.Elderly men and women improved climbing stairs in speed and power,accompanied by significant increases in LBM and decreases in fat mass after only 86 days [41]. Enobasarm (GTx-024,Ostarine and S-22) is the most well characterized clinically and has consistently demonstrated increases in LBM and better physical function across several populations, along with a lower hazard ratio for survival in cancer patients. Enobosarm was eveluated in the POWER 1(Prevention and Treatment of Muscle Wasting in Patients with Cancer)and in the POWER 2 trial. These are the first phase 3 trials for a SARM. Full results from these studies will soon be published and will guide the development of future anabolic trials [42].

Andarine (S4)

Andarine(S4) was studied in 120 ovariectomized rats for 120 days. The study found that treatment with S4 (Andarine) was benificial to maintain cortical bone content and whole body and trabecular bone mineral density (BMD) measured by DEXA scan. The S4 treatment also decreased body fat and increased body strength in these animals. It was further disclosed by this study that S4 had the ability to reduce the incidence of fractures via minimizing the incidence of falls, through increased muscle strength and through direct effects on bone,as compared to current therapies that are primarily antiresorptive in nature. The study also found that dosages of S4 were effective to increase LBM and reduce body fat in intact and ovariectomized rats. It was also revealed that Andarine provides the unique potential to prevent bone resorption, increase skeletal muscle mass and strength positions and promotes bone anabolism, that makes it a possible new alternative for the treatment of osteoporosis [43]. To date there are no clinical human studies of Andarine in osteoporosis.Andarine has a half-life of 4-6 hours and is prized for weight loss and building and repair of muscle as a muscle boosting supplement in the fitness community.

RAD 140 (Teslolone)

RAD 140 is a SARM that stimulates muscle weight increases at a lower dose than that required to stimulate prostate weight. It results in the expected lowering of lipids (LDL,HDL,triglycerides),without elevation of liver enzyne transaminase levels.RAD 140 has excellent pharmacokinetic properties and is a potent anabolic [44]. RAD 140 is a potent AR agonist in breast cancer cells with a distinct mechanism of action,including the AR-mediated repression of estrogen receptor1 (ESR1).It inhibits the growth of multiple AR/ ER+ breast cancer PDX (patient –derived xenograft) models as a single agent,and in combination with palbociclib.These preclinical data present support for further investigation of RAD 140 in AR/ ER+ breast cancer patients [45].

RAD 140 is a SARM that stimulates muscle weight increases at a lower dose than that required to stimulate prostate weight. It results in the expected lowering of lipids (LDL,HDL,triglycerides),without elevation of liver enzyne transaminase levels.RAD 140 has excellent pharmacokinetic properties and is a potent anabolic [44]. RAD 140 is a potent AR agonist in breast cancer cells with a distinct mechanism of action,including the AR-mediated repression of estrogen receptor1 (ESR1).It inhibits the growth of multiple AR/ ER+ breast cancer PDX (patient –derived xenograft) models as a single agent,and in combination with palbociclib.These preclinical data present support for further investigation of RAD 140 in AR/ ER+ breast cancer patients [45].

In the fitness community Testolone is seen as one of the latest additions to the line of SARMs. Testolone is developed by Radius Health Company. The increase in LBM and fat loss are highly appreciated, as its androgenic-anabolic ratio of 90:1, compared to testosterone. Recommended dosages of Testolone vary from 20- 30 mg once daily and it is used in cycles of 12-14 weeks duration. Because Testolone does not interact with the aromatase enzyme and is not liver toxic, no adverse effects are claimed. The half-life of Testolone is estimated 12-18 hours.

Cardarine(GW 501516) and SR 9009 (Stenab0olic)

These two preparations are usually grouped with the SARMs in the fitness community, but are not the same. Cardarine is used as an enhancing running endurance supplement. Cardarine is not a SARM, but a peroxisome proliferative activated receptor-omega agonist (PPAR-omega), that increases PPAR-omega, and regulates muscle metabolism and reprograms muscle fibre types to enhance running training endurance. While training alone increases the exhaustive running performance Cardarine treatment enhances running endurance and the proportion of succinate dehydrogenase(SDH)- positive muscle fibres in both trained and untrained mice. It appeared while training increases energy availability by promoting protein catabolism and gluconeogenesis, Cardarine enhances specific consumption of fatty acids and reduces glucose utilisation [47]. In the fitness community Carderine is regarded as”king of the gym”. Half-life is between 16-24 hours and it should be taken at 10 mg once a day or twice daily. It is claimed to be useful in conjunction with anabolics and stimulants of any kind without adverse reactions in 12-14 week cycles.

SR 9009 (Stenabolic) is a REV-ERB (revised-viral nuclear erythroblastosis receptors) agonist, that can modulate the expressions of circadian core clock proteins and therefore help to modulate the circadian rythm. Modulation of the REV-ERB activity by synthetic agonists e.g., SR 9009 SR 9011 alters the expression of genes involved in lipid and glucose metabolism and, therefore plays an important role in maintaining the energy homeotasis. Effects of SR9009 and SR9011 in animal studies are increased basal oxygen consumption, decreased lipogenesis, cholesterol and bileacid synthesis in the liver, increased mitochondrial content, glucose and fatty oxidation in the skeletal muscle and decreased lipid storage in the white adipose tissue. The observed increase in energy expenditure and decrease in fat mass make the REV-ERB agonists promising drug candidates for the treatment of several metabolic disorders.They are also attractive for performance enhancement by athletes. Such use can be classified as doping [48].

SR9009 (Stenabolic) has been developed by Scripps Research by the team of Prof. Thomas Burris. Stenabolic is taken orally as a metabolism enhancer in the fitness community. It is believed to have results similar to Cardarine, but with considerable more extra benefits. It is recommended as a very good addition to any steroid (Anavar or Trembolone) or SARMs cycle, especially when used together with Cardarine. The half-life is short, 30-60 minutes,so the dose should be spaced through the day e.g.,10 mg 4-6 times daily. Again no adverse effects are reported.

Illicit use of SARMs

Recently, the FDA issued a consumer warning letter against supplement-like bodybuilding products,that contain SARMs. The FDA warning came on the heels of warning letters sent to three companies, that market products containing the ingredients. FDA had this to say about the offending products distributed by Infantry Labs LLC,Iron Mag Labs and Panther Sports Nutrition: “ Although the products identified in the warning letters are marketed and labeled as dietary supplements, they are not dietary supplements. The products are unapproved drugs, that have not been reviewed by the FDA for safety and effectiveness” [49]. FDA told consumers among the dangers associated with SARMs are liver toxicity and the potential to increase the risk of heart attack and stroke.But the agency said the long- term effects of these substances are unknown. However, these FDA health risk statements can not be supported by the few small clinical human phase 1 and2 SARMs studies performed and the ongoing POWER trials. Furthermore, the FDA did not mention that Ostarine and Ligandrol have previously been investigated as new drugs, which makes them ineligible for use as dietary supplements.

Nevertheless, as clinical research of SARMs is slow, we are now in the wonderful situation the real world clinical SARMs experience is now represented by the fitness and body building world. It is estimated that ther are between 2 and 4 million young people in the U.S. alone, who have used performance-enhancing drugs sometime in their life. There are thousands of internet sites offering SARMs in and outside the U.S [50]. So the magnitude of the problem is completely unknown,if there is any problem at all. In general,these young people are very concerned about their health and “looks” and have the good right of their own responsability.

A recent JAMA publication found that the chemical analysis of 44 products sold via the internet as SARMs revealed, that only 52% contained SARMs and another 39% contained another unapproved drug. In addition, 25% of products contained substances not listed on the label, 9 percent did not contain an active substance and 59% contained substance amounts,that differed from the label [50]. Although these figures must be frightening,there is no registered SARMs epidemic at the U.S. emergency rooms. At present the biggest problems are the “loopholes” in the FDA regulation of dietary supplements.

Conclusion

The SARMs were discovered in the late 1990’s. Clinical development is slow. Few human phase 1 and 2 clinical studies are available Results of the phase 3 POWER trials,studying SARMs in wasting, are awaiting and will guide the development of future anabolic trials. Until now no SARM has received FDA approval. Due to “loopholes” in the FDA regulations the SARMs are widespread used as dietary supplements in the fitness community and body building world. This results in the wonderful situation the clinical experience with SARMs is represented by illicit SARMs use and not by clinical science.

Read More About Lupine Publishers Journal of Reproductive System Please Click on Below Link:
https://lupine-publishers-reproductive.blogspot.com/

Friday, 20 August 2021

Lupine Publishers | Contrast-Induced Nephropathy: Current practice

 Lupine Publishers | Journal of Urology & Nephrology


Abstract

Contrast induced nephropathy (CIN) is a common cause of hospital acquired acute kidney injury (AKI) and associated with adverse clinical outcomes. There is still debate regarding the exact definition, which has greatly influenced the reported incidence of CIN in literature. Recent studies have challenged the universal concern regarding risk of CIN in general population. It is found to occur more commonly after intra-arterial (IA) administration of contrast as in interventional cardiology and vascular procedures especially in patients with multiple comorbidities and underlying renal impairment. Recent studies report negligible risk after intravenous (IV) contrast administration for modern diagnostic radiological examinations. Since it is a potentially preventable clinical condition, it is imperative for health care professional to be well aware of this entity. All patients undergoing iodinated contrast exposure should be risk stratified and preventive measures should be employed in high risk population. This paper will review the epidemiology, controversies regarding definition, pathophysiology, risk stratification, iodinated contrast commonly used in practice and preventive strategies.

Keywords: Contrast Induced Nephropathy,Iodinated Contrast Media,Acute Kidney Injury,Cardiac Angiography,Contrast Enhanced Computed Tomography

Abbrevations: CIN: Contrast Induced Nephropathy,AKI: Acute Kidney Injury,CM: Contrast Media,ICU: Intensive Care Unit,CECT: Contrast Enhanced Computed Tomography,PTCA: Percutaneous Trans-Luminal Coronary Angioplasty,ACR: American College of Radiology,AKIN: Acute Kidney Injury Network,eGFR: Glomerular Filtration Rate,NGAL: Neutrophil Gelatinase-Associated Lipocalin,CES: Cholesterol Embolism Syndrome,ERBP: European Renal Best Practice,KDIGO: Kidney Disease Improving Global Outcomes,NSAIDS: Non-Steroidal Anti-Inflammatory Drugs,HOCM: High Osmolar Contrast Media,LOCM: Low Osmolar Isosmolar CM,HD: hemodialysis,HF: hemofiltration,NAC: N-acetylcysteine,ESUR: European Society of Urogenital Radiology,CAR: Canadian Association of Radiologist,ESRD: End Stage Renal Disease,TOF: Time Of Flight,CKD: Chronic Kidney Disease,NSF: Nephrogenic Systemic Fibrosis,NCCT: Non contrast computed Tomography,CO2: Carbon Dioxide

Introduction

Contrast induced nephropathy (CIN) is defined as acute renal impairment after exposure to iodinated contrast media (CM). In the modern era with the advancement of the diagnostic modalities, increase in number of percutaneous coronary and peripheral artery interventions and frequent use of contrast media, CIN has emerged as a common cause of acute renal failure. Mostly, it results in transient renal impairment; however in patients with multiple comorbidities it can be associated with high morbidity and mortality [1]. It is therefore imperative to identify patients at risk to decrease its occurrence and diagnose it early in course to avoid short and long term clinical adverse effects. It presents a challenging situation that is often encountered by practitioners in varied specialties including emergency medicine, nephrology, cardiology, radiology and intensive care unit (ICU). Since CIN represents a form of acute kidney injury (AKI), which is potentially preventable, it is important that clinicians are well aware of this entity and understands the basic pathogenesis involved. The aim of this review article is to discuss pathogenesis of CIN, associated risk factors, different iodinated CM used in clinical practice and their effect on kidney, alternative diagnostic modalities and preventive measures.

Epidemiology

CIN remains an important cause of in-hospital AKI, accounting for approximately 11% of the total cases of AKI [1]. Literature on CIN mainly reports it to occur following exposure to iodinated contrast during coronary or peripheral angiography [1,2] or diagnostic imaging, however recent data shows contrast exposure associated with modern radiographic procedure is not associated with significant increase in CIN incidence [3]. Exposure following cardiac or peripheral angiography differs from that during diagnostic imaging in that the injection is intra-arterial, requires catheter and dose of CM is concentrated and abrupt [4,5]. In general population without any risk factor, incidence of CIN is very low; however risk increases as comorbidities increases [1,6,7]. Critically ill patients with baseline renal impairment are particularly susceptible and contrast enhanced computed tomography (CECT) might account for 18% of AKI cases in this population [8]. Reported incidence of CIN varies with the procedure and is reported to be 11% after outpatient CECT [9], 4% following intravenous pyelography [10], 9% after peripheral arteriography (4), <3% following percutaneous trans-luminal coronary angioplasty (PTCA) in patient with normal renal function and as high as 40% in patient with underlying renal impairment [2,11,12]. Studies have documented at least 3.1% of patients with CIN required renal replacement therapy. In hospital mortality is reported to be 7.1% in patients with CIN after coronary intervention and as high as 35.7% in patients requiring dialysis, which further increases to 81.2% at 2 year [1]. CIN is reported to be independent predictor of poor outcome in patients with diabetes mellitus with or without renal impairment [6].

Definition

Post- contrast acute kidney injury (PC-AKI) is often defined as acute renal impairment occurring within 48hours of exposure to intravascular iodinated CM. It is a correlational diagnosis and can occur irrespective of CM being cause of renal deterioration. In contrast, CIN comes under subgroup of PC-AKI and is a causative diagnosis. In literature, CIN has been defined as relative change in the baseline serum creatinine (> 25-50%) and absolute elevation from baseline serum creatinine (>0.5-2 mg/dL) [13- 15]. Temporal relationship between exposure to CM and rise in serum creatinine along with exclusion of other causes of AKI are crucial for the diagnosis of CIN. Defining set criteria for diagnosis is important as incidence of CIN in clinical practice can vary greatly with small change in serum creatinine. An absolute increase of serum creatinine by ≥0.5 mg/dL from baseline is still commonly used definition of AKI [16]. Another well-known criterion for CIN proposed by Barrett and Parfrey in early 1990s was an absolute increase in serum creatinine levels by ≥0.5 mg/dL or a relative increase of ≥25% in serum creatinine from baseline within 72 hours after contrast exposure [17]. However, for purpose of standardizing the definitions, recently American College of Radiology (ACR) has recommended using the AKIN (Acute Kidney Injury Network) criteria to define CIN. It employs absolute serum creatinine increase >0.3mg/dl or ≥50% (≥1.5 times) percentage increase in serum creatinine or ≤0.5 mL/kg/hour urine output for at least 6 hours within 48hours of exposure to define AKI [18]. In clinical practice, serum creatinine concentration is commonly used measure of renal function; however it has its own limitations. There is often delay between renal insult and rise of serum creatinine, which delays the diagnosis. It is also affected by other factors including age, gender, nutritional status, volume status, hyper catabolic state, muscle mass and concomitant use of other medications, therefore it is important to interpret results in appropriate clinical settings [19,20]. Changes in serum creatinine concentration are not linearly related to changes in effective glomerular filtration rate (eGFR,) because of which small changes in eGFR can often go unnoticed. Normal serum creatinine is actually maintained till GFR or creatinine clearance is reduced by nearly 50% [20].

Diagnosis

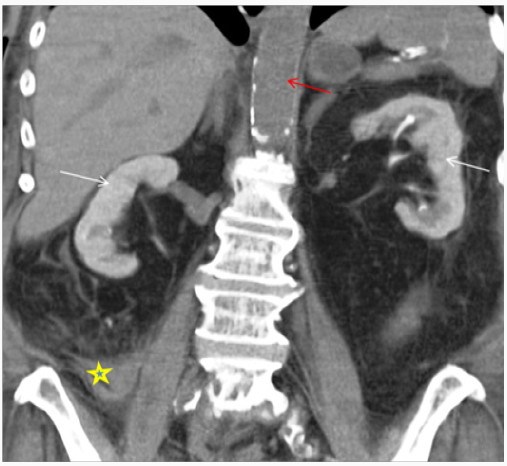
Diagnosing CIN is challenging. It is important to follow systemic approach while evaluating patient with AKI. CIN is a diagnosis of exclusion after other causes of AKI (prerenal/intrinsic/post renal) have been ruled out. There is temporal relationship with contrast exposure, however this should not preclude from searching for other reversible causes of AKI, which may coexist [13-15]. Periprocedural hypotension, bleeding, release of athero-embolic material and use of catheter exchanges may further complicate renal tubular injury after angiography [21]. After exposure to intravascular iodinated contrast, serum creatinine typically rises within the first 24-48 hours, peaks at 3-5 days and returns close to baseline within 1-3 weeks. In most cases, it is asymptomatic and has no significant clinical consequences. However, in rare cases it can lead to oliguria or anuria, irreversible renal damage and need for renal replacement therapy. Basic work up includes clinical assessment, urine output, urinalysis and renal imaging. Volume depleted state can predispose patient to CIN; however CIN can result in intrinsic renal injury with tubular necrosis in extreme cases. Finding on urinalysis may include muddy brown granular cast, tubular epithelial cells and minimal or no proteinuria. Urine examination is neither sensitive nor specific to diagnose CIN, however its usefulness is mainly to exclude underlying glomerular disease or acute interstitial nephritis [22]. Urine studies may show intrinsic renal injury picture with urine sodium < 10 mEq/L, fractional excretion of sodium <1% and urine osmolality <350 mOsm/kg. Persistent nephrogram (Figure 1) may be incidentally seen on follow up imaging because of delayed clearance of contrast [23].

Timing of serum creatinine rise after contrast exposure in literature has been reported to be 24-72hours. However, it is speculated that renal damage actually begins soon after exposure to intravascular iodinated contrast. In study by Ribichini et al. [24], it is reported that measuring change in serum creatinine from baseline within 12hours of contrast exposure significantly predicted occurrence of CIN and was associated with renal damage after 30days [24]. However, relying on serum creatinine for diagnosis of renal injury has its own limitation as discussed above, therefore finding of specific biomarkers that could predict early diagnosis of CIN is desirable. Recently, it has been proposed to classify these biomarkers into two group, namely, (1) reflecting change in renal function (e.g. cystatin C) and (2) representing renal damage {e.g. Plasma or urine neutrophil gelatinase-associated lipocalin (NGAL), interleukin-18} [25]. Briguori et al. [26] reported increase in levels of cystatin C ≥ 10% at 24 h after PTCA had 100% sensitivity and 85.9% specificity for the prediction of CIN [26].

Another condition often encountered after exposure to CM especially catheter related studies is cholesterol embolism syndrome (CES). It can be challenging to distinguish the two conditions clinically; however it is important as both have different treatment approach. CES is usually a rare entity and renal impairment typically develops gradually over 3-8weeks after the procedure. It is a multisystem disease caused by dislodgement of cholesterol crystals from atherosclerotic plaque and occlusion of peripheral arterioles. Other peripheral sign that can help clinch the diagnosis include live do reticularis, petechiae, digital gangrene, splinter hemorrhage and Hollenhorst plaques on ophthalmological examination. Laboratory studies may show peripheral eosinophilia, hypocomplementemia and high erythrocyte sedimentation rate. Spectrum of presentation is varied ranging from mild and asymptomatic to life threatening complications. CES is associated with significantly worse long term renal effects as compared to CIN and is suspected when multiple oral dysfunction occurs following coronary angiography [27].

Pathophysiology

Kidneys are particularly susceptible to ischemic injury in setting of delicate micro vascular circulation, which is particularly vulnerable to systemic and local hypo perfusion. Pathogenesis of CIN is multi factorial and still not completely understood. Interplay of factors including medullary hypoxia, oxidative stress, im balance of renal vaso constrictive and vaso dilatory mediators, changes in renal perfusion and direct tubular toxicity of CM has been suggested [28-30]. Two main mechanisms responsible are direct tubular toxicity of CM and changes in renal micro vascular hemo dynamics. Recently, high end diastolic pulmonary arterial blood pressure and left anterior descending artery lesion has been independently associated with development of CIN, pointing towards role of hemo dynamics and cardiac dynamics in its pathogenesis [31].

Effect of CM on Renal Tubules

CM is freely filtered from renal glomerulus and increases the tubular osmolality. It has direct cytopathological effects on tubular cells, which affects energy metabolism and impairs intracellular transport. Histopathologically, these changes consist of tubular cell vacuolization, necrosis and termed as osmotic nephrosis. There has been conflicting evidence to support precipitation of intratubular proteins triggered by CM. Actually it is proposed that CM induced cellular injury might be the inciting event responsible for CIN which triggers the cascade rather than hypoxia or hypoperfusion. Osmolality, viscosity and ionic properties of CM contribute to its nephrotoxicity. High osmolar CM have been shown to affect erythrocyte deformability, leading of stacking of blood cells and affecting blood flow in animal models. Another mechanism reported is mitochondrial dysfunction and release of catalytic iron, which serve as catalyst in oxidative reactions leading to production of free radicles [28-30].

Effects on Renal Microvascular Hemodynamics

Animal model have suggested that intra-arterial contrast infusion results in biphasic renal perfusion, with initial transient vasodilation followed by sustained prolonged vasoconstriction. Renal medullary perfusion and oxygen tension is lower than outer renal cortex under normal physiological state and thick ascending loop of henle in outer renal medulla has high oxygen requirement exacerbating relative medullary hypoxia. CM further aggravates this hypoxia by causing osmotic diuresis leading to increased sodium transport to thick ascending limb and subsequently increased oxygen extraction. Total medullary hypoxia is actually combination of increased oxygen demand of tubular cells and changes in regional renal microcirculation [32,33]. Subclinical CIN can occur in majority of patients following contrast exposure; however it goes undetected as healthy individuals have intact tubular repair mechanism that prevents clinically significant renal damage. In contrast, in patients with comorbidities like baseline renal impairment and diabetes mellitus even average dose of contrast can have clinical implications in setting of poor reparative mechanism and baseline reduced functional nephrons [34].

Risk Factors

Various risk factors have been described which increases the risk for development of CIN after exposure to iodinated CM. These can be broadly divided into intrinsic or patient related and external or procedural/contrast related. Among the patient related factors, baseline renal impairment (GFR < 60 mL/min per 1.73 m2) and diabetes mellitus are the two important independent risk factors that are commonly coexisting in vascular patient population [7,35]. However, recent analyses by McDonald [16] and Davenport et al. [36] have found increased incidence of CIN in diabetes only if renal function is compromised (GFR < 30 mL/min/1.73 m2) [16,36]. Studies have reported significant risk for CIN if baseline serum creatinine concentration is ≥1.3 mg/dL in men and ≥1.0 mg/dL in women, mostly equivalent to an eGFR <60 mL/min/1.73 m2 [37]. In light of recent studies, European Renal Best Practice (ERBP) along with Kidney Disease Improving Global Outcomes (KDIGO) guidelines suggest that the threshold at which actual risk for CIN increases could be lowered to 45 mL/min/1.73 m2 [38]. Other established risk factors include advanced age (≥70 years), dehydration, anemia, vascular disease, hypertension, coronary artery disease, congestive heart failure, smoking and concomitant use of other medications including metformin, non-steroidal anti-inflammatory drugs (NSAIDS), diuretics or calcium channel blockers.

It was long thought that patients with multiple myeloma have increased risk CIN secondary to precipitation of myeloma proteins in the renal tubules. However, recent studies propose that contrast studies can be safely performed in myeloma patients with normal renal function provided there is no dehydration. Also, studies have reported acute urate nephropathy in patients with hyperuricemia, particularly leukemic patients on chemotherapy, secondary to uricosuric property of CM, however recent studies have failed to show independent association between the two [21,39]. Extrinsic or contrast related factors includes type of CM, route of administration, dose of CM and numbers of contrast exposure. Procedure related factors may include urgent or emergent procedure, use of intra-aortic balloon pump, delayed reperfusion and nature of procedure [12,21,39]. Various risk scoring have been proposed to stratify the risk for CIN. One of them reported by Mehran et al. [6] included eight variables namely age > 75 years, anemia, hypotension, diabetes mellitus, chronic congestive heart failure (CHF), acute pulmonary edema, chronic kidney disease, use of intra-aortic balloon pump and increase volumes of CM. Total risk score ≥ 16 was associated with 57% risk of CIN with 13% of patient requiring dialysis [40]. Another simple risk scoring, which has shown to have clinically significant predictive value for CIN, is ACEF score. It uses three variables, namely age, creatinine level and ejection fraction and has been developed for patients undergoing coronary angiography [41,42].

Iodinated CM

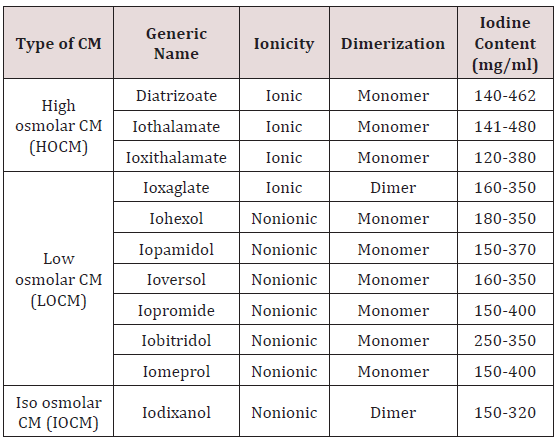
Type of Iodinated CM: Commonly available CMs are benzoic acid derivatives with three iodine atoms. High osmolar CM (HOCM), with osmolality up to eight times that of plasma were frequently used in past and had higher incidence of CIN. To decrease the osmolality, several approaches were considered including production of non-ionic agents, which resist dissociation in solution or by producing double benzoic acid rings. Low osmolar (LOCM) and isosmolar CM (IOCM) are commonly used nowadays and associated with low nephrotoxicity [43]. (Table1) descries the properties of CM. The adverse effect of CM is mainly related to its osmolality, ionicity, viscosity and iodine content. Viscosity instead of osmolality is responsible for vascular resistance [44]. Though IOCM has lower osmolality, because of its dimeric structure it has more viscosity than LOCM. There are conflicting results in studies comparing LOCM with IOCM and in most, no difference was found with respect to renal safety [45]. KDIGO guideline recommends use of LOCM or IOCM instead of HOCM however due to lack of data, there is no recommendation regarding preference of IOCM over LOCM [46]. However, CIN Consensus Working Panel recommends use of nonionic IOCM in patients with high risk for CIN undergoing coronary angiography, whereas IOCM or LOCM can be used for intravenous administration of contrast [47]. The current Canadian Association of Radiologists (CAR) consensus recommends use of CM depending upon route of administration of contrast and renal function; LOCM or IOCM should be used if eGFR < 45 mL/min for intravenous exposure and GFR < 60 mL/min for intra-arterial CM studies [48]. Many radiology department now-a-days uses IOCM in high risk patient population, especially with severe renal impairment with eGFR < 30 mL/min. Local hospital protocols based on guidelines can be used to decide between IOCM and LOCM.

Table 1: Properties of contrast media (information taken from manufacturer manual).
lupinepublishers-openaccess-journal-urology-nephrology

Dose of CM: A number of studies have shown contrast volume to be independent risk factor for subsequent development of CIN after coronary or peripheral angiography [39]. Both volumes of contrast and iodine content needs to be carefully considered taking in account renal safety and optimum imaging. Iodine content is important determinant of image enhancement and degree of attenuation achieved. Iodine content for most of the commonly used contrast ranges from 300 to 370mg/ml. Low dose of CM defined as <30-125ml or <5mg/kg, is less nephrotoxic and associated with lower risk of CIN. However, AKI can even occur with small (30 mL) volumes of iodinated CM, ruling out threshold effect. Some reports suggest performing staged angiography particularly when large volume of contrast use is anticipated, however this is solely dependent on clinical situation [39,43]. Brown et al.[49] proposed formula and use of “maximal allowable contrast (MAC) dose” (contrast volume limit [ml = 5 × body weight {kg}]/ [88.4 × SCr {μmol/l}]), which correlated, with development of CIN [49]. Whenever possible lowest dose of contrast should be used by incorporating MAC as a part of pre-procedure contrast ‘Time-Out’; especially in patients with high risk factors when other alternative modalities cannot be used.

Route of Administration: This is procedure dependent. Intraarterial (IA) injection of iodinated contrast is associated with higher risk of CIN compared to intravenous (IV) administration. Proposed mechanism behind greater risk after IA exposure is amount of contrast directly reaching kidneys if contrast is administered directly in abdominal aorta or renal arteries. Risk is less if contrast is given below origin of renal arteries and minimal risk after IV administration [4,43]. Recent studies by McDonald et al. [16] and Daveport et al. [36] using “propensity matching” as statistical tool in order to compare incidence of CIN in patients who received IV contrast for CECT to control group, found that occurrence of CIN in this population is rare and if it occurs it happens in patients with baseline severe renal impairment (eGFR<30ml/min/1.73 m2) [16,36].

Repeat Contrast Exposure: Multiple dose exposure of contrast within short period of time is well-documented risk factor for CIN [40,43,50]. It is believed that at least 24 hours interval should be considered between two contrast exposures as it takes approximately 20 hours to eliminate contrast from the body, provided patient has normal renal function. Guitterez et al. [51] demonstrated renal impairment may persist for 10 days after contrast exposure and duration of renal impairment is dependent on baseline renal function. Therefore, repeat exposure should be delayed in patients with chronic kidney disease to allow time for renal recovery [51].

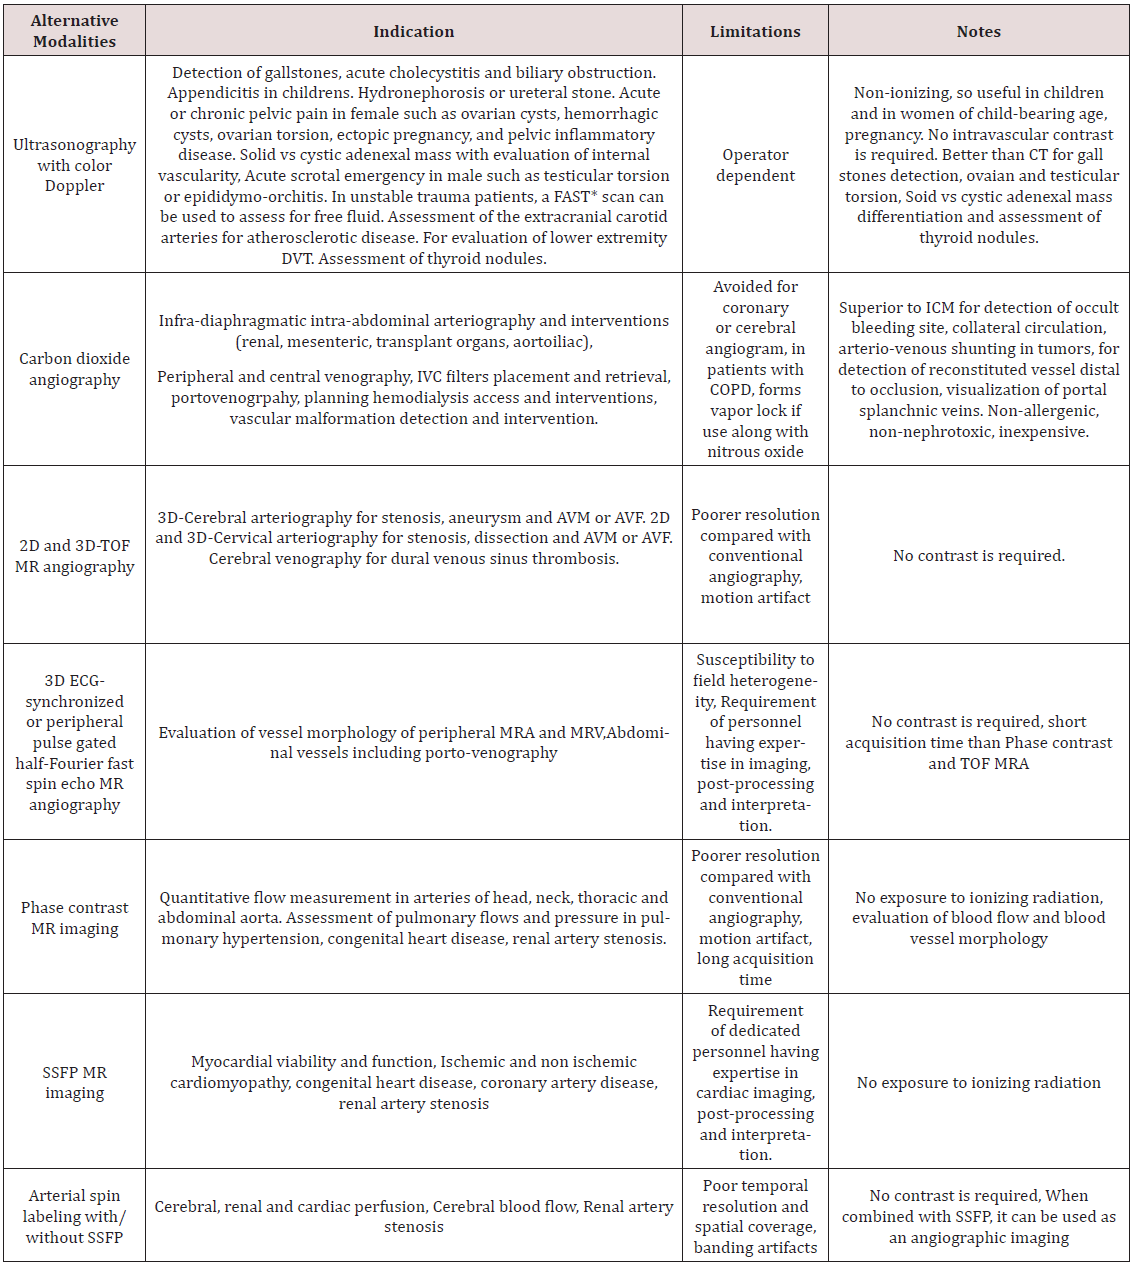
Alternative Imaging Modalities to Prevent CIN: In patients with high risk for CIN, alternative imaging modalities should be chosen after proper risk benefit discussion with the patient. Though contrast enhanced imaging have its own advantages particularly for the diagnosis of inflammatory/ infectious disease and neoplastic conditions as well as diagnosis and treatment of vascular diseases, it is important for the clinicians to be well aware of alternative modalities like ultrasonography, carbon dioxide (CO2) angiography and magnetic resonance imaging (MRI) with or without gadolinium (Table 2). In patients at risk for CIN every effort should be made to avoid iodinated contrast if possible. Non contrast computed tomography (NCCT) is preferred for diagnosis of intracranial hemorrhage, fracture or dislocation and interstitial lung disease [52].

Non contrast MRI [53] including Steady-state free precession MRI (SSFP), Phase contrast MRI, time of flight (TOF) MR angiography should be employed in appropriate setting as described in (Table 2). Gadolinium based contrast agents can be used in patients at risk of CIN, however it is best avoided in patients on dialysis and with severe renal impairment especially chronic kidney disease (CKD) Stage 4 and 5 for concerns of nephrogenic systemic fibrosis (NSF) [54,55]. CO2 angiography is another useful modality often used in various diagnostic and therapeutic interventions when exposure to CM must be avoided to prevent CIN or patient is allergic to iodinated contrast [56]. It is highly soluble, non-allergic, inexpensive and readily available gas with low viscosity relative to blood. For some procedures, CO2 angiography is actually superior to conventional CT including better visualization of collateral circulation, enhanced vascular filing in central venography, detection of AV shunting in tumors and detection of occult GI bleeding. It can be used in patients with chronic lung disease with caution if sufficient time is allowed for elimination of gas from the body. However, it has some limitations as well. It is preferably used for infradiaphragmatic arteriography due to concerns of neurotoxicity. Other complication limiting its use is vapor lock or air trapping which increases with simultaneous use of nitrous oxide. Another limitation for its use is cumbersome delivery system and risk of error of measurement of vessel size, which is dependent on injection technique [56].

Table 2: Alternative non-iodinated contrast and non-contrast diagnostic imaging modalities.
lupinepublishers-openaccess-journal-urology-nephrology

*FAST: Focused Assessment with Sonography for Trauma.

DVT: Deep Venous thrombosis.

TOF: Time of flight.

ICM: Intravascular contrast medium.

SSFP: Steady state Free Precision.

Special Consideration With Use of Iodinated CM:

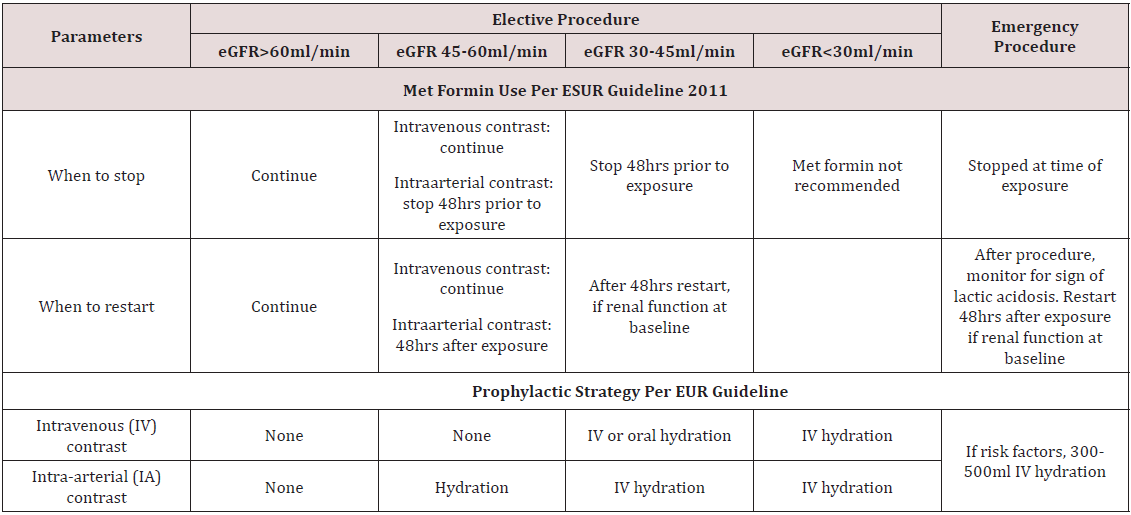
a) Met Formin Use: Metformin has not been recognized as independent risk factor for developing CIN, however serious complications like lactic acidosis can rarely develop in patients on metformin, if they subsequently develop AKI after contrast exposure. Whether it should be stopped in all patients anticipating contrast exposure or only in patients with underlying renal impairment and how earlier it should be stopped is still matter of controversy. The monogram for Glucophage (metformin) recommends that it should be discontinued at the time of or before the procedure in all patients, withheld for at least 48 hours subsequent to the procedure, and restarted only after confirmation of normal renal function [57]. The European Society of Urogenital Radiology (ESUR) (Table 3) and Canadian Association of Radiologist (CAR) consensus recommends holding metformin at the time contrast exposure in patient with normal renal function and 48 hours before in patients with preexisting chronic kidney disease [48,58]. However, ACR recommends withholding it for 48hrs before exposure only in patients with marked renal impairment (eGFR ≤ 30 mL/min/1.73 m2) or undergoing intra-arterial catheter studies and no need to discontinue or withhold if eGFR > 30 mL/min1.73 m2) [59].

Table 3: Preventive strategy to lower the risk of CIN as per EUR guideline 2011.
lupinepublishers-openaccess-journal-urology-nephrology

b) End Stage Renal Disease (ESRD): Patient with ESRD on dialysis usually do not have functional kidneys and can receive intravascular contrast material without further risk of renal damage, however studies have speculated conversion of oliguric patient to anuria. Other consideration is risk of pulmonary edema and fluid overload after osmotic load, though it was reported in past when HOCMs were frequently used. However, whenever possible LOCM should be used as they are not protein bound and have low molecular weight and can be cleared by dialysis. Usually urgent dialysis is never indicated after CM in this population unless there is exposure to large volume of contrast and patient develops life threatening pulmonary edema or cardiac arrhythmia [60].

c) Screening baseline renal function: It is actually general practice to screen baseline renal function prior to contrast exposure; however it can lead to diagnosis or procedural delay, increase financial cost and patient discomfort. ACR recommends to screen renal function (e.g., serum creatinine, eGFR) prior to exposure to iodinated CM in only selected patients with high risk factors including age >60 year, patient with history of renal disease, renal cancer, renal surgery, patient on dialysis, patients with single kidney, hypertension on medical therapy and diabetes mellitus. Patient who do not have above-mentioned risk factors and require routine intravascular contrast do not require routine screening [61,62]. Choyle et al. [62] listed few risk factors (preexisting renal dysfunction, hypertension, gout, proteinuria and prior renal surgery) and found that if none of these factors are present 99% of patients had serum creatinine levels less than 1.7mg/dl and 94% of patients had normal renal function [62]. However, ERBP guidelines recommend measuring baseline serum creatinine in all patients before an intervention and repeat levels 12 and 72 hours after contrast administration in high-risk patients [38]. The decision to repeat serum creatinine after procedure is a matter of debate. According to ESUR, renal function after contrast exposure should be assessed in 3 days, however some studies have documented that in certain patient populations particularly with diabetes mellitus and chronic kidney disease peak rise in creatinine levels is actually delayed, which demands prolonged renal function survey [58,63].

Prevention of CIN

There has been number of preventive measures to reduce incidence of CIN in high- risk population, however there is no clear consensus and current evidence remains inconclusive [64,65]. However, it has been agreed that identification of highrisk population is the foremost. Once this population is identified, best attempt should be done to minimize renal injury by stopping other nephrotoxic medications particularly NSAIDS, loop diuretics and met formin at least 24-48hours prior to contrast exposure particularly if IA exposure is anticipated and in patients with baseline severe insufficiency [47,57,58]. Unfortunately, in emergent procedures it might not be possible to stop medications or delay the procedure, however when possible restarting the nephrotoxic medication should be delayed for at least 48 hours after or as deemed clinically appropriate (Figure 1).

Figure 1: 68-year-old female with drop in hemoglobin status-post cardiac catheterization one day ago. Non-Contrast enhanced CT Abdomen demonstrating persistent nephrogram phase of enhancement from prior cardiac catheterization due to contrast induced nephropathy. Note hyperdense collection suggestive of an acute hematoma extending adjacent to RIGHT psoas muscle (*) lateral to the RIGHT psoas muscle continues with RIGHT iliac vessels, likely cause of drop in hemoglobin. Red arrow depicting no intra-vascular contrast media in the current study.
lupinepublishers-openaccess-journal-urology-nephrology

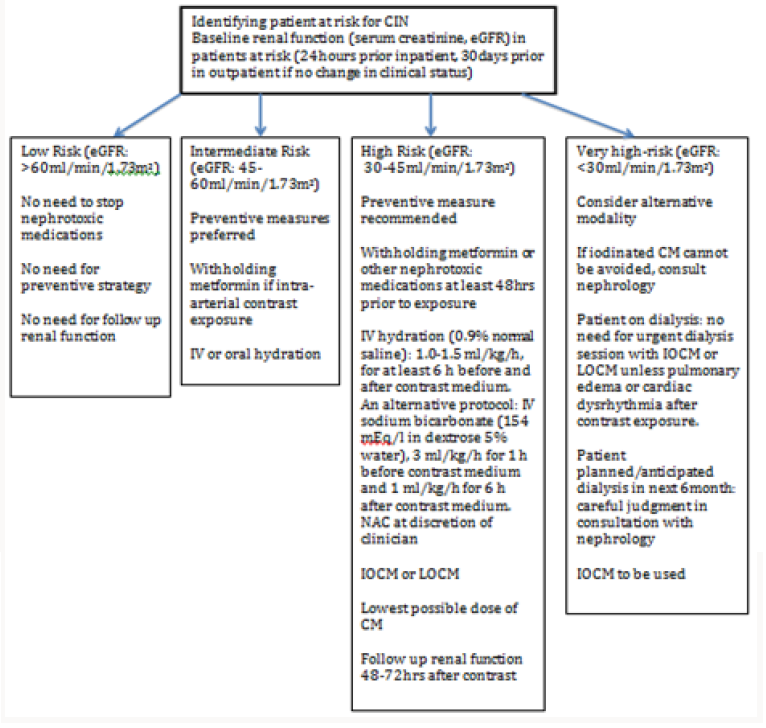
Figure 2: Flowchart for Risk stratification and preventive measures.
lupinepublishers-openaccess-journal-urology-nephrology

The cornerstone of practice to prevent CIN remains volume expansion. It is low-risk practice and carries few complications. Randomized trials have documented effectiveness of IV hydration with normal saline in the prevention of CIN. It should be given in all risk categories, particularly patients with an estimated GFR <60 ml/min/1.73 m2. It is postulated to promote diuresis, increase intravascular volume, induce vasodilation and suppress renin aldosterone axis. However, there is no fixed regimen and in general, starting it well before exposure and continuing even after procedure is the best practice. Oral volume expansion has shown some benefit, however evidence does not support it to be as effective as IV volume expansion. For isotonic saline administration, most studies suggest that 0.9% saline should be started at a rate of 1-1.5 mL/kg/h 3-12 h before and 6-12 h after contrast media exposure [66,67]. IV administration of sodium bicarbonate has also been studied for prevention of CIN; however recent data have shown conflicting and mixed results. The theoretical benefit of sodium bicarbonate is alkalization of tubular fluid and reduced production of free oxygen radicals, along with volume expansion. Most studies have suggested that it should be started at a rate of 3 mL/kg/h 1 h before and 1 mL/ kg/h for 6 h after contrast exposure. Though some studies have documented its beneficial effects, they have been critiqued for being single center, non-blinded and small studies [67,68].

N-acetylcysteine (NAC) also gained popularity for use to prevent CIN. It is believed to be direct free radicals scavenger, which improves blood flow through nitric oxide-mediated pathways. Its antioxidant and vasodilator actions are believed to protect against CIN. As compared to IV saline alone, low-dose NAC along with IV saline has shown significant decrease in CIN in patients receiving either IA or IV contrast. It is commonly employed agent in clinical setting in patients at high risk because of high tolerability, low cost, potential cardio protective properties, even in absence of clear scientific evidence. KDIGO 2012 guideline recommends using oral NAC with IV fluids in patients with high risk of CIN in setting of its low risk profile [38,69]. Algorithm showing preventive measures to be taken is shown in (Figure 2) Various other experimental pharmacologic agents have been studied for CIN prophylaxis including statin, ascorbic acid, tocopherol, dopamine, fenoldopam, theophylline, nebivolol, atrial natriuretic peptide and prostaglandin, however none of them have achieved clinical significant results [70]. Also, no beneficial effect of experimental procedures such as hemo filtration (HF) and prophylactic hemodialysis (HD) was found against CIN [71]. Moreover, prophylactic HD was found to be associated with increased CIN [71]. New investigational study ‘Renal guard system’ which is a fluid management device seems promising except for concern of electrolyte abnormalities and additional studies are needed before renal guard system can be implemented clinically [72,73].

Clinicians should be well aware of CIN, which is potentially serious entity. Since there is no established treatment for CIN, every effort should be taken to prevent it from occurring by recognizing at risk population, weighing risk-benefit ratio in all patients, optimizing volume status prior to contrast exposure, avoiding simultaneous use of other nephrotoxic agents, using newer generation of CM and using lowest possible dose.

Conclusion

Clinicians should be well aware of CIN, which is potentially serious entity. Since there is no established treatment for CIN, every effort should be taken to prevent it from occurring by recognizing at risk population, weighing risk-benefit ratio in all patients, optimizing volume status prior to contrast exposure, avoiding simultaneous use of other nephrotoxic agents, using newer generation of CM and using lowest possible dose.

Read More About Lupine Publishers Journal of Urology & Nephrology Please Click on Below Link:
https://lupine-publishers-urology-nephrology.blogspot.com/

Thursday, 19 August 2021

Lupine Publishers | Commentary: Pediatric Asthma Management in the Kingdom of Saudi Arabia: The Need for Culturally Sensitive Research and Practice

 Lupine Publishers | Journal of Clinical & Community Medicine


Abstract

Asthma is the third most common chronic disease in Saudi Arabia, affecting two million people. Asthma is also a leading cause of death among allergic disorders. Uncontrolled asthma may considerably decrease the quality of life for children and their families. Over the years, the Saudi government has included asthma as a major concern in their strategic health plan and has encouraged research in this area. However, paediatric asthma management remains under-researched and needs to be investigated further in the Saudi context. This review summarizes the recent advances in the paediatric asthma management in Saudi Arabia, including the need for culturally sensitive research and practice. The authors discuss the recent context of asthma management in KSA. The authors discuss the need for culturally and ethnically sensitive asthma management research and practice.

Keywords: Asthma; Management; Children; Saudi Arabia; Culturally sensitive care

Introduction

Asthma is a potentially life-threatening condition and is one of the most common respiratory problems causing lung airway obstruction [1]. It is a disease which has no cure but can be controlled by use of proper medication and effective selfmanagement through education [2]. In 2010 an estimated 300 million people were currently asthmatic globally [3]. Poor control of asthma may also lead to frequent use of emergency departments, hospitalization, and, in severe cases, death. Despite several decades of advances in its control and management, asthma remains a common worldwide health and socio-economic problem [4].

Approximately 1.4 million children aged 2-15 in the UK are currently receiving treatment for asthma [5]. In the US, nine million children aged under 18 years have asthma [6]. Asthma is an increasingly significant child health problem within the Kingdom of Saudi Arabia (KSA). Although the prevalence rate of asthma among Saudi adults is unknown, estimations by the Saudi Initiative for Asthma (SINA) [7] placed the overall prevalence rate among Saudi children between 8-25 % in 2012 [8]. The prevalence of lifetime wheeze, wheeze over one year and physician-diagnosed asthma in children have been reported as 25.3%, 18.5% and 19.6%, respectively [9]. According to international statistics, in 2016 it is estimated that the Saudi population will comprise 29.4% citizens aged under 15, and 67.6% aged 15-64. This indicates that paediatric asthma continues to be a major public health concern in KSA, especially as asthma control for many patients remains suboptimal. For example, a recent asthma control survey conducted in KSA showed that only 5% of child and adult patients were controlled, 31% were partially controlled, and 64% were uncontrolled [10].

Another recent cross-sectional study conducted among children with asthma aged 4-11 years revealed that uncontrolled asthma was present in about 59.3% of children [11]. This situation has considerable consequences for children in reducing their quality of life through increased hospitalisations and emergency visits [12]. For children, uncontrolled and poorly managed asthma also results in frequent school absences, affecting their educational attainment and future employment prospects and general life outcomes, including health [13].

The Context of Asthma Management in KSA

Internationally, achieving effective asthma management can be challenging for health professionals for a range of reasons, including under-diagnosis, lack of patient education, poor health facilities and limited treatment choices [14-15]. Such issues make asthma management even more challenging in KSA. For example, although there are available written protocols for the diagnosis and management of asthma in the country, there is still inadequate knowledge and application of these guidelines among health care providers [16-17]. Overall, the level of awareness of general knowledge, diagnosis, classification of severity, and management among physicians is considered average (52%), while that of other health professionals in general is considered low [7].

A shortage of Saudi healthcare professionals means that KSA has long employed doctors and nurses from other countries, resulting in the majority of healthcare professionals in KSA being expatriates. There are also issues in KSA which make the professional management of asthma more challenging. The Saudi Ministry of Health (MoH) for example reported that only 38% of its total health workforce were Saudis [18]. The use of health professionals from other countries contributes to high employee turnover rates and can cause barriers during clinical consultations, as foreign professionals usually lack Arabic language skills to communicate with children and parents [19-20].

In many other countries, including the UK and USA, asthma management services are provided by doctors and nurses working collaboratively. Nurses have an active role in the long-term asthma management and education of patients [21], but this is not the case in KSA where nursing staff typically have a negligible, ad hoc role in asthma management [8]. As the role of nurses in asthma care in KSA is under-developed, the burden of asthma management in Saudi therefore primarily falls on doctors rather than being shared with nurses. In recognition of this medical load, and the need to develop asthma care, SINA asthma guidelines were introduced in 2009 to mirror other national and international guidelines like GINA and NAEPP [8,22-23], particularly highlighting the importance of good asthma education [7].

One of the specific challenges of providing effective paediatric asthma management in the KSA is inadequate awareness of the condition. An estimated 50% of the populations of the major Saudi cities of Riyadh Jeddah and Dammam do not know asthma symptoms [24]. Public awareness campaigns regarding asthma, its symptoms, medications, and consequences are urgently required in KSA with specific initiatives targeted towards parents of children with asthma, because parental lack of asthma knowledge is likely to contribute to delays in children accessing health services and receiving asthma treatment which may lead to higher morbidity and mortality rates [13]. To that end, an on-going, nationally funded nurse-led research is being conducted to enable nurses working in KSA to better support doctors in the management of asthma by becoming more involved in the provision of pediatric asthma education, which requires more information about the current nursing role in this field and how it can be improved.

In addition to these contextual barriers to effective paediatric asthma management in KSA, there is also a lack of asthma research specifically conducted in the country. Saudi studies have tended to investigate asthma control or drug use using quantitative methods such as surveys, but rarely cohort designs [12,25-26]. Most Saudi asthma research has focused on the prevalence of asthma among children [4,9,27-28], investigating relationships between asthma and other factors including triggers and symptoms [29-31] and assessment of risk factors [27,32-34]. For instance, there has been a lack of research evaluating asthma management interventions, including the delivery of asthma education programmes for children and parents and their outcomes within a Saudi context. It can be argued that some of the risk factors could be avoided by providing children with sufficient education about asthma. Therefore, there is a need in KSA to educate children with asthma about their illness and to test the effectiveness of these educational programmes in the Saudi context.

The Need for Culturally and Ethnically Sensitive Asthma Management Research & Practice

In recent years recognition has been growing of the need to provide asthma care that is sensitive to the cultural and ethnic needs of patients and parents [35]. A systematic review on barriers and facilitators to asthma management in the care of South Asian children identified some key ethnic and cultural issues, including the impact of parental and professional knowledge and beliefs, health service utilization pattern explanations and the impact of prejudice and stigmatization on the improving of asthma management, and language barriers [36]. In the UK, substantial ethnic variations in hospital admission and deaths from asthma have been noted in Scotland [37]. Cultural factors, including selfmanagement and health seeking behavior as well as variations in the quality of primary care provision, are the most likely explanations for these differences. Such leading research on culturally sensitive care focuses on countries like the UK and USA, where Arabic patients/parents are an ethnic minority. However, in countries like KSA it is necessary to conduct quantitative research on asthma outcomes (e.g. to determine whether non-Saudi health professionals communicating in English to Arabic children/ parents have the same outcomes such as hospital admission rates as Saudi professionals who speak Arabic). While the vast majority of the indigenous population are Arabic nationals, asthma services and management are often provided by health professionals recruited from other countries. Even where foreign personnel are Arabic native speakers (e.g. Egyptians and Palestinians), these professionals may have differing beliefs and values to their Arabian patients and may also lack knowledge about Saudi culture.

Culturally and ethnically sensitive asthma care is also needed for general care purposes, so professionals do not misinterpret extraordinary behavior as Saudi social norms [38]. Asthma management advice and recommendations offered by some professionals may also not fully reflect Islamic beliefs and values, decreasing compliance among clients. When health professionals and patients belong to different cultures, culture based misunderstandings can influence their relationships and interactions adversely [39]. The structure of society and families may be another factor preventing culturally specific pediatric asthma care in KSA. In Saudi Arabia there are no laws in place defining a minimum age of children, although numerous drafts for possible laws and regulations have been created since 2011 [40]. For instance, children under 12 years old are seen in children’s hospitals, whereas children above 12 years are treated in adult hospitals.

The Royal College of Pediatrics and Child Health (RCPCH) in the UK advocates that young people need special support to manage their long-term condition, with emphasis on developing positive health behaviors that continue into adulthood [41]. This is in line with the UN Convention on the Rights of the Child, which formally and explicitly acknowledges the rights for children under international law to be recognized as subjects of rights, rather than merely recipients of adult protection, and that their views are entitled to be heard. These values are recognized in international asthma guidelines which, for example, encourage children to be involved in decisions made about their care, where appropriate research on self-management conducted in western countries may not be transferable to a Saudi context as self-management by children may not be possible within cultural conventions (i.e. they are socio-culturally expected and conditioned to adhere to what their parents say).

There are other barriers which may prevent the delivery of culturally sensitive pediatric asthma management in KSA, such as asthma management advice being provided by female/male health professionals to all genders. However, the current literature on culturally and ethnically sensitive asthma care is gender blind or gender neutral, and has totally over looked gender as a factor that could affect asthma care and outcomes in cultural context where the mixing of men and women is generally avoided, such as conservative Islamic and orthodox Jewish communities [42]. In Saudi Arabia, male health professionals never attempt to interview or examine female patients without a chaperone (typically a father, brother or adult son) being present. It is highly recommended to have female nurses present if female parents and child patients are to be accorded full recognition in decision making for collaborative asthma care recommended internationally [38]. Although SINA guidelines refer to partnerships between patients and healthcare workers, these values are not in-line with the Saudi culture where women and children are still not given full recognition, and as such they are likely not to be involved in asthma management decisions [7].

However, this issue has been over-looked and un-recognized to-date. Despite the fact that SINA guidelines indicated that asthma education program should be conducted by well-trained health care providers with good communication skills to the families, the cultural barriers to this are not acknowledged (e.g. the need for specific education sessions for mothers and for fathers). There is an urgent need for future research into this area to better understand the issue and to identify in what ways asthma management and education can be better tailored to the cultural needs of children and their parents in countries like KSA. Studies of pediatric asthma management also show indications of inadequate culturally sensitive management different settings in Saudi Arabia.

Culturally sensitive asthma care in KSA confers a key role on qualitative research, for instance observation of asthma consultations might enable exploration of whether non-Saudi health professionals are able to offer culturally sensitive asthma care, and how the situation can be improved. During doing a qualitative research, it can be argued that interviews could be harder when women are covered and veiled since it is agreed that studying verbal and non-verbal communications could not be fully understood without obtaining the views and feelings of the people concerned (Holloway & Wheeler, 2002; Parahoo, 2006). Obviously, any such disadvantage was greatly reduced for me due to my cultural competence with veiled Saudi women (see section 4.3.2). Nevertheless, I did not merely rely on the participants’ memories, but I also distinguished between participants’ descriptions in words and their actions to determine any inconsistencies between what they said and what they did (Holloway & Wheeler, 2002).

Asthma knowledge can only be applied effectively with culturally sensitive practices and attitudes adopted by nurses in their interactions with clients [38]. To navigate these cultural issues, interviews with parents of children with asthma and their health professionals enrich the nursing understanding of asthma management and patient education in KSA, providing culturally appropriate, tailored care and avoiding the mismanagement common in developing countries whereby Western (cultural) models are imported and applied wholesale, without consideration of the local context.

Conclusion

The prevalence of asthma amongst children in KSA is high in comparison to the rest of the world and it is increasing. This results in significant costs for individual children, their families and the country. This paper highlights specific contextual issues which make effective pediatric asthma management in KSA challenging. The need for culturally sensitive asthma care has been raised in countries such as the UK, where Arabic patients are a minority. This paper highlights that there is also a need for culturally sensitive asthma care in countries like KSA where Arabic patients are cared for by health professionals recruited from other countries who do not share their culture, beliefs and values. Culturally and ethnically sensitive asthma care is an un-recognized issue within pediatric asthma care generally and needs to be better understood to be fully addressed by qualitative research.

Read More About Lupine Publishers Journal of Clinical & Community Medicine Please Click on Below Link:
https://journalofclinicalcommunitymedicine.blogspot.com/

Tuesday, 17 August 2021

Lupine Publishers| From Merck's CCK- Antagonists Via 4-Amino-2(5H)- Furanones towards 5-Hydroxy-Pyrrol-2-Ones: Design, Synthesis and Evaluation of PNB-001 & PNB-081 as Experimental Therapeutic Agents in Pain Management

Lupine Publishers| Drug Designing & Intellectual Properties International Journal (DDIPIJ)

Abstract

Arylated 5-hydroxy-pyrrol-2-ones were prepared in 2 synthetic steps from muco-chloric acid and were optimised as CCK / CCK2 selective ligands using radio labelled binding assays. A potent CCK selective ligand was identified (PNB-081: CCK1=20nM) as well as a potent CCK2 ligand (PNB-001, IC50= 22nM) during a systematic SAR optimisation. The antagonism was confirmed for both ligands by using isolated tissue preparations with CCK5 and CCK8S. Subsequent in vivo evaluation revealed analgesic activity for the gastrin CCK2 antagonist PNB-001, in the hotplate and tail immersion test at 0.5mg /kg by IP administration in mice. The cholecystokinin antagonist PNB-081 potentiated the analgesic effect of morphine and reversed opiate tolerance in mice from doses >1 mg/kg by oral administration.

Keywords: Phenyl-Pyrolone; CCK Antagonist; Cholecystokinin; Analgesic; Opiate Adjunct

Abbrevations: GIT: Gastrointestinal Tract; TT: Test Thresholds; BT: Base Line Withdrawal Thresholds; ANOVA: Analysis Of Variance

Introduction

In terms of cholecystokinin-physiology [1], CCK8is the most common peptide hormone, which is extensively found throughout the gastrointestinal tract (GIT) and is also widely distributed through the nervous system [2]. Originally, cholecystokinin was discovered to cause contractions of the gallbladder [3]. It was then rediscovered as pancreozymin, triggering the release of pancreatic enzymes. Finally, it was confirmed that both peptides are identical [4]. Cholecystokinin acts as a neuro modulator as well as gut hormone. CCK-ligands, agonists and antagonists have been extensively investigated as potential drug molecules [5]. Cholecystokinin antagonists have been extensively investigated as potential drug targets [6]. They were studied as growth inhibitors in certain forms of cancer [7], as anxiolytics [8], in the treatment of schizophrenia [9] and satiety [10]. An agonist, the shortened CCK4 was found to induce panic in patients [11] and the CCK2 receptor is known to mediate anxiety [12] and panic attacks [13]. Cholecystokinin does cause proliferation in colon- and pancreatic cancer cell lines and therefore, CCK-antagonists were studied as growth factor inhibitors in certain forms of cancer. Asperlicin was the first non-peptidal lead structure from nature [14] and analogues thereof were studied as CCK ligands [15]. Simplification of this lead structure by Merck led to Devazepide [16], a potent CCK1 selective cholecystokinin antagonist (Figure 1a), containing a 1,4- benzodiazepine template and an indole moiety.

Figure 1a: Discovery; Merck's CCK patents. From the natural product asperlicin to a fully synthetic 1,4-benzodiazepine lead structure.

Lupinepublishers-openaccess-Drugdesigning-Intellectualproperties

Proglumide [17] was the first glutamic acid based agent, marketed as Milid for the treatment of ulcer. Lorglumide, a derivative of proglumide [18], (Figure 1b) is one of several CCK receptor antagonists [19] and served as experimental standard. The indolyl amide of devazepide was replaced by a urea linkage and Merck's L-365,260 resulted in a CCK2 selective antagonist [20]. Further subsequent SAR optimization led to Zeria's improved Z-360 [21], in which the N-alkyl side chain, the 5- position (cyclohexyl) was optimized for potency and a meta-carboxylic acid on the aryl urea linkage was introduced to enhance water solubility (Figure 1c). Z-360 is a CCK2-gastrin receptor antagonist and progressed into phase 2 trial with pancreatic cancer [22]. Z-360 is the most recent derivative derived from this original lead structure, with improved selectivity and bioavailability.

Figure 1b Cholecystokinin standard-Lorglumide. Rotta Research Labs. Patents based on glutamic acid, agents with little membrane penetration.

Lupinepublishers-openaccess-Drugdesigning-Intellectualproperties

Figure 1c: Merck's SAR optimisation from Devazepide towards a gastrin antagonist L-365,260 with final optimisation by Zeria Ltd and selection patent on Z-360.

Lupinepublishers-openaccess-Drugdesigning-Intellectualproperties

All structural optimisations did only partly address the main underlying problem with respect to poor pharmacokinetic properties, such as a low water solubility and very low membrane penetration, as a result of a large polar surface area of the molecules and a relatively high molecular weight. In our early search for new CCK ligands, in which the 1, 4-benzodiazepine structure [23] was replaced by an achiral diphenyl pyrazolone template, novel CCK antagonists with an indole carboxylic acid [24] and a phenyl urea moiety [25] were found and optimized with excellent animal data on anxiety and depression [26]. The patent was discontinued as structure was part of a Chinese molecular modelling patent application (Figure 1d). The 1,4-benzodiazepine template was varied by a combinatorial solid phase synthesis [27] and it was SAR optimised in terms of CCK binding affinity to a benzodiazepine with a simple propyl group [28]. Again, having realized the poor pharmacokinetic properties these agents, a search for a completely novel, smaller template with a molecular weight <350, a log p about 3 and a polar surface area for membrane penetration of less that 100A, with no urea linkage was initiated. Aim of the drug discovery programme, initiated by PNB Vesper Life Sciences, was to systematically investigate and design the 2(5H)-furanone scaffold [29] in to a hydroxy-pyrolone scaffold with ligands for both CCK pathways (Figure 1e). Molecular pain targets have been reviewed recently [30] and the results are quite disappointing in terms of efficacy and FDA approval rate. Even, this review missed out on CCK antagonists [31] and most importantly on a very positive report, publicised only in form of an abstract [32]. In summary in this study, devazepide at 5 mg was found very efficient in pain management as adjunct to strong opiates in a phase 2 trial carried out at leading UK pain research centres. Initial results for CCK antagonists of the pyrolone scaffold were communicated in the area of cancer therapeutics [33] and GI inflammation [34]. Here, a full biological evaluation of PNB Vesper Life Science's pain moleculesPNB-001& PNB-081, which are covered by an original patent, are reported in detail here with respect to pain management [35].

Figure 1d: Urea / Amide based CCK antagonists covered by Aston University patent replacing the 1,4-benzodiazepine scaffold with a pyrazole.

Lupinepublishers-openaccess-Drugdesigning-Intellectualproperties

Figure 1e: From lactones to lactams. Discovery of pyrolones as a novel CCK-template. From an Aston University user patent on 4-amino-2(5H)-furanonesto a novel original template.

Lupinepublishers-openaccess-Drugdesigning-Intellectualproperties

Results and Discussions

Chemistry

5-arylated dichloro-2(5H)-furanones A and B were synthesised from muco-chloric acid (Scheme 1), which is commercially available from furfural under oxidising conditions with hydrochloric acid. Theses intermediates were evaluated previously as anticancer agents [36]. Muco-chloric acid was reacted with benzene as reagent and solvent at RT under the development of hydrogen chloride gas. Depending on the scale of the reaction cooling with ice was required. For chloro benzene / benzene the powdered or most preferred granulated aluminium chloride served as the best catalyst and during work up with hydrochloric acid on ice the inorganic salts were easily removed from the organic phase. In terms of scope of the reaction arylated 2(5H)-furanones, containing nitro- groups or trifluoro-methyl groups could not be prepared. For the small scale synthesis aluminium chloride worked well as Lewis acid. However, during scale up aluminium chloride was replaced by trifluoroborane in THF as the exothermic reaction become problematic on a kg scale.

Scheme 1: Synthesis and chemical mechanism for the preparation of lactams1-21 from muco-chloric acid.
a) Arene, RT, 10 h, workup: hydrochloric acid; b) amine , excess, ether, RT, 30 min

Lupinepublishers-openaccess-Drugdesigning-Intellectualproperties

Subsequent reaction of the 5-arylated 3,4-dichloro-2(5H)- furanones A and B (Stage 1 intermediate) in diethyl ether with alkyl- and aryl alkyl amines furnished N-alkylated hydroxyl-pyrrolones1- 21(Stage 2 products) in high yields under mild conditions. The general synthetic sequence is outlined in Scheme 1.

Overall, the desired N-alkylated unsubstituted 5-phenyl pyrrolones1-21 was obtained in only a 2 stage process as white crystalline material. The molecule is not present in the ring opened keto form and fully occurred in the 5-membered ring form, as a hydroxy-pyrolone. The 5-arylated 2(5H)-furanones reacted selectively in the ester position and no reaction in the 4-position was observed here. Previously the IPSO substitution (4-position) was described for pseudo- esters [37], and here in Scheme 1, a ring- opening ring-closure mechanism is proposed for the formation of hydroxy-pyrolone. Thus, the first step in the reaction sequence of the dichlorinated 2(5H)-furanone is the ring opening and amide formation from the corresponding lactone. Subsequently, the keto form of the acyclic amide was in situ converted into a lactam under the elimination of hydrogen chloride (middle, scheme 1). The analysis of lactam7 and 20by chiral HPLC showed a 50:50 racemic mixture of both enantiomers in solution in methanol.

Read More About Lupine Publishers Drug Designing & Intellectual Properties International Journal (DDIPIJ) Please Click on Below Link:  https://lupine-publishers-drug-designing.blogspot.com/